消化管は「4層の管」という同じ設計の繰り返しで、区間ごとに違うのは粘膜の形・筋層の工夫・血管の由来の3つだけである。
目標は「見て区間を言い当てられるか」。輪状ヒダがあれば空腸、絨毛が乏しく半月ヒダと結腸ヒモがあれば大腸——粘膜と外面の形が区間の名札になっている。
この範囲の芯は「発生の3本の動脈が、成人の血管支配と関連痛の高さを今も決めている」ことである。腹腔動脈・上腸間膜動脈・下腸間膜動脈の境目は、そのまま前腸・中腸・後腸の境目であり、痛みが心窩部・臍周囲・下腹部のどこに出るかの境目でもある。
- 食道 — 3部・3狭窄
- 胃 — 部位・弯・壁
- 十二指腸 — C字の4部
- 空腸と回腸 — 見分け方
- 大腸 — 外から見て分かる3つの特徴
- 直腸と肛門管 — 歯状線で全部が変わる
- 内臓学の総論 — 管腔臓器と実質臓器
- 発生 — 管ができ、回り、戻って固定される
- 食道
- 食道口
- 噴門口
- 噴門部
- 胃底
- 胃体
- 大弯
- 小弯
- 幽門括約筋
- 十二指腸上部
- 十二指腸下行部
- 大十二指腸乳頭
- 十二指腸水平部・上行部
- 空腸
- 回腸
- 腸間膜
- 盲腸
- 虫垂
- 上行結腸
- 右結腸曲(肝弯曲)
- 横行結腸
- 左結腸曲(脾弯曲)
- 下行結腸
- S状結腸
- 大網ヒモ
- 直腸
- 直腸膨大部
- 直腸横ひだ
- 肛門管
- 肛門
- 食道 — 3部・3狭窄Oesophagus
- 胃 — 部位・弯・壁Gaster
- 十二指腸 — C字の4部Duodenum
- 空腸と回腸 — 見分け方Intestinum tenue
- 大腸 — 外から見て分かる3つの特徴Intestinum crassum
- 直腸と肛門管 — 歯状線で全部が変わるRectum et canalis analis
- 内臓学の総論 — 管腔臓器と実質臓器Organa cava et parenchymatosa
- 発生 — 管ができ、回り、戻って固定されるIntestinum primitivum
- 食道Oesophagus
- 食道口Ostium oesophageum
- 噴門口Ostium cardiacum
- 噴門部Pars cardiaca
- 胃底Fundus gastricus
- 胃体Corpus gastricum
- 大弯Curvatura major
- 小弯Curvatura minor
- 幽門括約筋Musculus sphincter pyloricus
- 十二指腸上部Pars superior duodeni
- 十二指腸下行部Pars descendens duodeni
- 大十二指腸乳頭Papilla duodeni major
- 十二指腸水平部・上行部Pars horizontalis, pars ascendens duodeni
- 空腸Jejunum
- 回腸Ileum
- 腸間膜Mesenterium intestinale
- 盲腸Caecum
- 虫垂Appendix vermiformis
- 上行結腸Colon ascendens
- 右結腸曲(肝弯曲)Flexura coli dextra
- 横行結腸Colon transversum
- 左結腸曲(脾弯曲)Flexura coli sinistra
- 下行結腸Colon descendens
- S状結腸Colon sigmoideum
- 大網ヒモTaenia omentalis
- 直腸Rectum
- 直腸膨大部Ampulla recti
- 直腸横ひだPlicae transversae recti
- 肛門管Canalis analis
- 肛門Anus
- まとめ
食道 — 3部・3狭窄Oesophagus
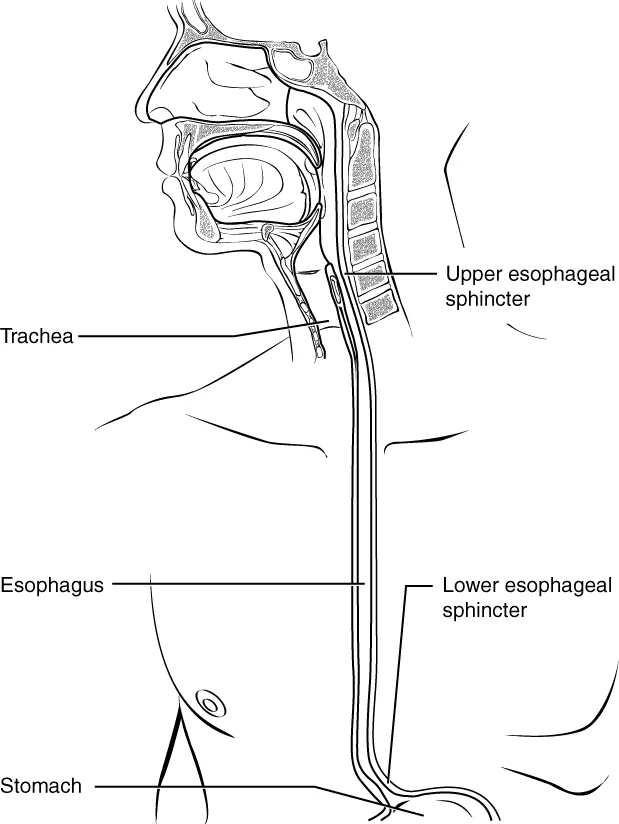
C6(輪状軟骨の下縁)から Th11(胃の噴門)まで、約25cm。3部:pars cervicalis(頸部・約5cm)・pars thoracica(胸部・約16cm)・pars abdominalis(腹部・約1〜2cm)。
3つの狭窄 — 解剖でも臨床でも必ず押さえる。
| 狭窄 | 高さ | 原因 | 切歯からの距離 |
|---|---|---|---|
| 第1(食道入口部) | C6 | 輪状咽頭筋 | 約15cm |
| 第2(大動脈・気管支) | Th4〜5 | 大動脈弓と左主気管支の交叉 | 約25cm |
| 第3(横隔膜) | Th10 | 食道裂孔 | 約40cm |
内腔には縦走する plicae longitudinales があり、拡張すると消える。
筋層は上から下へ骨格筋から平滑筋へ入れ替わる。上1/3が横紋筋、中1/3が混在、下1/3が平滑筋。だから上部の嚥下障害は神経筋疾患(ALS・重症筋無力症)、下部はアカラシアや GERDと、障害の性質が高さで変わる。
3つの狭窄は「詰まる・傷む・癌ができる」場所である。誤飲した異物や腐食性の液体はここで停留し、癌もここに好発する。内視鏡の距離(15・25・40cm)を覚えておくと所見の位置が読める。
食道の血管は上・中・下で由来が違う。頸部=下甲状腺動脈、胸部=胸大動脈の食道枝と気管支動脈、腹部=左胃動脈・下横隔動脈。静脈が要点で、下部だけが左胃静脈(門脈系)へ注ぐ——だから門脈圧亢進で食道静脈瘤ができる。門脈系と大循環系が粘膜下で吻合する場所という一点が、肝硬変の最も危険な合併症を作っている。
3つの生理的狭窄は、そのまま異物と癌と腐食性損傷の好発部位である。①食道入口部(輪状咽頭筋・C6)②大動脈弓と左主気管支の交叉部(Th4〜5)③横隔膜の食道裂孔(Th10)。
食道静脈瘤 — 腹部食道では左胃静脈(門脈系)と奇静脈系(大循環)が吻合する。門脈圧亢進でここが逆流路になり、粘膜下で怒張して破裂する。門脈大循環吻合の中で最も致命的な場所である。
食道裂孔ヘルニア — 胃の一部が胸腔へ入り込む。下部食道括約筋の機能が落ちて胸やけ・逆流。
反回神経は食道のすぐ横を走るので、食道癌の進展や手術で嗄声が出る。左反回神経は大動脈弓を回るぶん経路が長く、侵されやすい。
出典:イラスト解剖学 誌面445頁「横隔膜の臨床」
English version
Core
From C6 (the lower border of the cricoid cartilage) to Th11 (the cardia of the stomach), about 25 cm. Three parts: pars cervicalis (about 5 cm), pars thoracica (about 16 cm), pars abdominalis (1–2 cm).
Three constrictions — always to be known, both in anatomy and in the clinic.
| Constriction | Level | Cause | From the incisors |
|---|---|---|---|
| First (oesophageal inlet) | C6 | Cricopharyngeus | about 15 cm |
| Second (aortic and bronchial) | Th4–5 | Crossing of the aortic arch and left main bronchus | about 25 cm |
| Third (diaphragmatic) | Th10 | The oesophageal hiatus | about 40 cm |
The lumen carries longitudinal plicae longitudinales, which disappear on distension.
Going further
The muscle changes from skeletal to smooth from above downwards: striated in the upper third, mixed in the middle, smooth in the lower. So dysphagia of the upper part is neuromuscular (ALS, myasthenia gravis) and of the lower achalasia or GERD — the nature of the disorder changes with the level.
The three constrictions are the places that block, are injured, and develop cancer. Swallowed foreign bodies and corrosive fluids are held up there, and carcinoma has a predilection for them. Knowing the endoscopic distances (15, 25, 40 cm) lets the position of a finding be read.
The blood supply differs in the three parts: cervical from the inferior thyroid artery; thoracic from the oesophageal branches of the thoracic aorta and the bronchial arteries; abdominal from the left gastric and inferior phrenic arteries. The veins are the point: only the lower part drains to the left gastric vein (portal) — hence oesophageal varices in portal hypertension. The single fact that portal and systemic systems anastomose in the submucosa here creates the most dangerous complication of cirrhosis.
In the clinic
The three physiological constrictions are directly the sites of predilection for foreign bodies, for carcinoma and for corrosive injury. ① the inlet (cricopharyngeus, C6) ② the crossing of the aortic arch and left main bronchus (Th4–5) ③ the oesophageal hiatus (Th10).
Oesophageal varices — in the abdominal oesophagus the left gastric vein (portal) anastomoses with the azygos system (systemic). In portal hypertension this becomes a route of reversed flow, and the submucosal veins distend and rupture. The most lethal of the portosystemic anastomoses.
Hiatus hernia — part of the stomach enters the thorax. The lower oesophageal sphincter fails, giving heartburn and reflux.
The recurrent laryngeal nerve runs beside the oesophagus, so hoarseness follows the spread of oesophageal carcinoma or its surgery. The left recurrent nerve, having the longer course round the aortic arch, is the more readily involved.
胃 — 部位・弯・壁Gaster
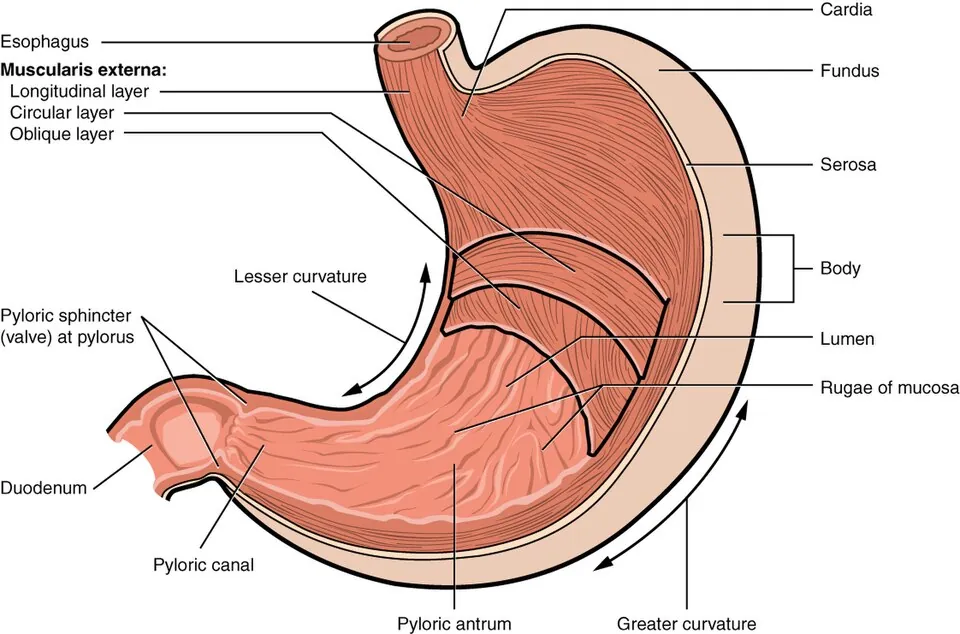
2つの口:ostium cardiacum(噴門・Th11 左)と ostium pyloricum(幽門・L1 右)。2つの弯:curvatura minor(小弯・右上)と curvatura major(大弯・左下)。小弯の途中の切れ込みが incisura angularis、噴門の左上の切れ込みが incisura cardialis。
4部:pars cardiaca → fundus gastricus(噴門より上に膨れる部分・立位ではガスが溜まる)→ corpus gastricum → pars pylorica(広い antrum pyloricum と狭い canalis pyloricus)。
粘膜には plicae gastricae(胃ヒダ・小弯に沿って縦走)。幽門には m. sphincter pyloricus(輪走筋の肥厚)。
胃の筋層は3層(外=縦走、中=輪走、内=斜走 fibrae obliquae)。消化管で内斜走層を持つのは胃だけで、内容物を捏ねるために必要な層である。「4層の管」の例外として問われる。
血管は弯に沿って2本ずつの弓を作る。小弯=左胃動脈(腹腔動脈から直接)+ 右胃動脈(総肝動脈から)、大弯=左胃大網動脈(脾動脈から)+ 右胃大網動脈(胃十二指腸動脈から)。底部は短胃動脈(脾動脈から)。すべて腹腔動脈の分枝——胃は前腸だからである。
肥厚性幽門狭窄症は生後2〜6週の乳児で幽門括約筋が肥厚し、噴水状嘔吐と右上腹部のオリーブ様腫瘤を起こす。胆汁を含まない嘔吐であることが決め手——閉塞が大十二指腸乳頭より上流にあるためで、解剖の位置がそのまま所見になる。
胃切除後症候群は、胃の貯留機能と分泌機能を失った結果として起こる。
早期ダンピング症候群 — 食後30分以内。高浸透圧の食塊が急に小腸へ落ち、腸管内へ水が引き込まれて循環血漿量が減り、動悸・冷汗・血圧低下・腹痛。
後期ダンピング症候群 — 食後2〜3時間。急速な吸収で一過性高血糖 → インスリン過剰分泌 → 反応性低血糖。脱力・冷汗・めまい。
貧血が2種類出る。鉄欠乏性貧血 — 胃酸が減って鉄の吸収が落ちる(術後早期から)。巨赤芽球性貧血 — 壁細胞の内因子が失われ、回腸末端でのビタミン B12 吸収が絶たれる。肝に約5mg 貯蔵があるので、欠乏が現れるのは数年後——「胃全摘の既往」を何年たっても聞く理由がここにある。
出典:イラスト解剖学 誌面411頁「胃切除術と胃切除後障害」
English version
Core
Two orifices: ostium cardiacum (Th11, left of the midline) and ostium pyloricum (L1, to the right). Two curvatures: curvatura minor (upper right) and curvatura major (lower left). The notch along the lesser curvature is the incisura angularis, the notch above and left of the cardia the incisura cardialis.
Four parts: pars cardiaca → fundus gastricus (the dome above the cardia, where gas collects in the standing position) → corpus gastricum → pars pylorica (the wide antrum and the narrow canalis pyloricus).
The mucosa carries the plicae gastricae (running longitudinally along the lesser curvature). At the pylorus is the m. sphincter pyloricus (a thickening of the circular muscle).
Going further
The muscle coat has three layers (outer longitudinal, middle circular, inner oblique — fibrae obliquae). The stomach is the only part of the tract with an inner oblique layer, needed for kneading the contents. It is asked as the exception to "a four-layered tube".
The vessels form two arches along each curvature. Lesser curvature = left gastric (direct from the coeliac) + right gastric (from the common hepatic); greater curvature = left gastro-omental (from the splenic) + right gastro-omental (from the gastroduodenal). The fundus is supplied by the short gastric arteries (from the splenic). All are branches of the coeliac artery — because the stomach is foregut.
Hypertrophic pyloric stenosis occurs at 2–6 weeks of age: the pyloric sphincter hypertrophies, giving projectile vomiting and an olive-like mass in the right upper quadrant. That the vomitus contains no bile is decisive — the obstruction lies upstream of the major duodenal papilla, and the position in the anatomy is directly the finding.
In the clinic
The post-gastrectomy syndromes arise from losing the reservoir and secretory functions of the stomach.
Early dumping — within 30 minutes of eating. A hyperosmolar bolus falls suddenly into the small intestine, water is drawn into the lumen, the circulating volume falls, and there are palpitations, sweating, hypotension and abdominal pain.
Late dumping — 2–3 hours after eating. Rapid absorption causes transient hyperglycaemia → excessive insulin release → reactive hypoglycaemia, with weakness, sweating and dizziness.
Two kinds of anaemia occur. Iron deficiency — acid falls and iron is absorbed less well (from early after operation). Megaloblastic anaemia — intrinsic factor from the parietal cells is lost and the absorption of B12 in the terminal ileum is cut off. The liver holds about 5 mg in store, so the deficiency appears only years later — which is why a history of total gastrectomy is asked about however long ago it was.
十二指腸 — C字の4部Duodenum
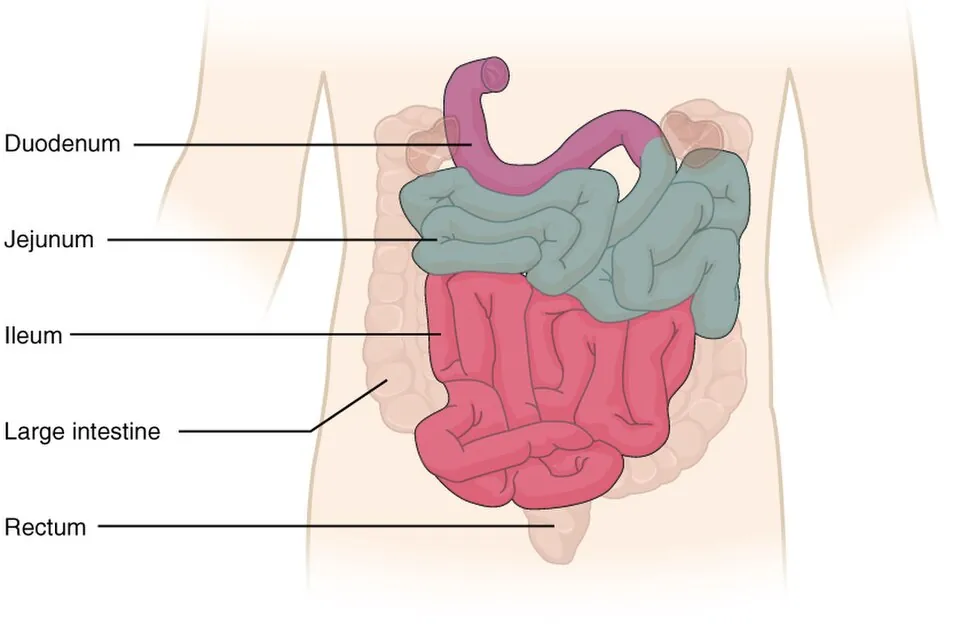
長さ約25cm(指12本ぶん)。膵頭を抱くC字で、大部分が後腹膜(二次的)。
| 部 | 高さ・向き | 特徴 |
|---|---|---|
| Pars superior | L1・右へ水平 | 始まりの2.5cm が ampulla(bulbus)。粘膜が滑らか。腹腔内(可動) |
| Pars descendens | L1〜L3・下行 | 後内側壁に papilla duodeni major(Vater)と minor |
| Pars horizontalis (inferior) | L3・左へ水平 | 上腸間膜動静脈と大動脈に挟まれる |
| Pars ascendens | L3〜L2・上行 | Flexura duodenojejunalis で空腸へ。Treitz 靱帯で固定 |
Papilla duodeni major に総胆管と主膵管が合流して開く(Vater 膨大部、Oddi 括約筋)。ここが前腸と中腸の境で、動脈支配も乳頭を境に上(腹腔動脈系=上膵十二指腸動脈)と下(上腸間膜動脈系=下膵十二指腸動脈)に切り替わる。
Treitz 靱帯(十二指腸提筋)が上部消化管出血と下部消化管出血の境界である。ここより上の出血は吐血・タール便、下は血便になる。解剖の一点が臨床の分類を定義している典型例。
十二指腸潰瘍は球部の前壁・後壁に好発する。前壁が穿孔すれば腹腔内へ(遊離ガス)、後壁が穿通すれば胃十二指腸動脈を破って大出血する。「前は穿孔、後ろは出血」——動脈が後ろを走っているという解剖そのものである。
大十二指腸乳頭(Vater 乳頭)に総胆管と主膵管が一緒に開く。この合流が、胆道と膵臓の病気を結びつける。
総胆管結石が乳頭に嵌頓すると、胆汁と膵液の両方が堰き止められる——閉塞性黄疸と胆石性膵炎が同時に起こりうる。
膵頭部癌は乳頭の手前で総胆管を締めるので、無痛性の閉塞性黄疸で発症する。腫大した胆嚢を触れる(Courvoisier 徴候)。
十二指腸潰瘍は球部(上部の始め2.5cm)に多い。後壁の穿通では胃十二指腸動脈が破れて大量出血、前壁の穿孔では遊離ガス(free air)——前後どちらかで起こることが違う。
上腸間膜動脈症候群 — 水平部が上腸間膜動脈と腹大動脈に挟まれるため、急激な痩せで脂肪が減ると圧迫され、嘔吐をきたす。
English version
Core
About 25 cm long (twelve fingers’ breadth). A C embracing the head of the pancreas, mostly (secondarily) retroperitoneal.
| Part | Level and direction | Features |
|---|---|---|
| Pars superior | L1, horizontally to the right | The first 2.5 cm is the ampulla (bulb), with smooth mucosa. Intraperitoneal (mobile) |
| Pars descendens | L1–L3, descending | Papilla duodeni major (of Vater) and minor on the posteromedial wall |
| Pars horizontalis (inferior) | L3, horizontally to the left | Caught between the superior mesenteric vessels and the aorta |
| Pars ascendens | L3–L2, ascending | Becomes jejunum at the flexura duodenojejunalis, fixed by the ligament of Treitz |
Going further
The common bile duct and the main pancreatic duct join and open at the papilla duodeni major (the ampulla of Vater, with the sphincter of Oddi). This is the boundary of foregut and midgut, and the arterial supply also changes there — above the papilla the coeliac system (superior pancreaticoduodenal), below it the superior mesenteric system (inferior pancreaticoduodenal).
The ligament of Treitz (suspensory muscle of the duodenum) is the boundary between upper and lower gastrointestinal bleeding. Bleeding above it gives haematemesis and melaena, below it fresh blood per rectum. A model case of one point of anatomy defining a clinical classification.
Duodenal ulcers have a predilection for the anterior and posterior walls of the bulb. Perforation of the anterior wall goes into the peritoneal cavity (free gas); penetration of the posterior wall erodes the gastroduodenal artery and bleeds heavily. "Front perforates, back bleeds" — which is simply the anatomy of the artery running behind.
In the clinic
The common bile duct and main pancreatic duct open together at the papilla of Vater, and this confluence links the diseases of the biliary tree and the pancreas.
A common duct stone impacted at the papilla dams back both bile and pancreatic juice — obstructive jaundice and gallstone pancreatitis can occur together.
Carcinoma of the head of the pancreas constricts the common bile duct just short of the papilla and so presents with painless obstructive jaundice, with a palpable distended gallbladder (Courvoisier’s sign).
Duodenal ulcers are commonest in the bulb (the first 2.5 cm). Penetration posteriorly ruptures the gastroduodenal artery and bleeds massively; perforation anteriorly gives free gas — what happens differs according to which wall.
Superior mesenteric artery syndrome — the horizontal part is caught between the superior mesenteric artery and the aorta, so rapid weight loss reduces the fat, it is compressed, and vomiting follows.
空腸と回腸 — 見分け方Intestinum tenue
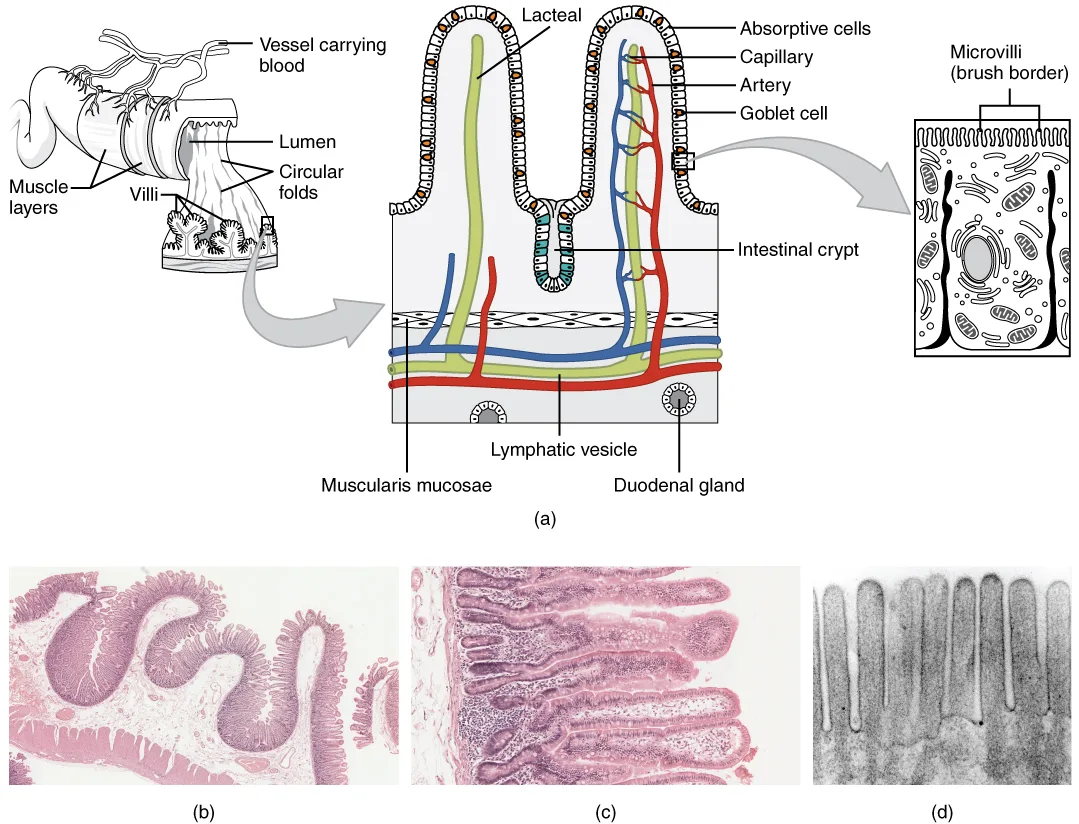
十二指腸空腸曲から回盲弁まで約6〜7m。近位2/5 が jejunum、遠位3/5 が ileumで、明確な境目は無く連続的に変わる。腸間膜で後腹壁に吊られる(radix mesenterii は L2 左から右腸骨窩へ斜めに走る)。
| Jejunum(空腸) | Ileum(回腸) | |
|---|---|---|
| 位置 | 左上腹部 | 右下腹部 |
| 壁 | 厚い・血管に富み赤い | 薄い・蒼白 |
| Plicae circulares | 高く密 | 低く疎(遠位では消失) |
| リンパ組織 | 孤立リンパ小節 | Peyer 板(集合リンパ小節) |
| 血管弓 | 1〜2列・直血管が長い | 4〜5列・直血管が短い |
| 腸間膜の脂肪 | 少ない | 多い(腸管まで這う) |

吸収面積は3段階の折りたたみで増える。Plicae circulares(Kerckring ヒダ)×3 → villi intestinales(絨毛)×10 → microvilli(微絨毛)×20。合計で単純な筒の約600倍、テニスコート1面ぶんになる。肉眼(ヒダ)・光顕(絨毛)・電顕(微絨毛)が、同じ原理の3つの倍率である。
血管弓の列数が空腸と回腸を分ける最も確実な所見で、手術で腸管の向きを判断するのに実際に使われる。
回腸末端は特別な区間である。ビタミンB12(内因子との複合体)と胆汁酸の吸収は、ここでしか行われない。だから回腸末端の切除やクローン病では、巨赤芽球性貧血と脂肪便・胆石が同時に起こる。Peyer 板が多いこともここに炎症が起きやすい理由(クローン病・腸チフス)である。
回腸末端は3つの意味で特別である。①ビタミン B12–内因子複合体の吸収②胆汁酸の再吸収(腸肝循環)③Peyer 板が最も密。
だから回腸末端の切除・Crohn 病では、巨赤芽球性貧血と、胆汁酸が失われることによる脂肪便・脂溶性ビタミン欠乏・胆石が同時に起こる。
Meckel 憩室 — 卵黄腸管の遺残。2の法則(回盲弁から約2フィート、長さ約2インチ、人口の約2%、症状は2歳までに、異所性胃粘膜と膵組織の2種類)。異所性胃粘膜が酸を出して無痛性の下血を起こす。
腸間膜の付着が斜めに走るため、腸重積は回盲部(回腸が結腸へ入り込む)に起こりやすい。
English version
Core
From the duodenojejunal flexure to the ileocaecal valve, 6–7 m. The proximal two fifths are jejunum, the distal three fifths ileum, with no sharp boundary but a continuous change. They are slung from the posterior wall by the mesentery, whose root runs obliquely from the left at L2 to the right iliac fossa.
| Jejunum | Ileum | |
|---|---|---|
| Position | Left upper abdomen | Right lower abdomen |
| Wall | Thick, vascular, red | Thin, pale |
| Plicae circulares | Tall and close-set | Low and sparse (absent distally) |
| Lymphoid tissue | Solitary follicles | Peyer’s patches |
| Vascular arcades | 1–2 tiers; long vasa recta | 4–5 tiers; short vasa recta |
| Mesenteric fat | Little | Much (creeping onto the bowel) |
Going further
The absorptive area is increased by folding in three stages: plicae circulares (of Kerckring) ×3 → villi ×10 → microvilli ×20. Together about 600 times a plain tube — the area of a tennis court. Gross (folds), light microscopy (villi) and electron microscopy (microvilli) are the same principle at three magnifications.
The number of tiers of vascular arcade is the most reliable sign separating jejunum from ileum, and is used in practice at operation to judge the orientation of the bowel.
The terminal ileum is a special stretch. The absorption of vitamin B12 (as the complex with intrinsic factor) and of bile acids occurs only there. So resection of the terminal ileum or Crohn’s disease gives megaloblastic anaemia together with steatorrhoea and gallstones. The abundance of Peyer’s patches is also why inflammation settles there (Crohn’s disease, typhoid).
In the clinic
The terminal ileum is special in three ways. ① absorption of the vitamin B12–intrinsic factor complex ② reabsorption of bile acids (the enterohepatic circulation) ③ the densest Peyer’s patches. So resection of the terminal ileum or Crohn’s disease gives megaloblastic anaemia together with the steatorrhoea, fat-soluble vitamin deficiency and gallstones that follow the loss of bile acids.
Meckel’s diverticulum — a remnant of the vitelline duct. The rule of twos (about 2 feet from the ileocaecal valve, about 2 inches long, in about 2 per cent of the population, symptomatic by age 2, with 2 kinds of ectopic tissue — gastric mucosa and pancreas). Ectopic gastric mucosa secretes acid and causes painless rectal bleeding.
Because the mesenteric attachment runs obliquely, intussusception occurs readily at the ileocaecal region (ileum invaginating into the colon).
大腸 — 外から見て分かる3つの特徴Intestinum crassum
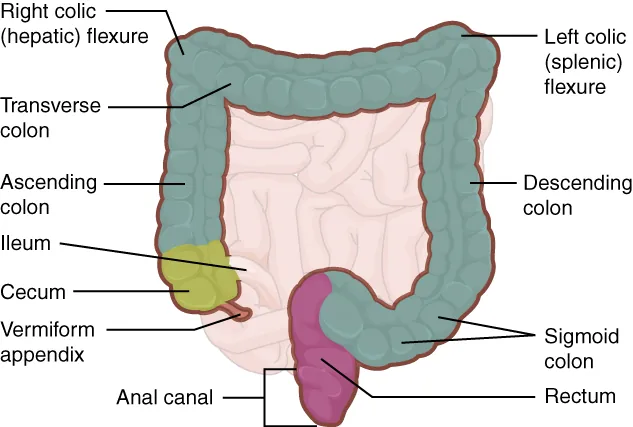
回盲弁から肛門まで約1.5m。Caecum → colon ascendens → flexura coli dextra → colon transversum → flexura coli sinistra → colon descendens → colon sigmoideum → rectum。
外から見て小腸と区別できる3つ(直腸には無いのが重要):
- Taeniae coli — 縦走筋が3本の帯に集まったもの(大網ヒモ・間膜ヒモ・自由ヒモ)
- Haustra coli — ヒモが短いため壁がたるんでできる膨隆
- Appendices epiploicae (omentales) — 漿膜下の脂肪の垂れ下がり
内腔には plicae semilunares coli(半月ヒダ・膨起の境)。盲腸には ostium ileale(回盲口)と ostium appendicis vermiformis。
3本のヒモは虫垂の根元で合流する。これが虫垂切除で虫垂を探す確実な方法である——盲腸の自由ヒモを末梢へたどれば必ず虫垂の基部に着く。虫垂の体表投影は McBurney 点(右上前腸骨棘と臍を結ぶ線の外側1/3)。
ヒモが短いから膨起ができる。結腸ヒモは腸管の全長より短いので、壁が蛇腹に寄せられる。形の理由が力学的に説明できる数少ない例。
憩室は血管が壁を貫くところにできる。直血管が輪走筋層を貫く点が構造的な弱点で、腸管内圧が上がると粘膜がそこから脱出する(仮性憩室)。だから憩室は間膜ヒモと自由ヒモのあいだの列に並ぶし、出血すると動脈性で大量になる。
Flexura coli sinistra(脾彎曲)は中腸と後腸の境で、上腸間膜動脈と下腸間膜動脈の分水嶺(Griffith 点)にあたる。虚血性腸炎がここに好発するのはそのためである。
結腸ヒモ・膨起・腹膜垂は大腸にしかない。開腹時に小腸と大腸を一目で区別する目印であり、3本の結腸ヒモをたどれば必ず虫垂根部に集まる——虫垂を探す最も確実な方法である。
Hirschsprung 病(先天性巨大結腸症) — Auerbach 神経叢と Meissner 神経叢が先天的に欠如し、その部分が縮んだまま広がらない。狭窄しているのは無神経節部で、拡張しているのはその口側という「病変部が細い」逆転が要点である。S状結腸〜直腸に多く、新生児の胎便排泄遅延で気づかれる。診断は直腸生検(神経節細胞の欠如)。
憩室は結腸ヒモに沿って、栄養血管が壁を貫く場所に出る。壁の弱点がそのまま憩室の位置になる。
出典:イラスト解剖学 誌面425頁「腸管の構造と臨床」
English version
Core
From the ileocaecal valve to the anus, about 1.5 m. Caecum → colon ascendens → flexura coli dextra → colon transversum → flexura coli sinistra → colon descendens → colon sigmoideum → rectum.
Three features visible from outside distinguish it from small intestine (and importantly are absent from the rectum):
- Taeniae coli — the longitudinal muscle gathered into three bands (omental, mesocolic, free).
- Haustra coli — the bulges made because the taeniae are short and the wall is puckered.
- Appendices epiploicae (omentales) — pendulous subserous fat.
The lumen carries the plicae semilunares coli (the boundaries of the haustra). The caecum has the ostium ileale and the ostium appendicis vermiformis.
Going further
The three taeniae converge at the base of the appendix. This is the sure way of finding the appendix at appendicectomy — follow the free taenia of the caecum distally and you always arrive at its base. The surface marking is McBurney’s point (the outer third of the line from the right anterior superior iliac spine to the umbilicus).
The haustra exist because the taeniae are short. The taeniae are shorter than the whole length of the bowel, so the wall is gathered like a concertina. One of the few cases where the reason for a shape can be explained mechanically.
Diverticula form where the vessels pierce the wall. The point at which a vas rectum pierces the circular muscle is a structural weakness, and when the intraluminal pressure rises the mucosa herniates through it (a false diverticulum). So diverticula line up in rows between the mesocolic and free taeniae, and when they bleed the bleeding is arterial and profuse.
The flexura coli sinistra is the boundary of midgut and hindgut and the watershed between superior and inferior mesenteric arteries (Griffith’s point). Hence the predilection of ischaemic colitis for that site.
In the clinic
Taeniae, haustra and appendices epiploicae belong to the large intestine alone. They are the marks by which small and large bowel are told apart at a glance at laparotomy, and following the three taeniae always brings you to the base of the appendix — the surest way of finding it.
Hirschsprung’s disease (congenital megacolon) — the myenteric and submucosal plexuses are congenitally absent and that segment stays contracted and will not distend. The narrowed part is the aganglionic segment and the dilated part is the bowel above it — the inversion that "the diseased part is the narrow one" is the point. Commonest in sigmoid and rectum, noticed as delayed passage of meconium in the newborn. The diagnosis is by rectal biopsy (absence of ganglion cells).
Diverticula appear along the taeniae, where the nutrient vessels pierce the wall. The weak point of the wall is directly the position of the diverticulum.
直腸と肛門管 — 歯状線で全部が変わるRectum et canalis analis
Rectum(S3 から)は仙骨の前を下り、ampulla recti で膨らんでから後下方へ曲がって canalis analis(約4cm)となり anus に終わる。結腸ヒモ・膨起・腹膜垂は無い。
内腔に plicae transversae recti(Houston 弁)が3枚。肛門管には縦の columnae anales があり、その下端を繋ぐヒダのあいだが sinus anales。粘膜下の静脈叢が zona haemorroidalis。
括約筋は2つ:内側の m. sphincter ani internus(輪走平滑筋の肥厚・不随意)と外側の m. sphincter ani externus(横紋筋・随意・陰部神経)。
Linea pectinata(歯状線)は発生の境目——上が内胚葉(後腸)、下が外胚葉(肛門窩)。この一線を境に、あらゆる性質が入れ替わる。
| 歯状線より上 | 歯状線より下 | |
|---|---|---|
| 上皮 | 単層円柱 | 重層扁平 |
| 動脈 | 上直腸動脈(下腸間膜) | 下直腸動脈(内陰部) |
| 静脈 | 上直腸静脈 →門脈 | 下直腸静脈 →下大静脈 |
| リンパ | 下腸間膜・内腸骨 | 浅鼠径リンパ節 |
| 神経 | 自律神経(痛みを感じない) | 陰部神経(強く痛む) |
| 痔核 | 内痔核(痛くない・出血) | 外痔核(痛い) |
ここも門脈大循環吻合の一つで、門脈圧亢進で痔静脈叢が怒張する。「痛いかどうかで内外を分ける」のは、神経支配が発生の由来で切り替わっているからである。
歯状線で、すべてが切り替わる。発生(内胚葉/外胚葉)の境界だからである。
上(内胚葉側) — 単層円柱上皮、自律神経支配で痛みを感じない、上直腸静脈 →門脈、リンパは内腸骨。内痔核は痛くないのはこのため。
下(外胚葉側) — 重層扁平上皮、陰部神経支配で鋭い痛み、下直腸静脈 →大循環、リンパは浅鼠径リンパ節。外痔核・裂肛は激痛。
この違いは癌の転移先も決める。歯状線より下の肛門管癌は鼠径リンパ節へ転移するので、触診で必ず鼠径部を確認する。
直腸診で前方に触れるのは、男性では前立腺、女性では子宮頸部と Douglas 窩。Douglas 窩は立位・坐位で腹腔の最下点なので、腹腔内の出血や膿がここに溜まる。
出典:イラスト解剖学 誌面430頁「直腸の臨床区分」
English version
Core
The rectum (from S3) descends in front of the sacrum, dilates as the ampulla recti, then turns down and back as the canalis analis (about 4 cm) to end at the anus. It has no taeniae, haustra or appendices epiploicae. The lumen carries three plicae transversae recti (Houston’s valves).
The anal canal has longitudinal columnae anales, with the sinus anales between the folds joining their lower ends. The submucosal venous plexus is the zona haemorrhoidalis.
Two sphincters: the inner m. sphincter ani internus (thickened circular smooth muscle, involuntary) and the outer m. sphincter ani externus (striated, voluntary, pudendal nerve).
Going further
The linea pectinata (dentate line) is a developmental boundary — endoderm (hindgut) above, ectoderm (the proctodeum) below. Across this single line every property changes over.
| Above the dentate line | Below it | |
|---|---|---|
| Epithelium | Simple columnar | Stratified squamous |
| Artery | Superior rectal (inferior mesenteric) | Inferior rectal (internal pudendal) |
| Vein | Superior rectal → portal | Inferior rectal → inferior vena cava |
| Lymph | Inferior mesenteric, internal iliac | Superficial inguinal nodes |
| Nerve | Autonomic (pain is not felt) | Pudendal (severe pain) |
| Piles | Internal (painless, bleeding) | External (painful) |
This is another portosystemic anastomosis, and the haemorrhoidal plexus distends in portal hypertension. That internal and external are divided by whether it hurts is because the innervation changes over with the developmental origin.
In the clinic
Everything changes over at the dentate line, because it is the boundary of development (endoderm / ectoderm).
Above (endodermal) — simple columnar epithelium, autonomic supply and no pain, superior rectal vein → portal, lymph to the internal iliac nodes. This is why internal piles are painless.
Below (ectodermal) — stratified squamous epithelium, pudendal supply and sharp pain, inferior rectal vein → systemic, lymph to the superficial inguinal nodes. External piles and fissures are agonising.
The difference also decides where a cancer metastasises. Carcinoma of the anal canal below the dentate line spreads to the inguinal nodes, so always examine the groin.
On rectal examination, what is felt anteriorly is the prostate in the man and the cervix and pouch of Douglas in the woman. The pouch of Douglas is the lowest point of the peritoneal cavity in the standing or sitting position, so blood and pus collect there.
内臓学の総論 — 管腔臓器と実質臓器Organa cava et parenchymatosa
内臓学は、胸腔・腹腔・骨盤腔にあり、漿膜(胸膜・心膜・腹膜)と関わる臓器を扱う。系統は消化器・呼吸器・泌尿器・生殖器の4つ。形で見ると、内臓は2つの型に分かれる。
| 管腔臓器(中空臓器) | 実質臓器 | |
|---|---|---|
| 形 | 管や袋。中に空洞がある | 中身の詰まった塊 |
| 例 | 食道・胃・腸・気管・尿管・膀胱・子宮 | 肝・膵・腎・脾・肺・甲状腺 |
| つくり | 壁が層をなす:粘膜(上皮・粘膜固有層・粘膜筋板)→ 粘膜下組織(血管・神経・リンパ)→ 筋層 → 外膜または漿膜 | 被膜から中へ中隔が入り、葉・小葉に区切る。枠組みの間質と、働く細胞の実質 |
| 出入り口 | 両端の開口 | 門(hilum / porta):血管・神経・リンパ管・導管が出入りする |
管腔臓器は中身を運び、実質臓器は血液を処理する。だから管腔臓器は動くための筋層と、守り・吸収するための粘膜を持ち、実質臓器は血液を出し入れする門を持つ。門という考え方を1つ持っておくと、肝門・脾門・腎門・肺門の中身が同じ形で並ぶ(動脈・静脈・導管か気管支・神経・リンパ管)。
一番外の層は、漿膜腔に面していれば漿膜、面していなければ周りとつながる結合組織の外膜になる。胸部の食道は外膜、腹部の食道と胃は漿膜、直腸の下部は外膜——腹膜の覆い方(「肝・胆道・膵・脾・腹膜」の章の「腹膜と臓器の位置関係」)がそのまま壁の最外層を決める。
病気の出方も型で分かれる。管腔臓器は詰まる・破れる・伸ばされて痛む(疝痛)。実質臓器は被膜が引き伸ばされて痛む——急性肝炎やうっ血肝で右上腹部が重く痛むのは肝の被膜が張るためで、実質そのものには痛覚が乏しい。
漿膜の無い臓器(食道・直腸の下部)は、吻合した縫い目が漏れやすい。漿膜が縫い代となって早く癒着してくれないためである。手術で出血を止めるときは、実質臓器では門で血管をまとめて押さえる(肝十二指腸間膜を挟む Pringle 法、腎門の遮断)。
English version
Core
Splanchnology deals with the organs in the thoracic, abdominal and pelvic cavities that relate to serous membranes (pleura, pericardium, peritoneum). There are four systems: digestive, respiratory, urinary and genital. By shape, viscera fall into two types.
| Hollow (tubular) organs | Parenchymatous (solid) organs | |
|---|---|---|
| Shape | Tube or sac with a cavity inside | Solid mass |
| Examples | Oesophagus, stomach, intestine, trachea, ureter, bladder, uterus | Liver, pancreas, kidney, spleen, lung, thyroid |
| Structure | Layered wall: mucosa (epithelium, lamina propria, muscularis mucosae) → submucosa (vessels, nerves, lymphatics) → muscular layer → adventitia or serosa | A capsule sends septa inward, dividing lobes and lobules; a framework of stroma and working cells of parenchyma |
| Doorway | Openings at both ends | Hilum / porta: vessels, nerves, lymphatics and ducts enter and leave |
Going further
Hollow organs move contents; solid organs process blood. So hollow organs have muscle to move and mucosa to protect and absorb, while solid organs have a hilum to bring blood in and out. Keep the idea of a hilum and the contents of the porta hepatis and the splenic, renal and lung hila line up in the same way (artery, vein, duct or bronchus, nerves, lymphatics).
The outer layer is serosa if the organ faces a serous cavity and adventitia (connective tissue blending with surroundings) if it does not. The thoracic oesophagus has adventitia, the abdominal oesophagus and stomach serosa, the lower rectum adventitia — the peritoneal covering (see “Intraperitoneal, mesoperitoneal and retroperitoneal organs” in the liver–pancreas–peritoneum chapter) decides the outer layer of the wall.
In the clinic
Disease patterns follow the type. Hollow organs block, perforate, or hurt when stretched (colic). Solid organs hurt when the capsule is stretched: the heavy right upper pain of acute hepatitis or congested liver comes from the tense capsule; the parenchyma itself has little pain sense.
Organs without serosa (oesophagus, lower rectum) leak more easily at an anastomosis, because no serosa is there to seal the suture line quickly. To stop bleeding in a solid organ, surgeons control the vessels together at the hilum (Pringle manoeuvre at the hepatoduodenal ligament, clamping the renal hilum).
発生 — 管ができ、回り、戻って固定されるIntestinum primitivum
第4週、胚の体が頭尾方向と左右に折れ曲がり、卵黄嚢の上部の内胚葉が取り込まれて原始腸管になる。前端は口咽頭膜、後端は総排泄腔膜で閉じ、中央は卵黄腸管で卵黄嚢とつながる。上皮と腺(肝細胞・膵の細胞も)は内胚葉、筋層・結合組織・漿膜は臓側中胚葉から作られる。
| 区分 | できるもの | 動脈 |
|---|---|---|
| 前腸 | 咽頭〜十二指腸(大十二指腸乳頭まで)・肝・胆嚢・膵、呼吸器 | 腹腔動脈 |
| 中腸 | 十二指腸の残り〜横行結腸の右2/3 | 上腸間膜動脈 |
| 後腸 | 横行結腸の左1/3〜肛門管の上部、膀胱・尿生殖洞(総排泄腔から) | 下腸間膜動脈 |
中腸は急に伸びて上腸間膜動脈を軸とするループを作り、第6週に腹腔に収まりきらなくなって臍帯の中へ出る(生理的臍帯ヘルニア)。ループは正面から見て反時計回りに合計270°回る——臍帯内で90°、第10週に腹腔へ戻るときに180°。最後に戻る盲腸は肝の下から右腸骨窩へ下り、上行・下行結腸の間膜は後腹壁に癒合する。

270°の回転だけで、成人の配置がほぼ全部説明できる。十二指腸は上腸間膜動脈の後ろを、横行結腸は前を通る。腸間膜根は左上から右下へ斜めに付き、盲腸は右下に来る。回転の途中で止まったり逆に回ったりすると、何がどこに来るかも予測できる。
この時期の異常(臨床で出会う型):
| 異常 | 何が起きたか | どう現れるか |
|---|---|---|
| Meckel 憩室 | 卵黄腸管の根元が残る(人口の約2%)。回盲弁から約60 cm の回腸 | 胃粘膜を含むと潰瘍から出血(小児の無痛性下血)、炎症・腸重積 |
| 臍帯ヘルニア | 生理的ヘルニアが戻らない。腸が羊膜と腹膜の袋に包まれて臍から出る | 染色体異常などの合併が多い |
| 腹壁破裂 | 臍の右の腹壁の欠損から腸が出る。袋は無い | 腸が羊水にさらされて傷む |
| 腸回転異常 | 回転が足りない・逆に回る(非回転では結腸が左、小腸が右)。盲腸が肝の下に残ることもある | 中腸軸捻転:新生児の胆汁性嘔吐は緊急。肝下の盲腸では虫垂炎が右上腹部痛になる |
| 十二指腸閉鎖・狭窄 | 一度ふさがった内腔の再開通が起こらない | 胆汁性嘔吐、X 線の double bubble。Down 症候群に多い |
English version
Core
In week 4 the embryo folds head-to-tail and side-to-side, and the upper endoderm of the yolk sac is taken in as the primitive gut. It is closed in front by the oropharyngeal membrane and behind by the cloacal membrane, and its middle stays joined to the yolk sac by the vitelline duct. The epithelium and glands (including liver and pancreatic cells) come from endoderm; muscle, connective tissue and serosa from splanchnic mesoderm.
| Part | Derivatives | Artery |
|---|---|---|
| Foregut | Pharynx to duodenum (as far as the major papilla), liver, gallbladder, pancreas, respiratory system | Coeliac trunk |
| Midgut | Rest of duodenum to right two thirds of transverse colon | Superior mesenteric artery |
| Hindgut | Left third of transverse colon to upper anal canal; bladder and urogenital sinus (from the cloaca) | Inferior mesenteric artery |
The midgut lengthens fast and forms a loop around the superior mesenteric artery. In week 6 it no longer fits in the abdomen and moves into the umbilical cord (physiological umbilical herniation). The loop turns 270° anticlockwise in total, seen from the front — 90° in the cord and 180° on returning to the abdomen in week 10. The caecum returns last and descends from under the liver to the right iliac fossa, and the mesenteries of the ascending and descending colon fuse with the posterior wall.
Going further
This one 270° rotation explains almost the whole adult layout. The duodenum passes behind the superior mesenteric artery and the transverse colon in front. The mesenteric root runs obliquely from upper left to lower right, and the caecum ends up at the lower right. If rotation stops or goes the wrong way, you can predict where each part will lie.
In the clinic
Anomalies of this stage met in clinical practice:
| Anomaly | What happened | How it shows |
|---|---|---|
| Meckel’s diverticulum | The root of the vitelline duct remains (about 2% of people), on the ileum about 60 cm from the ileocaecal valve | If it contains gastric mucosa, ulcer bleeding (painless rectal bleeding in children); inflammation, intussusception |
| Omphalocele | Physiological herniation fails to return; bowel comes out at the umbilicus in a sac of amnion and peritoneum | Often with chromosomal and other anomalies |
| Gastroschisis | Bowel comes out through a wall defect to the right of the umbilicus, with no sac | Bowel is damaged by exposure to amniotic fluid |
| Malrotation | Too little or reversed rotation (in non-rotation the colon lies on the left and small bowel on the right); the caecum may stay under the liver | Midgut volvulus: bilious vomiting in a newborn is an emergency. With a subhepatic caecum, appendicitis gives right upper pain |
| Duodenal atresia / stenosis | The lumen, once filled in, fails to reopen | Bilious vomiting, “double bubble” on X-ray; more common in Down syndrome |
食道Oesophagus
咽頭(C6)から胃の噴門(Th11)まで、約25cm。頸部・胸部・腹部の3部。
3か所の生理的狭窄——①起始部(輪状軟骨、C6)②大動脈弓と左気管支の交差(Th4/5)③横隔膜食道裂孔(Th10)。異物と腐食性食道炎はこの3か所に起きるので、必ず言えるようにする。
English version
Core
From the pharynx (C6) to the cardia of the stomach (Th11), about 25 cm, in cervical, thoracic and abdominal parts.
Three physiological constrictions — ① the origin (cricoid cartilage, C6) ② the crossing of the aortic arch and left bronchus (Th4/5) ③ the oesophageal hiatus of the diaphragm (Th10). Foreign bodies and corrosive oesophagitis occur at these three, so be able to name them.
食道口Ostium oesophageum
胃の入口。食道が胃へ開く孔で、噴門 cardia にあたる。
English version
Core
The entrance of the stomach: the orifice by which the oesophagus opens into it — the cardia.
噴門口Ostium cardiacum
食道と胃の境の孔。Th11 の高さ、正中よりやや左。
解剖学的な括約筋は無く、横隔膜脚・His 角・腹腔内食道の陽圧で逆流を防ぐ。ここが緩むと胃食道逆流症になる。
English version
Core
The orifice at the junction of oesophagus and stomach, at Th11, a little left of the midline.
There is no anatomical sphincter; reflux is prevented by the crura of the diaphragm, the angle of His and the positive pressure on the abdominal oesophagus. When this becomes lax, gastro-oesophageal reflux disease follows.
噴門部Pars cardiaca
噴門口を取り巻く狭い帯状の部分。粘膜には粘液のみを出す噴門腺がある。
English version
Core
The narrow band encircling the cardiac orifice. The mucosa carries cardiac glands, secreting mucus only.
胃底Fundus gastricus
噴門より上に膨らむドーム。名前に反して「底」ではなく最上部にある。
立位ではここに空気が溜まるので、胸部X線で左横隔膜下の胃泡として写る。
English version
Core
The dome bulging above the cardia. Despite the name it is not the "floor" but the highest part.
Air collects here in the standing position, and it appears on a chest radiograph as the gastric bubble beneath the left dome of the diaphragm.
胃体Corpus gastricum
胃底と幽門部の間の大部分。胃底腺(壁細胞・主細胞)が集まるので、酸とペプシノゲンはここで作られる。
English version
Core
The large part between fundus and pyloric part. The fundic glands (parietal and chief cells) are concentrated here, so acid and pepsinogen are made in this region.
大弯Curvatura major
胃の左下の長い凸縁。大網が垂れ下がり、胃大網動脈が走る。
English version
Core
The long convex border on the lower left. The greater omentum hangs from it and the gastro-omental arteries run along it.
小弯Curvatura minor
胃の右上の短い凹縁。小網が肝臓へ張り、胃動脈が走る。
途中の切れ込みが角切痕で、胃体と幽門部の境になる。胃潰瘍と胃癌は小弯に多い。
English version
Core
The short concave border on the upper right. The lesser omentum passes from it to the liver and the gastric arteries run along it. The notch along it is the angular incisure, the boundary of body and pyloric part.
Gastric ulcer and gastric carcinoma are commonest on the lesser curvature.
幽門括約筋Musculus sphincter pyloricus
幽門で輪走筋が厚く肥厚した、本物の括約筋。胃内容の十二指腸への排出を調節する。
外からは幽門前静脈を目印に触れる。乳児で肥厚するのが肥厚性幽門狭窄症で、噴水状嘔吐を起こす。
English version
Core
A true sphincter, formed by a thickening of the circular muscle at the pylorus, regulating the emptying of the stomach into the duodenum. From outside it is found by the prepyloric vein.
Hypertrophy in infancy is hypertrophic pyloric stenosis, causing projectile vomiting.
十二指腸上部Pars superior duodeni
幽門から続く第1部(L1)。始まりの約2cmは腹膜に覆われ可動で、X線で十二指腸球部として写る。
十二指腸潰瘍の9割はここ。4部のうちここだけが腹腔内で、他は後腹膜。
English version
Core
The first part, continuing from the pylorus (L1). The first 2.5 cm is covered by peritoneum and mobile, and appears radiologically as the duodenal cap. Nine tenths of duodenal ulcers are here.
Of the four parts, this alone is intraperitoneal; the rest are retroperitoneal.
十二指腸下行部Pars descendens duodeni
L1〜L3 を右側で下る第2部。後腹膜。膵頭を抱え込む。
総胆管と主膵管がここへ開くので、胆道と膵の出口として重要。
English version
Core
The second part, descending on the right from L1 to L3. Retroperitoneal. It embraces the head of the pancreas.
The common bile duct and main pancreatic duct open into it, so it matters as the outlet of the biliary tree and the pancreas.
大十二指腸乳頭Papilla duodeni major
下行部の後内側壁にある隆起(Vater 乳頭)。総胆管と主膵管が合流して開く。
出口をOddi 括約筋が締める。ここに石が嵌まると胆道と膵管の両方が詰まる——胆石性膵炎の仕組み。ERCP の標的でもある。
English version
Core
The elevation on the posteromedial wall of the descending part (the papilla of Vater), where the common bile duct and the main pancreatic duct join and open, the outlet closed by the sphincter of Oddi.
A stone impacted here blocks both the biliary and the pancreatic duct — the mechanism of gallstone pancreatitis. It is also the target of ERCP.
十二指腸水平部・上行部Pars horizontalis, pars ascendens duodeni
第3部は L3 を左へ水平に横切り、第4部は L2 まで上って十二指腸空腸曲で空腸に移る。
水平部は腹大動脈と上腸間膜動脈に挟まれる。この角が狭いと通過障害を起こす(上腸間膜動脈症候群)。曲を吊るのが Treitz 靭帯で、上部消化管出血と下部消化管出血の境になる。
English version
Core
The third part crosses L3 horizontally to the left and the fourth ascends to L2, becoming jejunum at the duodenojejunal flexure.
The horizontal part is caught between the aorta and the superior mesenteric artery. If that angle is narrow, obstruction results (superior mesenteric artery syndrome).
The flexure is suspended by the ligament of Treitz, the boundary between upper and lower gastrointestinal bleeding.
空腸Jejunum
小腸の上部5分の2。左上腹部に位置する。
回腸との見分けは「壁が厚い・輪状ひだが高く密・血管のアーケードが少なく直細動脈が長い・腸間膜に脂肪が少ない」。標本で見分けるときはこの対比そのものを使う。
English version
Core
The upper two fifths of the small intestine, lying in the left upper abdomen.
Distinguished from the ileum by: thicker wall, tall and close-set circular folds, few vascular arcades with long vasa recta, and little mesenteric fat. On the specimen, it is precisely this contrast that tells them apart.
回腸Ileum
小腸の下部5分の3。右下腹部で盲腸に開く。
空腸に比べ壁が薄く・ひだが低く疎・アーケードが多段で直細動脈が短い・脂肪が多い。Peyer 板が発達する。
English version
Core
The lower three fifths of the small intestine, opening into the caecum in the right lower abdomen.
Compared with the jejunum the wall is thinner, the folds lower and sparser, the arcades multi-tiered with short vasa recta, and there is more fat. Peyer’s patches are well developed.
腸間膜Mesenterium intestinale
空腸・回腸を後腹壁に吊る扇形の二重腹膜。根は約15cm しかないのに、腸側の縁は約6m——この落差が扇の襞をつくる。
根は左上(十二指腸空腸曲)から右下(回盲部)へ斜めに走り、上腸間膜動静脈がこの中を通る。根が短いために腸がねじれるのが腸捻転。
English version
Core
The fan-shaped double fold of peritoneum slinging jejunum and ileum from the posterior abdominal wall. The root is only about 15 cm while the intestinal border is about 6 m — and that difference creates the pleats of the fan.
The root runs obliquely from upper left (the duodenojejunal flexure) to lower right (the ileocaecal region), and the superior mesenteric vessels run within it.
It is because the root is short that the bowel twists — volvulus.
盲腸Caecum
大腸の起始部、右腸骨窩にある袋。回腸が回盲弁を通して開く。腹膜に完全に覆われるが、腸間膜を持たない。
English version
Core
The pouch at the beginning of the large intestine, in the right iliac fossa, into which the ileum opens through the ileocaecal valve.
It is completely covered by peritoneum but has no mesentery.
虫垂Appendix vermiformis
盲腸の後内側壁から出る細い盲管。位置は個人差が大きい(骨盤位・回腸後位など)が、根元だけは一定——3本の結腸ヒモが集まる点。
体表の目安は McBurney 点(右上前腸骨棘と臍を結ぶ線の外側1/3)。標本ではヒモをたどって根元を出すのが正解の手順。
English version
Core
The narrow blind tube arising from the posteromedial wall of the caecum. Its position varies greatly between individuals (pelvic, retro-ileal and others), but its base alone is constant — the point at which the three taeniae converge.
The surface marking is McBurney’s point (the outer third of the line from the right anterior superior iliac spine to the umbilicus). On the specimen, the correct procedure is to follow a taenia and bring out the base.
上行結腸Colon ascendens
盲腸から右側腹部を上る。後腹膜(二次的)で可動性がない。
English version
Core
Ascends the right flank from the caecum. Secondarily retroperitoneal and immobile.
右結腸曲(肝弯曲)Flexura coli dextra
肝右葉の下で前内側へ折れ曲がる。左結腸曲より低い位置にある。
English version
Core
Beneath the right lobe of the liver it turns anteromedially. It lies lower than the left colic flexure.
横行結腸Colon transversum
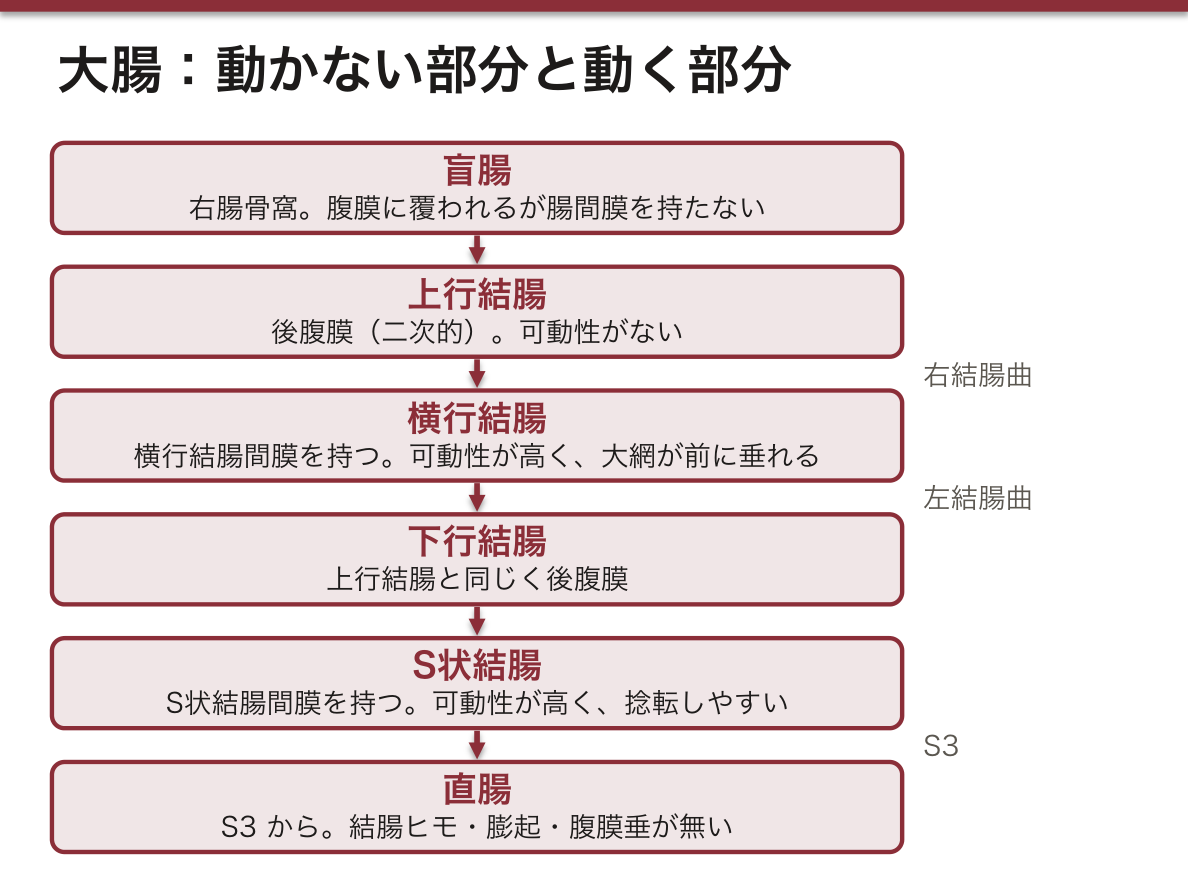
左右の結腸曲を結ぶ。横行結腸間膜を持つので腹腔内・可動性が高い。大網が前に垂れる。
English version
Core
Joins the two colic flexures. Having a transverse mesocolon it is intraperitoneal and highly mobile. The greater omentum hangs in front of it.
左結腸曲(脾弯曲)Flexura coli sinistra
脾の下で鋭く折れ曲がる。右より高く、より鋭い。横隔結腸ヒダで横隔膜に吊られる。
ここは上腸間膜動脈と下腸間膜動脈の境(分水嶺)で、虚血性大腸炎の好発部位。

English version
Core
Turns sharply beneath the spleen. Higher and sharper than the right, and suspended from the diaphragm by the phrenicocolic ligament.
It is the boundary (watershed) between the superior and inferior mesenteric arteries and the site of predilection of ischaemic colitis.
下行結腸Colon descendens
左側腹部を下る。上行結腸と同じく後腹膜。
English version
Core
Descends the left flank. Retroperitoneal, like the ascending colon.
S状結腸Colon sigmoideum
左腸骨窩から骨盤へ入り、S3 で直腸に移る。S状結腸間膜を持ち可動性が高い。
可動性が高く根が狭いため捻転を起こしやすい。憩室の好発部位でもある。
English version
Core
Passes from the left iliac fossa into the pelvis and becomes rectum at S3. Having a sigmoid mesocolon it is highly mobile.
Being mobile on a narrow root, it is prone to volvulus. It is also the site of predilection of diverticula.
大網ヒモTaenia omentalis
結腸の縦走筋が集まった3本のヒモの1本で、大網が付く線に沿う。他は間膜ヒモと自由ヒモ。
ヒモは大腸を見分ける決め手(小腸には無い)。ヒモが縮むので腸は結腸膨起に膨らみ、半月ひだができる。3本は虫垂の根で合する。
English version
Core
One of the three bands into which the longitudinal muscle of the colon is gathered, following the line of attachment of the greater omentum; the others are the mesocolic and free taeniae.
The taeniae are the decisive mark of the large intestine (the small intestine has none). Because they are short the bowel bulges into haustra and semilunar folds form. The three converge at the base of the appendix.
直腸Rectum
S3 からS状結腸に続き、肛門管に至る約12cm。名前に反してまっすぐではない——仙骨曲と会陰曲の2つの前後屈がある。
結腸ヒモ・膨起・腹膜垂を持たないことでS状結腸と区別する。
English version
Core
About 12 cm, continuing from the sigmoid colon at S3 to the anal canal. Despite the name it is not straight — it has two anteroposterior curves, sacral and perineal.
It is distinguished from the sigmoid colon by having no taeniae, haustra or appendices epiploicae.
直腸膨大部Ampulla recti
直腸の下部の膨らんだ部分。便を溜める場所で、ここが伸展されると便意が起きる。
English version
Core
The dilated lower part of the rectum. The place where faeces are stored; distension of it produces the call to stool.
直腸横ひだPlicae transversae recti
直腸内腔に張り出す3枚の半月状のひだ(Houston 弁)。上と下は左、中央は右から出る。
中央のひだは腹膜反転部の高さにあたり、直腸鏡の目印になる。
English version
Core
Three semilunar folds projecting into the lumen of the rectum (Houston’s valves). The upper and lower arise on the left, the middle on the right.
The middle fold lies at the level of the peritoneal reflection and is a landmark at proctoscopy.
肛門管Canalis analis
直腸膨大部から肛門までの約4cm。内腔に肛門柱と肛門弁が並ぶ。
櫛状線(歯状線)が境界——上は内胚葉由来で自律神経支配・痛みを感じず内痔核ができ、下は外胚葉由来で陰部神経支配・鋭い痛みがあり外痔核ができる。この上下の対比がそのまま要点になる。
English version
Core
About 4 cm from the rectal ampulla to the anus, with the anal columns and valves lining its lumen.
The pectinate (dentate) line is the boundary — above it is endodermal, with autonomic supply, painless, and the site of internal piles; below it is ectodermal, with pudendal supply, sharply painful, and the site of external piles. This contrast above and below is the key point as it stands.
肛門Anus
消化管の出口。内肛門括約筋(平滑筋・不随意)と外肛門括約筋(横紋筋・随意、陰部神経)の二重で締まる。
English version
Core
The outlet of the digestive tract, closed by a double sphincter — the internal (smooth muscle, involuntary) and the external (striated, voluntary, pudendal nerve).
まとめ
| 食道 — 3部・3狭窄 | C6(輪状軟骨の下縁)から Th11(胃の噴門)まで、約25cm。 |
|---|---|
| 胃 — 部位・弯・壁 | 2つの口:ostium cardiacum(噴門・Th11 左)と ostium pyloricum(幽門・L1 右)。 |
| 十二指腸 — C字の4部 | 長さ約25cm(指12本ぶん)。膵頭を抱くC字で、大部分が後腹膜(二次的)。 |
| 空腸と回腸 — 見分け方 | 十二指腸空腸曲から回盲弁まで約6〜7m。 |
| 大腸 — 外から見て分かる3つの特徴 | 回盲弁から肛門まで約1.5m。Caecum → colon ascendens → flexura coli dextra → colon transversum → flexur… |
| 直腸と肛門管 — 歯状線で全部が変わる | Rectum(S3 から)は仙骨の前を下り、ampulla recti で膨らんでから後下方へ曲がって canalis analis(約4cm)となり anus に終わる。 |
| 内臓学の総論 — 管腔臓器と実質臓器 | 内臓学は、胸腔・腹腔・骨盤腔にあり、漿膜(胸膜・心膜・腹膜)と関わる臓器を扱う。 |
| 発生 — 管ができ、回り、戻って固定される | 第4週、胚の体が頭尾方向と左右に折れ曲がり、卵黄嚢の上部の内胚葉が取り込まれて原始腸管になる。 |
| 食道 | 咽頭(C6)から胃の噴門(Th11)まで、約25cm。 |
| 食道口 | 胃の入口。食道が胃へ開く孔で、噴門 cardia にあたる。 |
| 噴門口 | 食道と胃の境の孔。Th11 の高さ、正中よりやや左。 |
| 噴門部 | 噴門口を取り巻く狭い帯状の部分。粘膜には粘液のみを出す噴門腺がある。 |
| 胃底 | 噴門より上に膨らむドーム。名前に反して「底」ではなく最上部にある。 |
| 胃体 | 胃底と幽門部の間の大部分。胃底腺(壁細胞・主細胞)が集まるので、酸とペプシノゲンはここで作られる。 |
| 大弯 | 胃の左下の長い凸縁。大網が垂れ下がり、胃大網動脈が走る。 |
| 小弯 | 胃の右上の短い凹縁。小網が肝臓へ張り、胃動脈が走る。 |
| 幽門括約筋 | 幽門で輪走筋が厚く肥厚した、本物の括約筋。 |
| 十二指腸上部 | 幽門から続く第1部(L1)。始まりの約2cmは腹膜に覆われ可動で、X線で十二指腸球部として写る。 |
| 十二指腸下行部 | L1〜L3 を右側で下る第2部。後腹膜。 |
| 大十二指腸乳頭 | 下行部の後内側壁にある隆起(Vater 乳頭)。 |
| 十二指腸水平部・上行部 | 第3部は L3 を左へ水平に横切り、第4部は L2 まで上って十二指腸空腸曲で空腸に移る。 |
| 空腸 | 小腸の上部5分の2。左上腹部に位置する。 |
| 回腸 | 小腸の下部5分の3。右下腹部で盲腸に開く。 |
| 腸間膜 | 空腸・回腸を後腹壁に吊る扇形の二重腹膜。 |
| 盲腸 | 大腸の起始部、右腸骨窩にある袋。回腸が回盲弁を通して開く。 |
| 虫垂 | 盲腸の後内側壁から出る細い盲管。位置は個人差が大きい(骨盤位・回腸後位など)が、根元だけは一定——3本の結腸ヒモが集まる点。 |
| 上行結腸 | 盲腸から右側腹部を上る。後腹膜(二次的)で可動性がない。 |
| 右結腸曲(肝弯曲) | 肝右葉の下で前内側へ折れ曲がる。左結腸曲より低い位置にある。 |
| 横行結腸 | 左右の結腸曲を結ぶ。横行結腸間膜を持つので腹腔内・可動性が高い。 |
| 左結腸曲(脾弯曲) | 脾の下で鋭く折れ曲がる。右より高く、より鋭い。 |
| 下行結腸 | 左側腹部を下る。上行結腸と同じく後腹膜。 |
| S状結腸 | 左腸骨窩から骨盤へ入り、S3 で直腸に移る。 |
| 大網ヒモ | 結腸の縦走筋が集まった3本のヒモの1本で、大網が付く線に沿う。 |
| 直腸 | S3 からS状結腸に続き、肛門管に至る約12cm。 |
| 直腸膨大部 | 直腸の下部の膨らんだ部分。便を溜める場所で、ここが伸展されると便意が起きる。 |
| 直腸横ひだ | 直腸内腔に張り出す3枚の半月状のひだ(Houston 弁)。 |
| 肛門管 | 直腸膨大部から肛門までの約4cm。内腔に肛門柱と肛門弁が並ぶ。 |
| 肛門 | 消化管の出口。内肛門括約筋(平滑筋・不随意)と外肛門括約筋(横紋筋・随意、陰部神経)の二重で締まる。 |
このノートは医学生が授業の内容を自分の言葉でまとめたもので、診療の判断に使うものではありません。誤りに気づいたらお知らせください。