副腎皮質と性腺のステロイドは、すべてコレステロールから始まる1本の幹から枝分かれする。枝を担当する酵素が決まっているので、どの酵素が欠けると何が足りず、何が余るかが図の上で読める。
先天性副腎皮質過形成は、この樹形図を覚えているかどうかで、丸暗記か理解かが分かれる典型的な題材である。
- 樹形図 — 3本の枝と、共通の幹
- 受容体の側の話 — なぜコルチゾールは腎で働かないのか
- 21-水酸化酵素欠損症 — 樹形図の1か所が詰まると、何が起きるか
- レニンとアルドステロン — 比で見ると、原因の場所が分かる
- コルチゾールは、いつ測るかで意味が変わる
- ステロイドをやめるとき — 眠っている軸は、すぐには起きない
樹形図 — 3本の枝と、共通の幹
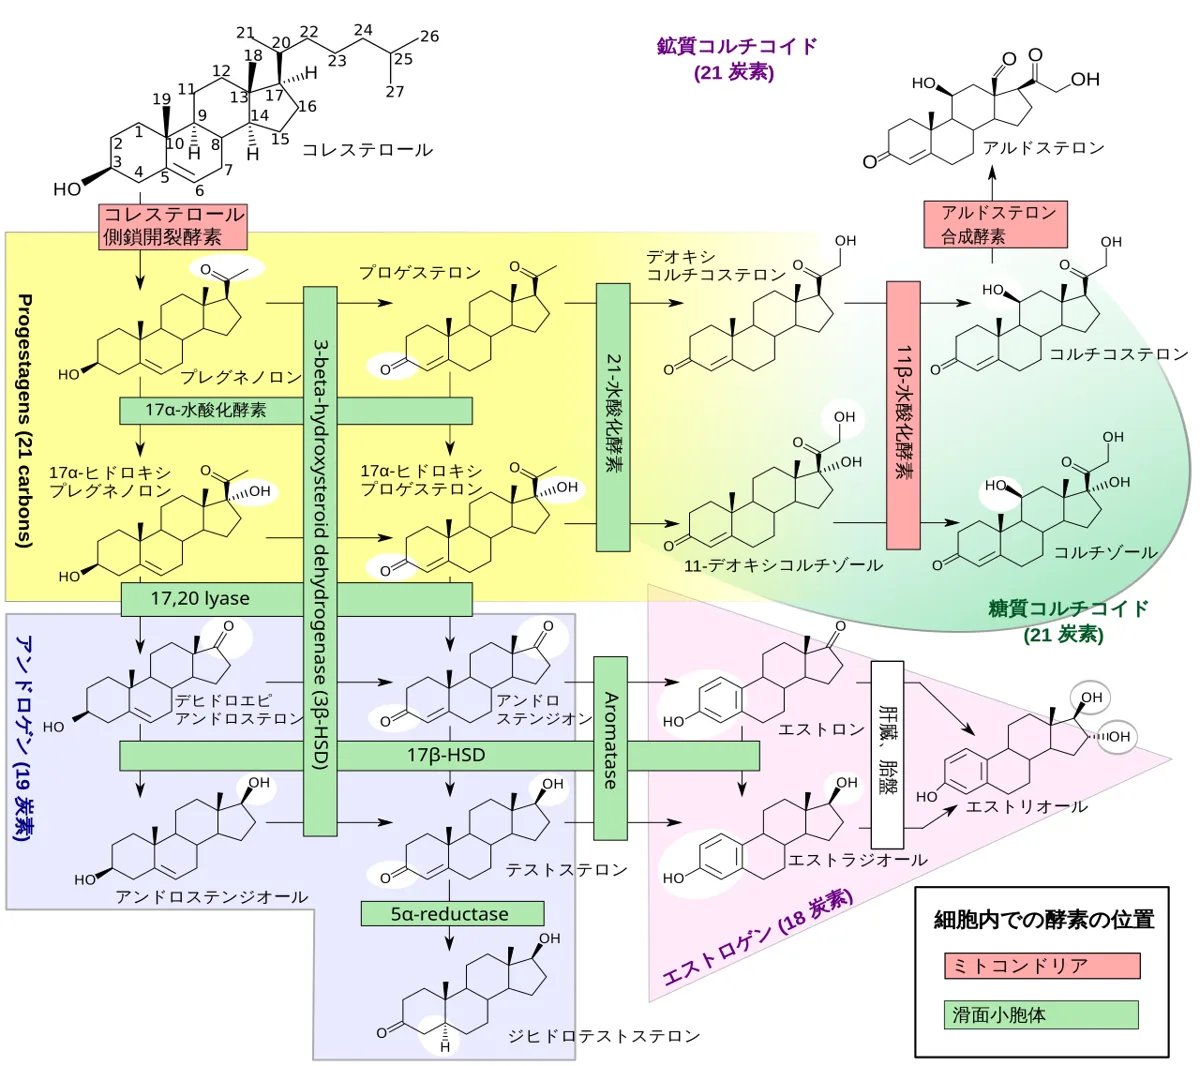
幹:コレステロール →(側鎖切断酵素、律速。副腎皮質刺激ホルモンが促進)→ プレグネノロン
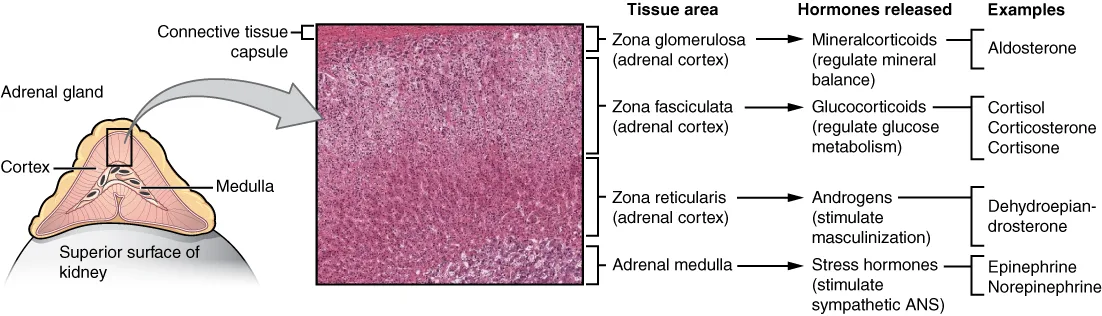
3本の枝(副腎皮質の3層に対応)
| 層 | 作るもの | 枝に必要な酵素 |
|---|---|---|
| 球状層 | アルドステロン | アルドステロン合成酵素(この層にしかない) |
| 束状層 | コルチゾール | 17α水酸化酵素と11β水酸化酵素 |
| 網状層 | 副腎アンドロゲン | 17α水酸化酵素(17,20リアーゼ活性) |
共通して必要な酵素:21水酸化酵素——アルドステロンとコルチゾールの両方の枝で使う。アンドロゲンの枝では使わない。
- 球状層は副甲状腺ホルモンではなくレニン・アンジオテンシン系とカリウムで制御される
- 束状層と網状層は副腎皮質刺激ホルモンで制御される
21水酸化酵素が「2つの枝で使われ、1つの枝では使われない」ことが、最多の先天性副腎皮質過形成の病像をすべて説明する。
21水酸化酵素欠損症(全体の90%以上)
- コルチゾールが作れない → 負のフィードバックが外れ副腎皮質刺激ホルモンが上がる → 副腎が過形成になる
- アルドステロンも作れない → 塩喪失型では低ナトリウム・高カリウム・脱水・ショック(生後1〜2週)
- 行き場を失った前駆体がアンドロゲンの枝へ流れる → 女児の外性器男性化、男児の性早熟
- 診断は17ヒドロキシプロゲステロンの高値(詰まった直前の物質)。新生児マススクリーニングの対象
他の型は、この図の上で位置をずらすだけで導ける。
| 欠損酵素 | アンドロゲン | 血圧 | 理由 |
|---|---|---|---|
| 21水酸化酵素 | 過剰 | 低い | アルドステロンが作れない |
| 11β水酸化酵素 | 過剰 | 高い | 11デオキシコルチコステロンが溜まる(鉱質コルチコイド作用あり) |
| 17α水酸化酵素 | 不足 | 高い | 同上。男児が女性型外性器になる |
高血圧になる2つの型は、いずれも「詰まりの手前に鉱質コルチコイド作用を持つ物質が溜まる」ためである。アンドロゲンが増えるか減るかは、詰まりが分岐点より上流か下流かで決まる。表を覚えるのではなく、図の上で指を動かせばよい。
English version
Core
The trunk: cholesterol → (side-chain cleavage enzyme, rate-limiting, promoted by ACTH) → pregnenolone.
Three branches, corresponding to the three zones of the cortex.
| Zone | Product | Enzyme the branch needs |
|---|---|---|
| Glomerulosa | Aldosterone | Aldosterone synthase (present only in this zone) |
| Fasciculata | Cortisol | 17α-hydroxylase and 11β-hydroxylase |
| Reticularis | Adrenal androgens | 17α-hydroxylase (17,20-lyase activity) |
Needed in common: 21-hydroxylase — used in both the aldosterone and the cortisol branch, and not in the androgen branch.
- The glomerulosa is controlled by the renin–angiotensin system and by potassium.
- The fasciculata and reticularis are controlled by ACTH.
Going further
That 21-hydroxylase is used in two branches and not in the third explains the whole picture of the commonest congenital adrenal hyperplasia.
21-hydroxylase deficiency (over 90 per cent of cases)
- Cortisol cannot be made → negative feedback is released, ACTH rises → the adrenal becomes hyperplastic.
- Aldosterone cannot be made either → in the salt-wasting form, hyponatraemia, hyperkalaemia, dehydration and shock (in the first week or two of life).
- The precursors with nowhere to go flow into the androgen branch → virilisation of the external genitalia in a girl, precocious puberty in a boy.
- The diagnosis is a high 17-hydroxyprogesterone (the substance just before the block). Included in newborn screening.
The other forms are derived simply by shifting position on the same diagram.
| Enzyme lacking | Androgens | Blood pressure | Why |
|---|---|---|---|
| 21-hydroxylase | Excess | Low | Aldosterone cannot be made |
| 11β-hydroxylase | Excess | High | 11-deoxycorticosterone accumulates (it has mineralocorticoid action) |
| 17α-hydroxylase | Deficient | High | The same. A boy has female external genitalia |
Both hypertensive forms accumulate a substance with mineralocorticoid action before the block. Whether the androgens rise or fall depends on whether the block is above or below the branch point. Do not memorise the table — move a finger on the diagram.
受容体の側の話 — なぜコルチゾールは腎で働かないのか
鉱質コルチコイド受容体は、コルチゾールとアルドステロンを区別できない。しかも血中コルチゾール濃度はアルドステロンの1000倍近い。それでも腎でコルチゾールが働かないのは、受容体の手前で酵素が守っているからである。
- 11βヒドロキシステロイド脱水素酵素2型が、腎の尿細管でコルチゾールを不活性なコルチゾンに変える
- アルドステロンはこの酵素の基質にならないので、そのまま受容体に届く
この酵素が働かないと、コルチゾールが鉱質コルチコイドとして作用する。
- 甘草(グリチルリチン)——この酵素を阻害。偽性アルドステロン症(高血圧・低カリウム・代謝性アルカローシス・レニンもアルドステロンも低い)
- 異所性副腎皮質刺激ホルモン症候群——コルチゾールが著明高値で酵素の処理能力を超える
「特異性は受容体ではなく、その手前の代謝で作られている」——この考え方は内分泌学全体に通じる。受容体を厳密にする代わりに、届く前に不活化するほうが設計として簡単だったのだろう。
低カリウム性高血圧を見たとき、レニンとアルドステロンの組で鑑別できる。
| レニン | アルドステロン | 代表 | |
|---|---|---|---|
| 原発性アルドステロン症 | 低い | 高い | 副腎腺腫・過形成 |
| 腎血管性高血圧 | 高い | 高い | 腎動脈狭窄 |
| 偽性アルドステロン症 | 低い | 低い | 甘草・Liddle症候群・Cushing症候群 |
両方が低いことが、この群の決め手である。「アルドステロンが低いのにアルドステロン症状」という矛盾した所見を見たら、受容体側か、酵素側か、チャネル側の異常を考える。
甘草は漢方薬の多くに含まれる——芍薬甘草湯、小柴胡湯、抑肝散など。高齢者が複数の漢方を併用して偽性アルドステロン症を起こすのは実際によくある。浮腫・脱力・血圧上昇・低カリウム血症を見たら、服用薬に漢方が無いかを必ず確かめる。国試でも実務でも問われる線である。
Liddle症候群は上皮性ナトリウムチャネルの機能獲得変異で、受容体を介さずチャネルが開きっぱなしになる。スピロノラクトンは効かず、トリアムテレン・アミロライドが効く——作用点が受容体ではなくチャネルだからである。
English version
Core
The mineralocorticoid receptor cannot distinguish cortisol from aldosterone, and the blood cortisol is nearly a thousand times the aldosterone. That cortisol nevertheless does not act in the kidney is because an enzyme guards the receptor.
- 11β-hydroxysteroid dehydrogenase type 2 converts cortisol to inactive cortisone in the renal tubule.
- Aldosterone is not a substrate of this enzyme and reaches the receptor unchanged.
When the enzyme does not work, cortisol acts as a mineralocorticoid.
- Liquorice (glycyrrhizin) — inhibits the enzyme. Pseudohyperaldosteronism (hypertension, hypokalaemia, metabolic alkalosis, with both renin and aldosterone low).
- Ectopic ACTH syndrome — the cortisol is so high that it exceeds the capacity of the enzyme.
Going further
"Specificity is created not at the receptor but in the metabolism in front of it" — an idea that runs through the whole of endocrinology. Rather than making the receptor strict, it was simpler in design to inactivate the ligand before it arrives.
Seeing hypokalaemic hypertension, the differential is made by the pair of renin and aldosterone.
| Renin | Aldosterone | Example | |
|---|---|---|---|
| Primary aldosteronism | Low | High | Adrenal adenoma or hyperplasia |
| Renovascular hypertension | High | High | Renal artery stenosis |
| Pseudohyperaldosteronism | Low | Low | Liquorice, Liddle syndrome, Cushing’s syndrome |
Both being low is the decisive feature of this group. On seeing the contradictory finding of aldosterone symptoms with a low aldosterone, think of the receptor, the enzyme or the channel.
Liquorice is in many herbal preparations — shakuyakukanzoto, shosaikoto, yokukansan and others. Pseudohyperaldosteronism in an older person taking several herbal medicines together is genuinely common. On seeing oedema, weakness, rising blood pressure and hypokalaemia, always ask whether there is a herbal preparation among the drugs.
Liddle syndrome is a gain-of-function mutation of the epithelial sodium channel, the channel staying open without any receptor. Spironolactone does not work; triamterene and amiloride do — because the site of action is the channel and not the receptor.
21-水酸化酵素欠損症 — 樹形図の1か所が詰まると、何が起きるか
先天性副腎過形成の約 90〜95% を占める。常染色体潜性遺伝(CYP21A2)。
21-水酸化酵素は、コルチゾールとアルドステロンの両方の枝で使われる。止まると、行き場を失った前駆体がアンドロゲンの枝へ流れる。
| ホルモン | どうなるか |
|---|---|
| コルチゾール | 減る → ACTH が上がる → 副腎が過形成する |
| アルドステロン | 減る(塩喪失型) |
| 17-ヒドロキシプロゲステロン | 溜まる(診断の指標) |
| アンドロゲン | 増える |
症状——女児の外性器の男性化・男児は生後2週前後の塩喪失発作(嘔吐・脱水・低ナトリウム・高カリウム・低血糖・ショック)。
新生児マススクリーニングの対象になっている。

「詰まった手前が溜まり、溜まったものは別の道へ流れる」という代謝異常の一般則が、そのまま症状になる。コルチゾールが足りないという欠乏症状と、アンドロゲンが多いという過剰症状が同時に出る(先天代謝異常症の総論の章)——「1つの酵素の欠損で、足りないものと余るものが並ぶ」。
だから電解質の組み合わせが、そのまま診断のきっかけになる。低ナトリウム+高カリウム+脱水の新生児は、アルドステロンが効いていない状態になる(副腎の章)——「幽門狭窄症の脱水とは、電解質の向きが逆になる」。
他の酵素欠損との見分けも、樹形図の位置で決まる。
| 欠損 | 血圧 | 男性化 |
|---|---|---|
| 21-水酸化酵素 | 低い(塩喪失) | する |
| 11β-水酸化酵素 | 高い(デオキシコルチコステロンが溜まる) | する |
| 17α-水酸化酵素 | 高い | しない |
——「血圧と男性化の2つを聞けば、どの段で止まったかが決まる」。
治療はホルモンの補充であって、抑制ではない。グルココルチコイドを補うと ACTH が下がり、結果としてアンドロゲンの産生も減る(副腎皮質ステロイドの章)——「足りないものを足すことが、余っているものを減らすことになる」。
English version
Core
About 90–95 per cent of congenital adrenal hyperplasia. Autosomal recessive (CYP21A2).
21-hydroxylase is used in both the cortisol and the aldosterone branch. Blocked, the precursors with nowhere to go flow into the androgen branch.
| Hormone | What happens |
|---|---|
| Cortisol | Falls → ACTH rises → the adrenal becomes hyperplastic |
| Aldosterone | Falls (the salt-wasting form) |
| 17-hydroxyprogesterone | Accumulates (the diagnostic marker) |
| Androgens | Rise |
Symptoms — virilisation of the external genitalia in a girl; in a boy a salt-losing crisis at about two weeks (vomiting, dehydration, hyponatraemia, hyperkalaemia, hypoglycaemia, shock). Included in newborn screening.
Going further
The general rule of metabolic disease — what is behind the block accumulates, and what accumulates flows down another road — is itself the clinical picture. The deficiency symptoms of too little cortisol and the excess symptoms of too much androgen appear together — one enzyme deficiency putting a shortage and a surplus side by side.
So the combination of electrolytes is itself the way in to the diagnosis. A newborn with hyponatraemia, hyperkalaemia and dehydration is a newborn in whom aldosterone is not working — the electrolytes run in the opposite direction from the dehydration of pyloric stenosis.
The distinction from the other enzyme deficiencies is decided by position on the tree.
| Deficiency | Blood pressure | Virilisation |
|---|---|---|
| 21-hydroxylase | Low (salt-wasting) | Yes |
| 11β-hydroxylase | High (deoxycorticosterone accumulates) | Yes |
| 17α-hydroxylase | High | No |
Ask two things — the blood pressure and the virilisation — and the level of the block is settled.
The treatment is replacement, not suppression. Replacing the glucocorticoid lowers the ACTH and thereby reduces the androgen production too — supplying what is lacking becomes the way of reducing what is in surplus.
レニンとアルドステロン — 比で見ると、原因の場所が分かる
アルドステロンは、本来レニンの指令で出る——レニン → アンジオテンシンI → II → 副腎皮質球状層。
だから2つの値の関係を見れば、命令の側が原因か、出す側が原因かが分かる。
| レニン | アルドステロン | 読み方 | 例 |
|---|---|---|---|
| 低い | 高い | 副腎が勝手に出している | 原発性アルドステロン症 |
| 高い | 高い | 命令が過剰 | 腎血管性高血圧・心不全・肝硬変・利尿薬 |
| 低い | 低い | 他の鉱質コルチコイド作用 | Cushing 症候群・甘草(偽性アルドステロン症) |
共通する所見——高血圧・低カリウム血症・代謝性アルカローシス。
アルドステロン/レニン比(ARR)が、原発性アルドステロン症のスクリーニングになる。

「1つを測るのではなく、上流と下流を組で測る」という発想が、内分泌検査の基本形になる。ホルモンの絶対値ではなく、指令との釣り合いが答えを出す(フィードバックの章)——「甲状腺で TSH と FT4 を組で見るのと、同じ論理になる」。
原発性アルドステロン症が「二次性高血圧の最多」であることは、頻度の面で重要になる。治せる高血圧なので、若年発症・低カリウム・治療抵抗性のときに探す(副腎の章)——「片側なら手術で治り、両側なら選択的アルドステロン拮抗薬になる」。
測る前に薬を整理する必要がある。ミネラルコルチコイド受容体拮抗薬・β遮断薬・ACE 阻害薬・利尿薬が、レニンとアルドステロンの両方を動かす(降圧薬の章)——「検査値を作っているのが薬だという可能性を、先に潰す」。
甘草による偽性アルドステロン症は、受容体の側の話になる。グリチルリチンが 11β-水酸化ステロイド脱水素酵素2 を阻害し、コルチゾールが鉱質コルチコイド受容体を刺激してしまう(この章の受容体の項)——「アルドステロンは低いのに、アルドステロンの症状が出る」。
だから漢方薬を飲んでいる高齢者の低カリウム血症は、まず甘草を疑う(薬が臓器を壊す章)——「市販薬にも入っているので、お薬手帳だけでは分からない」。
English version
Core
Aldosterone is properly released on the command of renin — renin → angiotensin I → II → the zona glomerulosa. So the relation of the two values shows whether the fault is with the command or with the gland.
| Renin | Aldosterone | Read as | Example |
|---|---|---|---|
| Low | High | The adrenal is releasing it on its own | Primary aldosteronism |
| High | High | Excessive command | Renovascular hypertension, heart failure, cirrhosis, diuretics |
| Low | Low | Some other mineralocorticoid action | Cushing’s syndrome, liquorice (pseudohyperaldosteronism) |
Common findings — hypertension, hypokalaemia, metabolic alkalosis. The aldosterone/renin ratio (ARR) is the screening test for primary aldosteronism.
Going further
"Do not measure one; measure the upstream and the downstream as a pair" is the basic form of endocrine testing. The answer comes not from the absolute value of a hormone but from its balance with the command — the same logic as reading TSH with FT4 in the thyroid.
That primary aldosteronism is the commonest secondary hypertension matters by frequency. It is a curable hypertension, so look for it in a young patient, with hypokalaemia, or where treatment is resistant — unilateral disease is cured by surgery; bilateral is treated with a selective aldosterone antagonist.
The drugs must be sorted out before measuring. Mineralocorticoid receptor antagonists, beta blockers, ACE inhibitors and diuretics all move both renin and aldosterone — exclude first the possibility that the drugs are creating the result.
Pseudohyperaldosteronism from liquorice is a matter of the receptor side. Glycyrrhizin inhibits 11β-hydroxysteroid dehydrogenase 2 and cortisol stimulates the mineralocorticoid receptor — the aldosterone is low yet the symptoms of aldosterone appear.
So in hypokalaemia in an older person taking herbal medicine, suspect liquorice first — it is in over-the-counter preparations too, so the medication record alone will not show it.
コルチゾールは、いつ測るかで意味が変わる
コルチゾールは朝方に最も高く、深夜に最も低いという日内変動を持つ。変動幅が大きいので、1回の測定値だけでは診断にならない。
- 朝(6〜8 時)が頂点——起床前後で最高になる
- 深夜(23〜24 時)が底——健常なら検出限界に近いところまで下がる
- ストレス・急病・手術で跳ね上がる——入院中の値は解釈できない
だから検査は「高いか低いか」ではなく、本来あるべき動きが残っているかを見る形で組まれている。
| 過剰を疑う | 深夜唾液コルチゾール/1 mg デキサメサゾン抑制試験/24 時間尿中遊離コルチゾール | 底が無くなっていないか・抑制がかかるかを見る |
| 不足を疑う | 早朝コルチゾール/ACTH 負荷試験 | 頂点が立つかを見る |
測っているのが「総コルチゾール」であることが、思わぬ落とし穴になる。
血中のコルチゾールは 90% 以上がコルチゾール結合グロブリン(CBG)とアルブミンに結合していて、作用するのは遊離型だけである。ところが通常の測定は総量を測っている。
- 経口エストロゲン・妊娠——CBG が増えるので総コルチゾールは高く出るが、遊離型は正常。Cushing 症候群と誤りうる
- ネフローゼ症候群・肝硬変・重症疾患——CBG とアルブミンが減り、総コルチゾールは低く出る。副腎不全と誤りうる
唾液コルチゾールが使われるのはこのためである——唾液には遊離型しか移行しないので、結合蛋白の影響を受けない。しかも自宅で深夜に採れる。
⚠️ 偽陽性を作るものを先に潰す。デキサメサゾン抑制試験が抑制されないとき、Cushing 症候群と決めつける前にうつ病・アルコール多飲・肥満・睡眠障害(偽 Cushing 状態)と、CYP3A4 誘導薬(デキサメサゾンが速く分解されて濃度が上がらない)を確認する。
救急で副腎不全を疑ったら、コルチゾールを採血してから、結果を待たずにヒドロコルチゾンを投与する。採血さえしておけば、後から診断はつく。
English version
Core
Cortisol has a diurnal rhythm, highest in the early morning and lowest at midnight. The swing is large, so a single value is not a diagnosis.
- The peak is in the morning (06:00–08:00), around waking.
- The trough is at midnight — in health it falls close to the limit of detection.
- It leaps with stress, acute illness and surgery — a value obtained in hospital cannot be interpreted.
So the tests are constructed not around high or low but around whether the movement that should be there remains.
| Suspecting | Test | What is being looked at |
|---|---|---|
| Excess | Late-night salivary cortisol / 1 mg dexamethasone suppression / 24-hour urinary free cortisol | Whether the trough has disappeared; whether it suppresses |
| Deficiency | Early morning cortisol / ACTH stimulation test | Whether the peak appears |
Going further
That what is measured is total cortisol creates an unexpected pitfall. Over 90 per cent of the cortisol in blood is bound to cortisol-binding globulin (CBG) and albumin, and only the free fraction acts. Yet the ordinary assay measures the total.
- Oral oestrogen, pregnancy — CBG rises, so the total cortisol reads high while the free is normal. It can be mistaken for Cushing’s syndrome.
- Nephrotic syndrome, cirrhosis, severe illness — CBG and albumin fall and the total reads low. It can be mistaken for adrenal insufficiency.
This is why salivary cortisol is used — only the free fraction passes into saliva, so it is unaffected by the binding proteins. And it can be collected at home at midnight.
⚠️ Exclude the causes of a false positive first. When the dexamethasone suppression test does not suppress, before concluding Cushing’s syndrome, check for depression, heavy drinking, obesity and sleep disorder (pseudo-Cushing states), and for CYP3A4-inducing drugs (dexamethasone is degraded quickly and the level does not rise).
In the clinic
Suspecting adrenal insufficiency in an emergency, take blood for cortisol and then give hydrocortisone without waiting for the result. Provided the sample has been taken, the diagnosis can be made afterwards.
ステロイドをやめるとき — 眠っている軸は、すぐには起きない
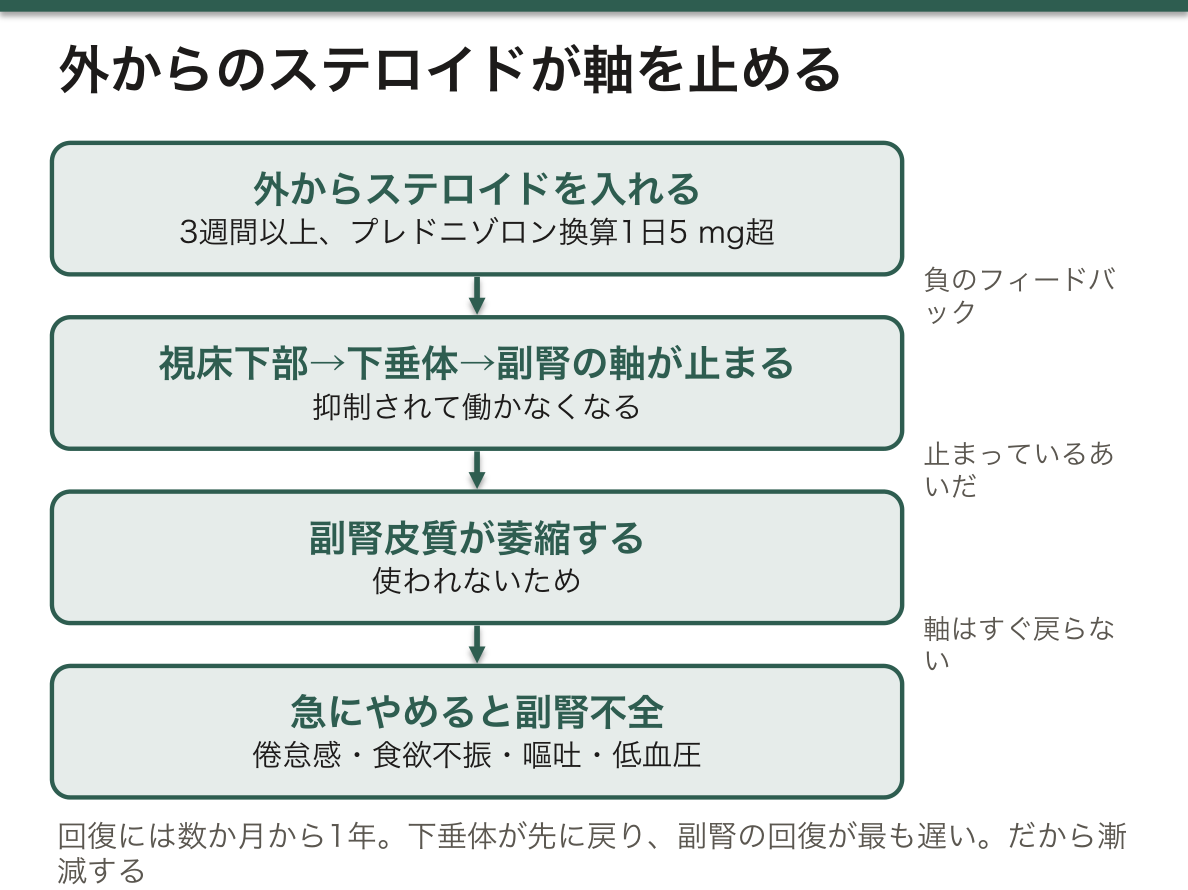
外からステロイドを入れると、負のフィードバックで視床下部→下垂体→副腎の軸が止まる。止まっているあいだ、副腎皮質は使われないので萎縮する。
問題は、薬をやめたときに軸がすぐには戻らないことである。
- 3 週間以上プレドニゾロン換算 1 日 5 mg 超を続けたら、抑制されていると考える
- 回復には数か月から1年かかる。下垂体が先に戻り、副腎の回復が最も遅い
- だから中止は漸減する。急にやめると副腎不全の症状(倦怠感・食欲不振・嘔吐・低血圧)が出る
吸入・外用・関節内注射でも起こりうる。「飲み薬ではないから大丈夫」とは言えない。
漸減には2つの別々の目的が混ざっていることを分けて考える。
| もとの病気の再燃を防ぐ | 生理的な量(プレドニゾロン 5 mg 相当)より上での減量 | 病気の活動性を見ながら下げる。速さは疾患ごとに決まっている |
| 軸を起こす | 生理的な量より下での減量 | ここからが本番。ヒドロコルチゾンに替えて、朝1回にし、ゆっくり減らす |
⚠️ 減量が終わっても、しばらくは「隠れた副腎不全」が残る。普段は足りていても、感染・手術・外傷で必要量が跳ね上がったときに足りなくなる。そこでストレス時には増量する(sick day rules)ことを、患者に必ず伝える。発熱時は 2〜3 倍、嘔吐して飲めないときは注射、と具体的に決めておく。
離脱症状は副腎不全とは別に存在する。コルチゾール値が正常でも、関節痛・倦怠感・気分の落ち込みが出る。受容体の側が高濃度に慣れてしまっているためで、検査値が正常なら大丈夫とは言い切れない。
回復の確認には早朝コルチゾールを使い、判断がつかなければ ACTH 負荷試験を行う。
ステロイドを長期に飲んでいる患者が、手術・内視鏡・重症感染で来たら、投与量を増やす必要がないかを必ず考える。見落とすと術中の原因不明の低血圧になる。
English version
Core
Giving steroid from outside stops the hypothalamic–pituitary–adrenal axis by negative feedback. While it is stopped the adrenal cortex is unused and atrophies. The problem is that the axis does not return at once when the drug is stopped.
- Assume suppression after three weeks of more than the equivalent of 5 mg of prednisolone a day.
- Recovery takes months to a year. The pituitary returns first and the adrenal last.
- So stopping must be by tapering. Stopped abruptly, the symptoms of adrenal insufficiency appear (malaise, anorexia, vomiting, hypotension).
- It can occur with inhaled, topical and intra-articular steroid too. "It is not a tablet, so it is safe" cannot be said.
Going further
Two separate purposes are mixed together in a taper, and they should be thought of separately.
| Purpose | Range | How |
|---|---|---|
| Prevent relapse of the original disease | Above the physiological dose (equivalent to 5 mg prednisolone) | Reduce while watching the activity of the disease. The rate is set by the disease |
| Wake the axis | Below the physiological dose | This is the real work. Change to hydrocortisone, once in the morning, and reduce slowly |
⚠️ Even after the taper is finished, a hidden adrenal insufficiency remains for a time. It suffices in ordinary life but not when the requirement leaps in infection, surgery or trauma. So always tell the patient to increase the dose under stress (sick day rules) — set it out concretely: two or three times the dose with fever, injection if vomiting prevents swallowing.
Withdrawal symptoms exist separately from adrenal insufficiency. With a normal cortisol there may still be arthralgia, malaise and low mood, the receptor side having grown used to a high concentration. A normal value does not guarantee that all is well.
Recovery is confirmed with an early morning cortisol, and where that is equivocal, with an ACTH stimulation test.
In the clinic
When a patient on long-term steroid presents for surgery, endoscopy or with severe infection, always consider whether the dose needs to be increased. Missed, it becomes unexplained intraoperative hypotension.
まとめ
| 樹形図 — 3本の枝と、共通の幹 | 幹:コレステロール →(側鎖切断酵素、律速。 |
|---|---|
| 受容体の側の話 — なぜコルチゾールは腎で働かないのか | 鉱質コルチコイド受容体は、コルチゾールとアルドステロンを区別できない。 |
| 21-水酸化酵素欠損症 — 樹形図の1か所が詰まると、何が起きるか | 先天性副腎過形成の約 90〜95% を占める。 |
| レニンとアルドステロン — 比で見ると、原因の場所が分かる | アルドステロンは、本来レニンの指令で出る——レニン → アンジオテンシンI → II → 副腎皮質球状層。 |
| コルチゾールは、いつ測るかで意味が変わる | コルチゾールは朝方に最も高く、深夜に最も低いという日内変動を持つ。 |
| ステロイドをやめるとき — 眠っている軸は、すぐには起きない | 外からステロイドを入れると、負のフィードバックで視床下部→下垂体→副腎の軸が止まる。 |
このノートは医学生が授業の内容を自分の言葉でまとめたもので、診療の判断に使うものではありません。誤りに気づいたらお知らせください。

