
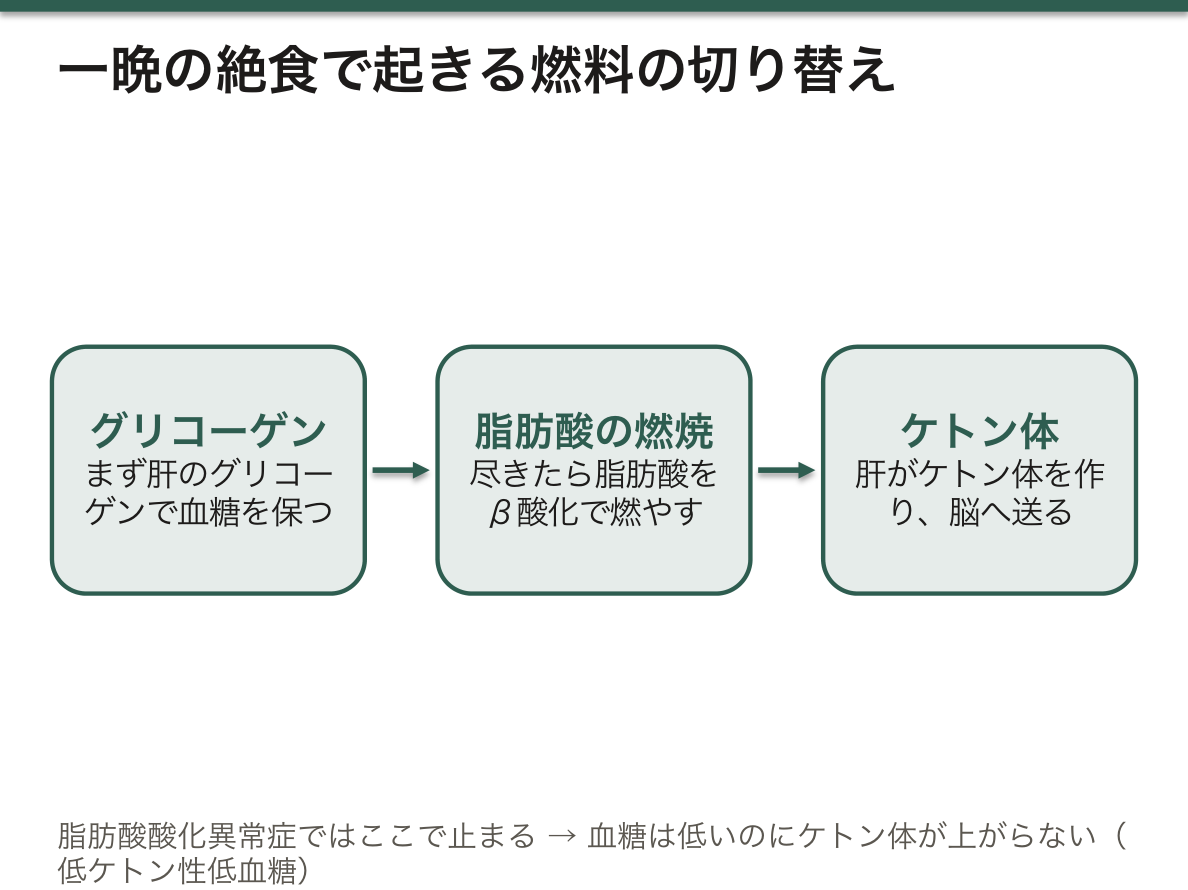
健常なら一晩の絶食は何でもない。グリコーゲンが尽きたら脂肪酸を燃やし、肝はケトン体を作って脳に送るからである。この切り替えのどこかが壊れていると、ただの絶食が命に関わる。
典型的な発症の形は決まっている——感冒や胃腸炎で食べられなくなった乳幼児が、意識障害とけいれんで運ばれてくる。血糖は低いのに、ケトン体が上がっていない。この組み合わせが決定的な手がかりになる。
- カルニチンシャトル — 長い脂肪酸は、自分では入れない
- 低ケトン性低血糖 — ケトン体が「無いこと」が診断になる
- 鎖の長さで、別の酵素が担当している — 脂肪酸酸化異常症の分け方
- 絶食を避けるという治療 — 何をどれだけ空けてよいか
- 母体の重症妊娠合併症が、胎児の代謝異常で起きることがある
- カルニチンは、どこから来ているのか
カルニチンシャトル — 長い脂肪酸は、自分では入れない
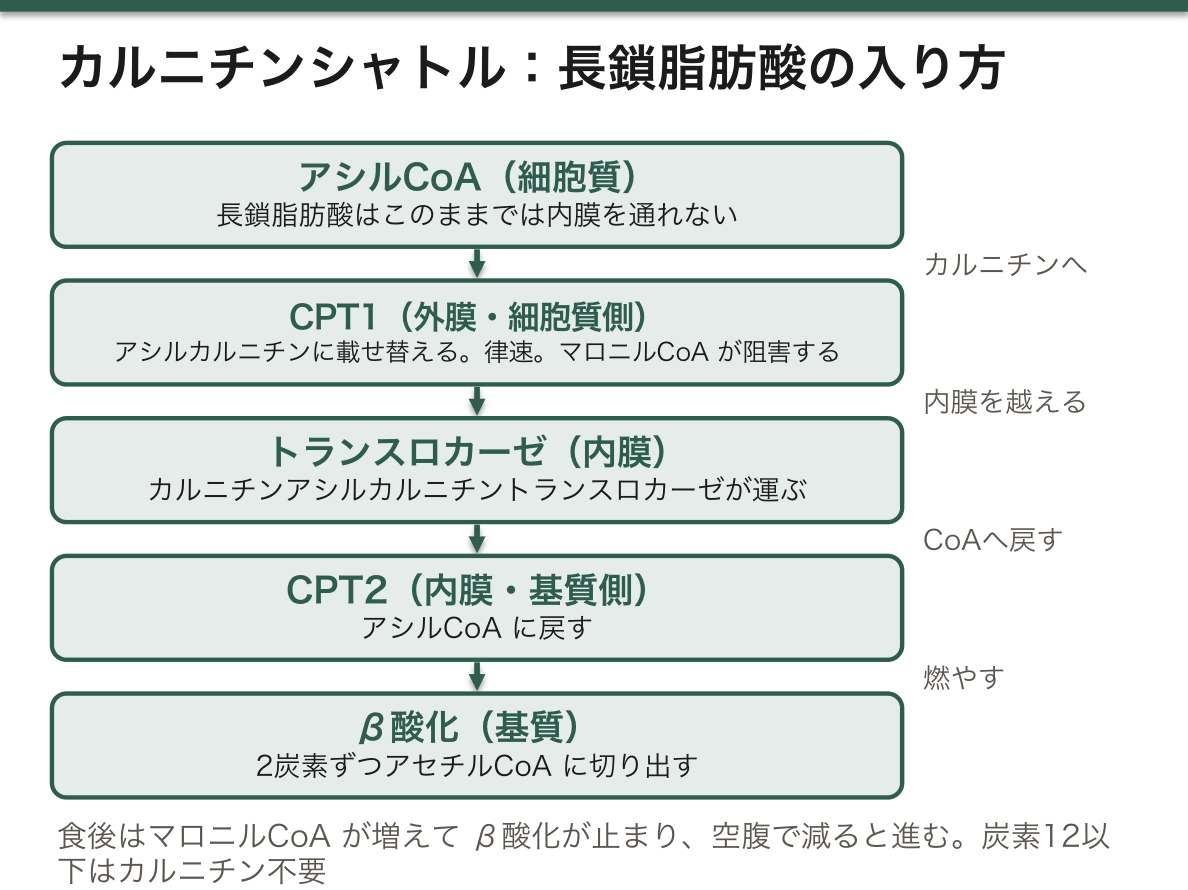
炭素数12以下の脂肪酸はミトコンドリア内膜を自由に通れるが、長鎖脂肪酸は通れない。カルニチンに載せ替える必要がある。
- カルニチンパルミトイルトランスフェラーゼ1(外膜、細胞質側):アシルCoA → アシルカルニチン
- カルニチンアシルカルニチントランスロカーゼ(内膜)で輸送
- カルニチンパルミトイルトランスフェラーゼ2(内膜、基質側):アシルカルニチン → アシルCoA
この経路の律速はカルニチンパルミトイルトランスフェラーゼ1で、マロニルCoAによって阻害される。
- 食後:脂肪酸合成が進む → マロニルCoAが増える → β酸化が止まる
- 空腹:マロニルCoAが減る → β酸化が進む
作ることと壊すことを、1つの中間体で切り替えている——糖代謝のフルクトース2,6ビスリン酸と同じ設計である。
カルニチン欠乏には一次性と二次性がある。
- 一次性——有機カチオントランスポータ2(腎と筋の取り込み輸送体)の欠損。心筋症と低ケトン性低血糖。カルニチンの補充で劇的に改善する数少ない代謝疾患である
- 二次性——はるかに多い。バルプロ酸(カルニチンを消費する)、ピボキシル基を持つ抗菌薬(ピバリン酸としてカルニチンを持ち去る)、透析、長期の中心静脈栄養
ピボキシル基を持つ抗菌薬による小児の低血糖・脳症は、日本で実際に注意喚起が出ている問題である。抗菌薬を数日飲んだ乳幼児が低血糖で搬送される——処方する側が知らなければ防げない。
カルニチンパルミトイルトランスフェラーゼ2欠損症は、発症年齢で3つの型に分かれる。成人型は運動や絶食を契機とした横紋筋融解症として現れ、低血糖を伴わないため見逃されやすい。繰り返すミオグロビン尿を見たら、代謝性ミオパチーを鑑別に入れる(運動の生化学の章)。
English version
Core
Fatty acids of twelve carbons or fewer cross the inner mitochondrial membrane freely; long-chain fatty acids cannot and must be transferred onto carnitine.
- Carnitine palmitoyltransferase 1 (outer membrane, cytosolic face): acyl-CoA → acylcarnitine.
- Carnitine–acylcarnitine translocase (inner membrane) transports it.
- Carnitine palmitoyltransferase 2 (inner membrane, matrix face): acylcarnitine → acyl-CoA.
The rate-limiting step is CPT-1, inhibited by malonyl-CoA.
- Fed: lipogenesis proceeds → malonyl-CoA rises → β-oxidation stops.
- Fasting: malonyl-CoA falls → β-oxidation proceeds.
Making and breaking are switched by a single intermediate — the same design as fructose 2,6-bisphosphate in carbohydrate metabolism.
Going further
Carnitine deficiency is primary or secondary.
- Primary — deficiency of OCTN2 (the uptake transporter of kidney and muscle). Cardiomyopathy and hypoketotic hypoglycaemia. One of the few metabolic diseases that improves dramatically with carnitine replacement.
- Secondary — far commoner. Valproate (which consumes carnitine), antibiotics carrying a pivoxil group (which carry carnitine away as pivalate), dialysis, long-term parenteral nutrition.
Hypoglycaemia and encephalopathy in children from pivoxil-containing antibiotics is a problem about which warnings have actually been issued in Japan. A toddler brought in with hypoglycaemia after a few days of an antibiotic — it cannot be prevented unless the prescriber knows.
CPT-2 deficiency divides into three forms by age of onset. The adult form presents as rhabdomyolysis triggered by exercise or fasting and is readily missed because there is no hypoglycaemia. On seeing recurrent myoglobinuria, put a metabolic myopathy into the differential.
低ケトン性低血糖 — ケトン体が「無いこと」が診断になる
低血糖を見たら、まずケトン体の有無で二分する。
| ケトン体が高い | ケトン体が低い(低ケトン性) | |
|---|---|---|
| 意味 | 脂肪酸酸化は動いている | 脂肪酸を燃やせていない |
| 代表 | ケトン性低血糖症・糖原病・副腎不全・成長ホルモン欠損 | 脂肪酸酸化異常症・高インスリン血症 |
- 中鎖アシルCoA脱水素酵素欠損症が最も頻度が高い。新生児マススクリーニングの対象
- 診断はタンデム質量分析によるアシルカルニチン分析(血中)と尿有機酸分析
- 治療の原則は絶食させないこと。発症時はブドウ糖の点滴
高インスリン血症も低ケトン性低血糖を起こす点が鑑別の鍵になる。インスリンは脂肪分解とケトン体産生を抑えるので、脂肪酸を燃やす能力はあるのに使わせてもらえない。だから低血糖時の血中インスリンと遊離脂肪酸を同時に測る。
| インスリン | 遊離脂肪酸 | ケトン体 | |
|---|---|---|---|
| 脂肪酸酸化異常症 | 低い | 高い | 低い |
| 高インスリン血症 | 高い | 低い | 低い |
「低血糖なのにインスリンが測定感度以上ある」こと自体が異常である。正常なら血糖50 mg/dL 未満でインスリンは抑制されきっている。
中鎖アシルCoA脱水素酵素欠損症は、かつて乳幼児突然死症候群と診断されていた一群を含んでいた。マススクリーニングの導入で、発症前に見つけて絶食を避けるだけで防げるようになった——スクリーニングの価値がもっとも明快に出た例である。
ジカルボン酸尿も所見として押さえておく。β酸化が詰まると、脂肪酸がミクロソームのω酸化へ迂回し、両端がカルボキシル基になった二塩基酸が尿へ出る。尿有機酸分析でアジピン酸・スベリン酸・セバシン酸が並ぶのはこの機序である。
English version
Core
Seeing hypoglycaemia, divide it first by the presence or absence of ketones.
| Ketones high | Ketones low (hypoketotic) | |
|---|---|---|
| Meaning | Fatty acid oxidation is working | Fatty acids cannot be burnt |
| Examples | Ketotic hypoglycaemia, glycogenoses, adrenal insufficiency, growth hormone deficiency | Fatty acid oxidation disorders, hyperinsulinism |
- MCAD deficiency is the commonest. Included in newborn screening.
- Diagnosis by acylcarnitine profile on tandem mass spectrometry (blood) and urinary organic acids.
- The principle of treatment is not to let the child fast. At presentation, intravenous glucose.
Going further
That hyperinsulinism also causes hypoketotic hypoglycaemia is the key to the differential. Insulin suppresses lipolysis and ketogenesis, so the capacity to burn fatty acids is there but is not being allowed to work. So measure the insulin and the free fatty acids at the same time as the low glucose.
| Insulin | Free fatty acids | Ketones | |
|---|---|---|---|
| Fatty acid oxidation disorder | Low | High | Low |
| Hyperinsulinism | High | Low | Low |
That the insulin is detectable at all during hypoglycaemia is itself abnormal — normally it is fully suppressed below a glucose of 50 mg/dL.
MCAD deficiency included a group once diagnosed as sudden infant death syndrome. With the introduction of screening it can now be found before it presents and prevented simply by avoiding fasting — the clearest example of the value of screening.
Fix dicarboxylic aciduria as a finding too. With β-oxidation blocked, fatty acids are diverted to microsomal ω-oxidation and diacids carboxylated at both ends appear in the urine. Adipic, suberic and sebacic acids lined up on urinary organic acid analysis is this mechanism.
鎖の長さで、別の酵素が担当している — 脂肪酸酸化異常症の分け方
β酸化の脱水素反応は、鎖の長さごとに別の酵素が担当する。
| 欠損 | 鎖長 | 特徴 |
|---|---|---|
| VLCAD 欠損症 | 極長鎖 | 新生児期の心筋症・不整脈/小児期以降の横紋筋融解症 |
| MCAD 欠損症 | 中鎖 | 最も多い。感染や絶食を契機に低ケトン性低血糖・脳症。乳幼児突然死と紛らわしい |
| SCAD 欠損症 | 短鎖 | 症状が乏しいことが多い |
| LCHAD/三頭酵素欠損症 | 長鎖 | 網膜症・末梢神経障害。母体の HELLP 症候群・妊娠性急性脂肪肝と関連する |
診断——血中アシルカルニチン分析で、詰まった鎖長のアシルカルニチンが特異的に上がる。
「詰まった手前が溜まる」という原則が、診断法そのものになっている。どの鎖長のアシルカルニチンが増えるかで、欠損している酵素が言い当てられる(新生児マススクリーニングの章)——「タンデムマス法が、この分野を一変させた」。
MCAD 欠損症は、治療できるのに突然死しうる病気になる(乳幼児突然死の章)——「発作の前は完全に健康なので、スクリーニングでしか拾えない」。
中鎖脂肪酸はカルニチンを介さずミトコンドリアへ入る(この章のカルニチンシャトルの項)——「だから長鎖の障害では中鎖脂肪酸を使えるが、MCAD 欠損症では使えない」。
母体の妊娠性急性脂肪肝が、胎児の LCHAD 欠損と関連することは、実務で問われる(産科の異常の章)——「母体の重症疾患が、生まれてくる子の診断につながる」。
横紋筋融解症を繰り返す成人でも、鑑別に入れる(代謝性ミオパチーの章)——「長時間の運動・寒冷・絶食が引き金になる」。
English version
Core
The dehydrogenation of β-oxidation is carried out by a different enzyme for each chain length.
| Deficiency | Chain | Features |
|---|---|---|
| VLCAD | Very long | Cardiomyopathy and arrhythmia in the newborn; rhabdomyolysis in later childhood |
| MCAD | Medium | The commonest. Hypoketotic hypoglycaemia and encephalopathy triggered by infection or fasting. Confusable with sudden infant death |
| SCAD | Short | Often with few symptoms |
| LCHAD / trifunctional protein | Long | Retinopathy, peripheral neuropathy. Associated with maternal HELLP syndrome and acute fatty liver of pregnancy |
Diagnosis — the acylcarnitine of the blocked chain length rises specifically on the blood acylcarnitine profile.
Going further
The principle that what lies behind the block accumulates is itself the diagnostic method. Which chain-length acylcarnitine rises names the deficient enzyme — tandem mass spectrometry transformed this field.
MCAD deficiency is a disease that can kill suddenly although it is treatable — the child is entirely well before the attack, so it can only be found by screening.
Medium-chain fatty acids enter the mitochondrion without carnitine — so in a long-chain defect medium-chain fat can be used, and in MCAD deficiency it cannot.
That maternal acute fatty liver of pregnancy is associated with fetal LCHAD deficiency is asked in practice — a severe maternal illness leading to the diagnosis of the child who is born.
Include it in the differential in an adult with recurrent rhabdomyolysis — prolonged exercise, cold and fasting are the triggers.
絶食を避けるという治療 — 何をどれだけ空けてよいか
治療の中心は、脂肪酸酸化に頼らせないことになる。
| やること | 内容 |
|---|---|
| ①絶食時間の上限を決める | 年齢で変える(乳児は 4〜6 時間、幼児は 8〜10 時間、年長児以降は 10〜12 時間が目安) |
| ②高炭水化物・低脂肪食 | 夜間は非加熱コーンスターチを使うことがある |
| ③長鎖の障害には中鎖脂肪酸(MCT) | カルニチンを介さず入れるので、詰まりを迂回できる |
| ④体調が悪いときの計画(sick day rules) | 食べられなければ受診し、ブドウ糖の点滴を受ける |
L-カルニチンの補充は、二次性欠乏がある場合に行う。
MCAD 欠損症では MCT を使わない——詰まっているのが中鎖そのものになるため。
「食べないこと自体が、発作の引き金になる」という点が、他の多くの病気と違う。だから治療の大半が、生活の設計になる(発症の引き金の項)——「薬ではなく、時間の管理が処方になる」。
手術や検査の絶食が、そのまま危険になる(術前評価の章)——「どの科にかかっても伝わるよう、緊急時の対応カードを持たせる」。
予防接種と発熱も、注意すべき場面になる(小児の急性疾患の章)——「接種を避けるのではなく、その後の哺乳と水分を確認する」。
MCT の使い分けは、この分野の理解を試す典型的な問いになる(この章の鎖長別の項)——「詰まりの手前を迂回できるか、を毎回考える」。
成人期に診断される例では、運動の指導が加わる(運動処方の章)——「運動前に糖を摂り、長時間の持久運動を避ける」。
English version
Core
The centre of treatment is not to make the patient depend on fatty acid oxidation.
| What is done | |
|---|---|
| ① Set a limit on the fasting interval | By age (as a guide, 4–6 hours in infants, 8–10 in toddlers, 10–12 from later childhood) |
| ② High-carbohydrate, low-fat diet | Uncooked cornstarch may be used overnight |
| ③ Medium-chain triglyceride (MCT) for the long-chain defects | It enters without carnitine, bypassing the block |
| ④ A plan for when unwell (sick day rules) | If unable to eat, attend and receive intravenous glucose |
L-carnitine is replaced where there is a secondary deficiency. MCT is not used in MCAD deficiency — the block is in the medium chains themselves.
Going further
That not eating is itself the trigger sets this apart from most other diseases. So most of the treatment is the design of a way of life — the prescription is the management of time, not a drug.
The fasting required for surgery or investigation is itself the danger — give the patient an emergency card so that it is conveyed in whatever department they attend.
Immunisation and fever are also situations to watch — not avoiding the immunisation, but checking the feeding and fluid afterwards.
The choice of MCT is the classic question testing understanding of this field — ask every time whether the block can be bypassed on its upstream side.
Where the diagnosis is made in adult life, advice about exercise is added — take sugar before exercise and avoid prolonged endurance work.
母体の重症妊娠合併症が、胎児の代謝異常で起きることがある
急性妊娠脂肪肝と HELLP 症候群は、母体の側の病気として扱われるが、胎児が脂肪酸酸化異常症をもっている場合に発症率が跳ね上がることが知られている。
特に LCHAD 欠損症(長鎖 3-ヒドロキシアシル CoA 脱水素酵素)で強い関連がある。
- 胎児と胎盤が、代謝しきれない長鎖の中間体を作る
- それが母体の循環へ移り、母の肝を傷害すると考えられている
- 母は保因者(ヘテロ)で、自分自身は無症状のことが多い
つまり、母を診ているようで、実は胎児の遺伝性疾患を見ているという構図になる。
実務上の含意が2つある。
- 急性妊娠脂肪肝や重症 HELLP を経験した母から生まれた児は、脂肪酸酸化異常症を積極的に調べる。新生児期は無症状でも、感染や絶食を機に致死的な発作を起こしうる
- 次の妊娠で再発しうるので、遺伝カウンセリングの対象になる(常染色体潜性なので、次子も 1/4 の確率で罹患する)
急性妊娠脂肪肝そのものの押さえどころ。
| 時期 | 妊娠後期(多くは 30 週以降) | 初産・多胎・男児で多い |
| 症状 | 悪心・嘔吐・腹痛・口渇・多尿 | つわりや胃腸炎と間違えられる |
| 検査 | 低血糖・PT 延長・アンモニア上昇・白血球増多・尿酸高値 | 低血糖は HELLP との鑑別に有用 |
| 治療 | 速やかな妊娠の終了 | 肝の支持療法だけでは進行する。分娩が治療である |
妊娠は、母体を強い異化状態に置く。胎児と胎盤がブドウ糖を大量に消費するため、母は脂肪酸とケトン体に頼る割合が増える。だから脂質代謝の弱点が、妊娠後期に表面化する。妊婦が「食べられない」状態を軽く見てはいけない理由でもある。
妊娠後期の嘔吐と全身倦怠では、血糖・肝機能・凝固を測る。「つわりが長引いている」で済ませない。
English version
Core
Acute fatty liver of pregnancy and the HELLP syndrome are treated as maternal diseases, but their incidence is known to leap where the fetus has a fatty acid oxidation disorder, with a strong association for LCHAD deficiency.
- The fetus and placenta make long-chain intermediates they cannot metabolise.
- These are thought to pass into the maternal circulation and injure her liver.
- The mother is a heterozygous carrier and usually has no symptoms herself.
That is, one appears to be treating the mother while in fact looking at an inherited disease of the fetus.
Going further
Two practical implications.
- Investigate actively for a fatty acid oxidation disorder in a child born to a mother who has had acute fatty liver of pregnancy or severe HELLP. Asymptomatic in the newborn period, it can nonetheless cause a fatal attack with infection or fasting.
- It can recur in the next pregnancy, so it is a matter for genetic counselling (being autosomal recessive, the next child has a 1 in 4 risk).
The points about acute fatty liver of pregnancy itself.
| Note | ||
|---|---|---|
| Timing | Late pregnancy (usually after 30 weeks) | Commoner in first pregnancies, multiple pregnancy and male fetuses |
| Symptoms | Nausea, vomiting, abdominal pain, thirst, polyuria | Mistaken for hyperemesis or gastroenteritis |
| Tests | Hypoglycaemia, prolonged PT, raised ammonia, leucocytosis, high urate | The hypoglycaemia is useful in distinguishing it from HELLP |
| Treatment | Prompt delivery | Supportive care of the liver alone does not stop it. Delivery is the treatment |
Pregnancy places the mother in a strongly catabolic state. The fetus and placenta consume a great deal of glucose, so the mother depends more on fatty acids and ketones. A weakness in lipid metabolism therefore surfaces in late pregnancy — and this is why "she cannot eat" in a pregnant woman must not be taken lightly.
In the clinic
With vomiting and malaise in late pregnancy, measure the blood glucose, liver function and clotting. Do not settle for "the morning sickness is going on a long time".
カルニチンは、どこから来ているのか
カルニチンはビタミンではない——体内で作れる。ただし作る量は多くなく、供給の 4 分の 3 は食事からである。
- 材料はリジンとメチオニン——リジンがメチル化され、4 段階で作られる
- 補酵素にビタミン C・B6・ナイアシン・鉄が要る——壊血病の倦怠感の一部は、カルニチンが作れないためとも説明される
- 作る場所は肝・腎・脳。心筋と骨格筋は作れず、取り込むだけ
- 食事では肉と乳製品に多い。植物性食品にはほとんど無い
体内のカルニチンの 95% 以上は筋にある。取り込みは OCTN2 という輸送体が担い、腎では 98% が再吸収されている。
欠乏は「作れない」より「失う・奪われる」で起きることが多い。
| 原発性 | OCTN2 の異常 | 取り込めず、腎から漏れ続ける。心筋症・低ケトン性低血糖。補充がよく効く |
| 有機酸血症・脂肪酸酸化異常症 | 溜まった有機酸がカルニチンと結合して尿へ出ていく | 解毒の代償として消費される |
| 薬剤性 | バルプロ酸/ピボキシル基をもつ抗菌薬(小児のセフェム系シロップなど) | ピバリン酸がカルニチンを引き連れて排泄される。低血糖・けいれん・脳症の報告がある |
| 透析 | 小分子なので抜けてしまう | 筋力低下・心筋症・エリスロポエチン抵抗性の貧血に関わる |
| 低栄養・厳格な菜食・早産児 | 摂取と合成が足りない | 早産児は腎の再吸収も未熟 |
⚠️ 小児にピボキシル基含有抗菌薬を長く出さない。日本では低カルニチン血症による低血糖・けいれんの症例が報告され、注意喚起が出ている。数日で起こりうるので「短期だから安全」とは言えない。
測るときは分画で見る。遊離カルニチンとアシルカルニチンを分けて測り、アシル/遊離比が 0.4 を超えれば、何かが消費していると読む。総量だけでは欠乏が隠れる。
けいれんを起こした小児では、直前に飲んでいた抗菌薬の名前を確認する。ピボキシル基の有無が鍵になる。
English version
Core
Carnitine is not a vitamin — it can be made in the body. But not in large amounts, and three quarters of the supply comes from the diet.
- The materials are lysine and methionine — lysine is methylated and made in four steps.
- The cofactors are vitamin C, B6, niacin and iron — part of the fatigue of scurvy is explained as an inability to make carnitine.
- It is made in liver, kidney and brain. Heart and skeletal muscle cannot make it and only take it up.
- In the diet it is abundant in meat and dairy and almost absent from plant foods.
Over 95 per cent of the body’s carnitine is in muscle. Uptake is by the transporter OCTN2, and 98 per cent is reabsorbed in the kidney.
Going further
Deficiency arises more often from losing or being robbed of it than from failing to make it.
| Cause | Mechanism | Note |
|---|---|---|
| Primary | Abnormal OCTN2 | It cannot be taken up and leaks from the kidney. Cardiomyopathy, hypoketotic hypoglycaemia. Replacement works well |
| Organic acidaemias, fatty acid oxidation disorders | The accumulated organic acids conjugate with carnitine and leave in the urine | Consumed as the price of detoxification |
| Drug-induced | Valproate; antibiotics with a pivoxil group (paediatric cephalosporin syrups and others) | Pivalate takes carnitine with it. Hypoglycaemia, seizures and encephalopathy have been reported |
| Dialysis | A small molecule, it is removed | Involved in weakness, cardiomyopathy and erythropoietin-resistant anaemia |
| Malnutrition, strict veganism, prematurity | Intake and synthesis are both insufficient | The preterm kidney also reabsorbs immaturely |
⚠️ Do not prescribe pivoxil-containing antibiotics to children for long. Cases of hypoglycaemia and seizures from carnitine deficiency have been reported in Japan and warnings issued. It can happen within days, so "it is only short-term" is not safe.
Measure it as fractions. Free carnitine and acylcarnitine are measured separately, and an acyl/free ratio above 0.4 reads as something consuming it. The total alone hides a deficiency.
In the clinic
In a child who has had a seizure, check the name of the antibiotic taken just before. Whether it carries a pivoxil group is the key.
まとめ
| カルニチンシャトル — 長い脂肪酸は、自分では入れない | 炭素数12以下の脂肪酸はミトコンドリア内膜を自由に通れるが、長鎖脂肪酸は通れない。 |
|---|---|
| 低ケトン性低血糖 — ケトン体が「無いこと」が診断になる | 低血糖を見たら、まずケトン体の有無で二分する。 |
| 鎖の長さで、別の酵素が担当している — 脂肪酸酸化異常症の分け方 | β酸化の脱水素反応は、鎖の長さごとに別の酵素が担当する。 |
| 絶食を避けるという治療 — 何をどれだけ空けてよいか | 治療の中心は、脂肪酸酸化に頼らせないことになる。 |
| 母体の重症妊娠合併症が、胎児の代謝異常で起きることがある | 急性妊娠脂肪肝と HELLP 症候群は、母体の側の病気として扱われるが、胎児が脂肪酸酸化異常症をもっている場合に発症率が跳ね上がることが知られている。 |
| カルニチンは、どこから来ているのか | カルニチンはビタミンではない——体内で作れる。 |
このノートは医学生が授業の内容を自分の言葉でまとめたもので、診療の判断に使うものではありません。誤りに気づいたらお知らせください。

