
抗癌薬・免疫抑制薬・抗ウイルス薬の多くは、核酸の合成経路のどこかを塞ぐ薬である。作用点が経路上の一点に決まっているので、副作用も、耐性の生じ方も、経路から予測できる。
選択性は「分裂が速い細胞ほど強く効く」という一点に依存している。だから骨髄・消化管粘膜・毛根・生殖細胞が副作用の場所になる——これは避けられない代償である。
- 葉酸とチミジル酸を狙う — メトトレキサートと5-フルオロウラシル
- プリンを狙う薬と、鎖を止める薬
- ロイコボリン救済 — 効かせたい細胞だけを、後から助ける
- 同じ量で死ぬ人がいる — 代謝の個人差が、抗腫瘍薬で牙をむく
- メトトレキサートは、量が変われば別の薬になる
- 骨髄抑制は、細胞の寿命どおりの順序で現れる
葉酸とチミジル酸を狙う — メトトレキサートと5-フルオロウラシル
チミジル酸合成は、DNA合成の律速である。
デオキシウリジル酸 →(チミジル酸合成酵素、メチル基は5,10メチレンテトラヒドロ葉酸から)→ チミジル酸
| 薬 | 作用点 | 解毒・救済 |
|---|---|---|
| メトトレキサート | ジヒドロ葉酸還元酵素を阻害 | ホリナート(ロイコボリン)——還元済みの葉酸を与える |
| 5-フルオロウラシル | チミジル酸合成酵素を阻害 | — |
| ペメトレキセド | 複数の葉酸酵素 | 葉酸とビタミンB12の事前投与 |
- メトトレキサートの主な副作用——口内炎・骨髄抑制・肝障害・間質性肺炎。腎排泄なので腎機能低下で毒性が増す
- 非ステロイド性抗炎症薬との併用でメトトレキサートの排泄が落ちる
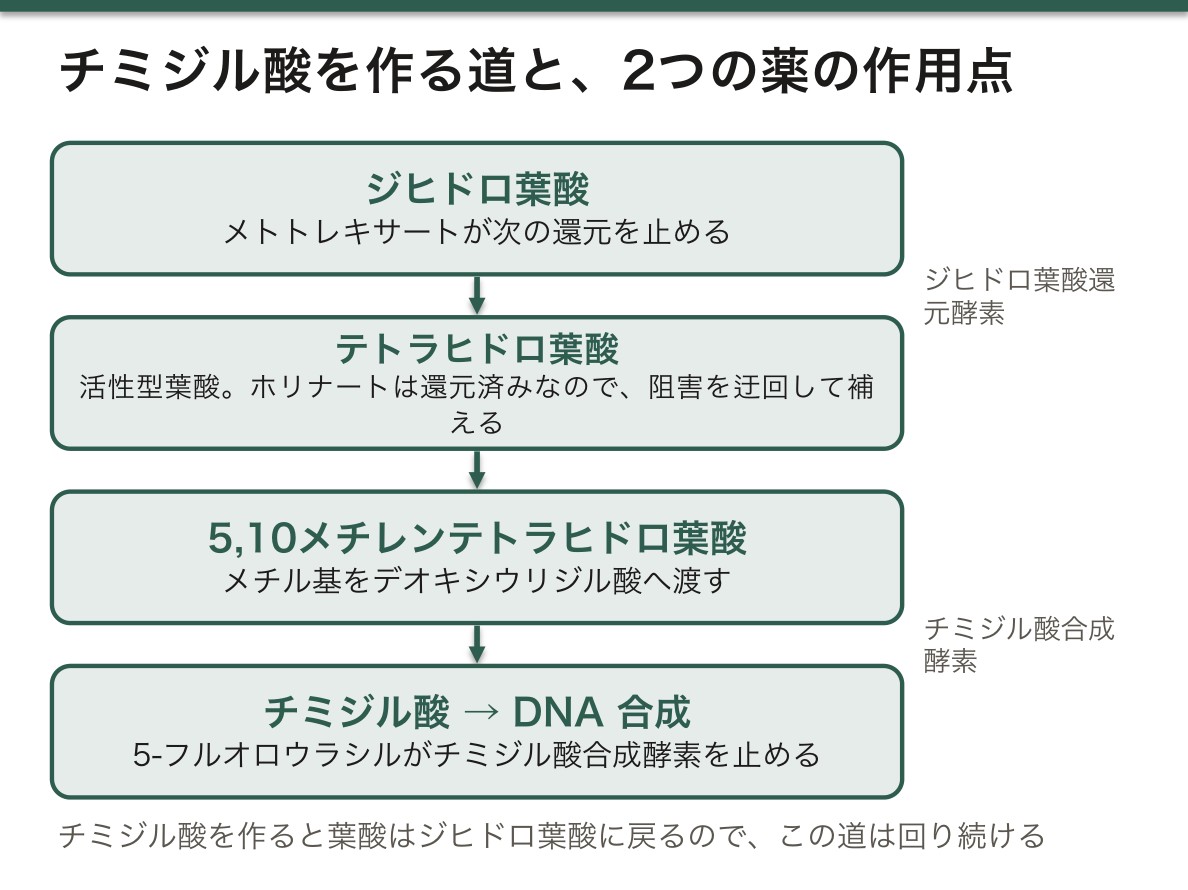
ロイコボリン救援の理屈を正確に言えるようにしておく。メトトレキサートはジヒドロ葉酸還元酵素を止めるので、テトラヒドロ葉酸が作れなくなる。ホリナートはすでに還元された形の葉酸なので、阻害された酵素を迂回して直接使える。大量療法の後、一定時間を置いてから投与するのは、その間に癌細胞へ十分な打撃を与えるためである。
同じホリナートが、5-フルオロウラシルでは逆に効果を強める——ここが紛らわしい。5-フルオロウラシルの活性代謝物はチミジル酸合成酵素と葉酸で三者複合体を作って酵素を止めるので、葉酸が多いほど複合体が安定し、阻害が強まる。同じ薬が、相手によって解毒剤にも増強剤にもなる。
ジヒドロピリミジン脱水素酵素欠損は臨床で命に関わる。5-フルオロウラシルを分解する酵素で、欠損があると重篤な骨髄抑制と粘膜障害を起こす。抗真菌薬フルシトシンは腸内細菌により5-フルオロウラシルに変換されるため、同じ危険がある。
メトトレキサートは「量で人格が変わる薬」である。関節リウマチでは週1回の少量、悪性腫瘍では大量投与。週1回の薬を毎日飲んでしまう誤りが、実際に死亡事故として繰り返し報告されている——処方も服薬指導も、この一点を外さない。
English version
Core
The synthesis of thymidylate is the rate-limiting step of DNA synthesis.
Deoxyuridylate → (thymidylate synthase, the methyl group from 5,10-methylene-tetrahydrofolate) → thymidylate
| Drug | Point of action | Antidote / rescue |
|---|---|---|
| Methotrexate | Inhibits dihydrofolate reductase | Folinate (leucovorin) — gives already-reduced folate |
| 5-Fluorouracil | Inhibits thymidylate synthase | — |
| Pemetrexed | Several folate enzymes | Folate and vitamin B12 given beforehand |
The chief adverse effects of methotrexate — stomatitis, marrow suppression, liver injury, interstitial pneumonitis. It is renally excreted, so toxicity increases with reduced renal function.
Given with an NSAID, the excretion of methotrexate falls.
Going further
Be able to state the reasoning of leucovorin rescue accurately. Methotrexate stops dihydrofolate reductase, so tetrahydrofolate can no longer be made. Folinate is folate already in the reduced form, so it bypasses the inhibited enzyme and can be used directly. It is given a set time after high-dose therapy so that in the interval the cancer cells take sufficient damage.
The same folinate, with 5-fluorouracil, strengthens the effect instead — this is the confusing part. The active metabolite of 5-FU forms a ternary complex with thymidylate synthase and folate to stop the enzyme, so the more folate, the more stable the complex and the stronger the inhibition. The same drug being an antidote or an enhancer according to its partner.
Dihydropyrimidine dehydrogenase deficiency is a matter of life in practice. It is the enzyme that degrades 5-FU, and a deficiency gives severe marrow suppression and mucosal injury. The antifungal flucytosine is converted to 5-FU by gut bacteria, so it carries the same danger.
Methotrexate is a drug whose character changes with the dose. A small dose once a week in rheumatoid arthritis, large doses in malignancy. The error of taking a once-weekly drug every day has been reported repeatedly as a fatal accident — do not miss this point either in prescribing or in counselling.
プリンを狙う薬と、鎖を止める薬
| 薬 | 作用 | 要点 |
|---|---|---|
| 6-メルカプトプリン/アザチオプリン | プリン合成を阻害 | キサンチンオキシダーゼで分解される → アロプリノール併用で毒性が跳ね上がる |
| ミコフェノール酸 | イノシン一リン酸脱水素酵素を阻害 | リンパ球は救済経路が乏しくグアニンを新生経路に頼るため選択性が出る |
| シタラビン | DNAポリメラーゼを阻害 | 急性骨髄性白血病 |
| アシクロビル | DNA鎖を止める | ウイルスのチミジンキナーゼでのみ活性化 → 感染細胞だけで効く |
| ジドブジンなど | 逆転写酵素を止める | 3位の水酸基が無く、次を繋げない |
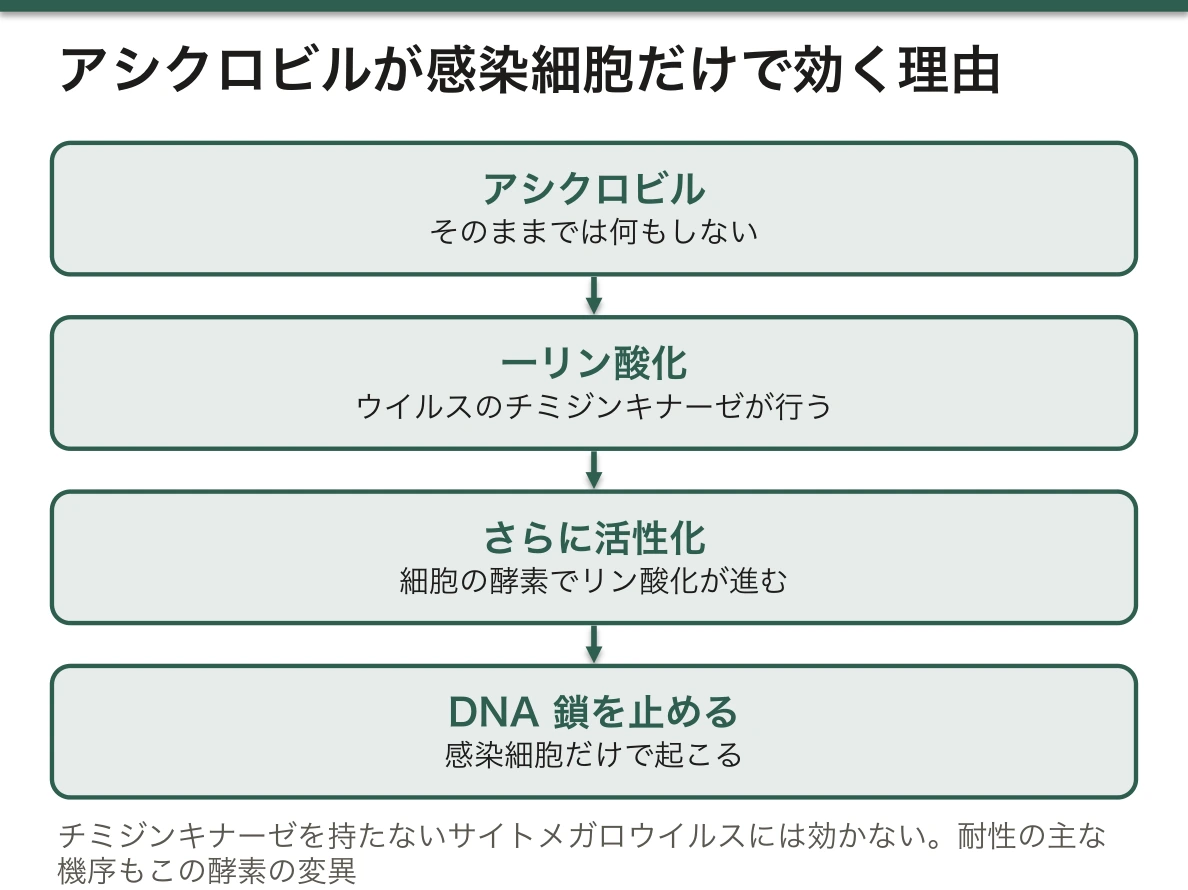
アシクロビルの選択性は、抗ウイルス薬の設計思想そのものである。この薬はそのままでは何もしない。単純ヘルペスウイルスや水痘帯状疱疹ウイルスのチミジンキナーゼによって一リン酸化されて初めて活性化の道に乗る。感染していない細胞では活性化されないので、毒性が極めて低い。
この事実から2つの帰結が出る。
- チミジンキナーゼを持たないウイルスには効かない——サイトメガロウイルスにアシクロビルが効かないのはこのため。ガンシクロビルは別の酵素で活性化される
- 耐性の主な機序はチミジンキナーゼの変異である。免疫不全患者で長期使用すると出現する。その場合は活性化を必要としないホスカルネットへ切り替える
チオプリン薬(6-メルカプトプリン・アザチオプリン)は、薬理遺伝学の代表例である。チオプリンS-メチル基転移酵素やNUDT15の多型があると分解が遅れ、通常量で重篤な骨髄抑制と全脱毛を起こす。NUDT15の変異は日本人・東アジア人に多いため、炎症性腸疾患などで投与前に遺伝子型を調べることが保険適用になっている。
アロプリノールとの相互作用も必ず押さえる。6-メルカプトプリンはキサンチンオキシダーゼで不活化されるので、アロプリノールを併用すると血中濃度が数倍に上がる。併用するなら投与量を4分の1程度へ減らす——痛風と炎症性腸疾患を併せ持つ患者で、現実に起こりうる組み合わせである。
English version
Core
| Drug | Action | Key point |
|---|---|---|
| 6-Mercaptopurine / azathioprine | Inhibit purine synthesis | Degraded by xanthine oxidase → toxicity leaps with concurrent allopurinol |
| Mycophenolic acid | Inhibits inosine monophosphate dehydrogenase | Lymphocytes have little salvage and depend on de novo synthesis for guanine, which gives the selectivity |
| Cytarabine | Inhibits DNA polymerase | Acute myeloid leukaemia |
| Aciclovir | Terminates the DNA chain | Activated only by the viral thymidine kinase → it works only in infected cells |
| Zidovudine and others | Stop reverse transcriptase | Lacking the 3′ hydroxyl, nothing can be joined on |
Going further
The selectivity of aciclovir is the design philosophy of antiviral drugs itself. As it is, the drug does nothing. Only when monophosphorylated by the thymidine kinase of herpes simplex or varicella-zoster virus does it enter the path to activation. In an uninfected cell it is not activated, so the toxicity is extremely low.
Two consequences follow.
- It does not work on viruses without a thymidine kinase — hence aciclovir does not work on cytomegalovirus. Ganciclovir is activated by another enzyme.
- The chief mechanism of resistance is mutation of the thymidine kinase. It emerges with long use in the immunocompromised. In that case change to foscarnet, which needs no activation.
The thiopurines (6-mercaptopurine, azathioprine) are the representative example of pharmacogenetics. With polymorphisms of thiopurine S-methyltransferase or NUDT15, degradation is delayed and an ordinary dose causes severe marrow suppression and total alopecia. The NUDT15 variant is common in Japanese and East Asian people, so genotyping before administration is covered by insurance in inflammatory bowel disease and elsewhere.
Always hold the interaction with allopurinol. 6-Mercaptopurine is inactivated by xanthine oxidase, so giving allopurinol with it raises the blood level several-fold. If they must be combined, reduce the dose to about a quarter — a combination that can really arise in a patient who has both gout and inflammatory bowel disease.
ロイコボリン救済 — 効かせたい細胞だけを、後から助ける
メトトレキサートはジヒドロ葉酸還元酵素を阻害し、活性型葉酸(テトラヒドロ葉酸)を枯渇させる。
ロイコボリン(ホリナート)は、還元酵素を通らずに使える活性型葉酸になる——だから阻害を迂回して補充できる。
| 使い方 | 目的 |
|---|---|
| 大量メトトレキサート療法の後の救済 | 正常細胞を助け、腫瘍細胞との差をつける |
| メトトレキサート中毒の解毒 | 腎障害で排泄が遅れたとき |
| 5-フルオロウラシルとの併用 | 逆に効果を強める(三者複合体を安定化する) |
ビタミンB12 欠乏を隠しうるので、葉酸単独の補充とは区別する。
同じ薬が、片方では「効果を打ち消し」、もう片方では「効果を強める」ことが要点になる。メトトレキサートの標的は葉酸そのものなので補うと打ち消し、5-フルオロウラシルの標的はチミジル酸合成酵素なので、葉酸が多いほど酵素との結合が安定する(この章の葉酸とチミジル酸の項)——「作用点が違えば、同じ補充が逆の意味になる」。
救済が成り立つのは、細胞ごとに薬の残り方が違うからになる。正常細胞のほうが薬を早く排出するので、後から葉酸を入れると先に回復する(抗腫瘍薬の章)——「毒性の差を、時間差で作り出している」。
だから血中濃度と腎機能を測りながら、救済の量と期間を決める(血中濃度を測る章)——「尿をアルカリ化して排泄を促すのも、同じ目的になる」。
相互作用が致命的になりうる。非ステロイド性抗炎症薬・プロトンポンプ阻害薬・スルホンアミド系がメトトレキサートの排泄を遅らせる(相互作用の章)——「関節リウマチの少量投与でも、汎血球減少が起こる」。
関節リウマチでは、副作用を減らすために葉酸を併用する(抗リウマチ薬の章)——「効果を消さない量とタイミングを選んで入れている」。
English version
Core
Methotrexate inhibits dihydrofolate reductase and exhausts the active folate (tetrahydrofolate).
Leucovorin (folinate) is active folate usable without passing through the reductase — so it can be supplied bypassing the inhibition.
| Use | Purpose |
|---|---|
| Rescue after high-dose methotrexate | Help the normal cells and create a difference from the tumour cells |
| Antidote in methotrexate toxicity | When excretion is delayed by renal impairment |
| Combined with 5-fluorouracil | Strengthens the effect instead (stabilising the ternary complex) |
It can mask vitamin B12 deficiency, so distinguish it from folate supplementation alone.
Going further
- The key point is that the same drug on one side cancels the effect and on the other strengthens it. The target of methotrexate is folate itself, so supplying it cancels the effect; the target of 5-fluorouracil is thymidylate synthase, so the more folate the more stable the binding to the enzyme (the section on folate and thymidylate in this chapter) — with a different point of action, the same supplementation means the opposite.
- Rescue works because the drug remains differently in different cells. Normal cells clear the drug faster, so giving folate afterwards lets them recover first (the chapter on antitumour drugs) — the difference in toxicity created out of a difference in time.
- Hence the amount and duration of rescue are set while measuring the blood level and renal function (the chapter on measuring blood levels) — alkalinising the urine to promote excretion serves the same purpose.
- Interactions can be fatal. NSAIDs, proton pump inhibitors and sulphonamides delay the excretion of methotrexate (the chapter on interactions) — pancytopenia occurs even on the low doses of rheumatoid arthritis.
- In rheumatoid arthritis folate is given alongside to reduce the adverse effects (the chapter on antirheumatic drugs) — put in at an amount and timing chosen not to abolish the effect.
同じ量で死ぬ人がいる — 代謝の個人差が、抗腫瘍薬で牙をむく
抗腫瘍薬は治療域が狭い。だから代謝の個人差が、そのまま重篤な副作用になる。
| 薬 | 関わる分子 | 異常があると |
|---|---|---|
| 5-フルオロウラシル・カペシタビン | DPD(DPYD) | 分解できず、重度の骨髄抑制・粘膜炎・下痢 |
| アザチオプリン・6-メルカプトプリン | NUDT15・TPMT | 高度の骨髄抑制・脱毛 |
| イリノテカン | UGT1A1(*6/*28) | 好中球減少・下痢 |
| メトトレキサート | MTHFR・腎機能 | 粘膜炎・骨髄抑制 |
日本では NUDT15 と UGT1A1 の検査が、投与前に行われている。
抗ウイルス薬のソリブジンは、DPD を阻害して 5-FU の毒性を激増させた(1993年の薬害)。
「効くために増やす細胞を狙う薬は、正常の増える細胞も同じだけ狙う」という前提が、この項の背景になる。だから毒性は骨髄・消化管粘膜・毛根に出る(抗腫瘍薬の章)——「副作用の場所が、薬の作用機序を裏づけている」。
ソリブジン事件は、機序が分かっていれば防げた薬害になる(薬害の歴史の章)——「分解する酵素を止める薬を、分解される薬と一緒に出した」。
投与前に測る検査が普及した意味は、量の調整ができることにある(薬物代謝の個人差の項)——「投与しないのではなく、その人に合う量から始める」。
手足症候群や粘膜炎は、生活の質を大きく落とす(がんの痛みの章)——「予防的な口腔ケアと保湿が、治療の継続率を上げる」。
薬の副作用を「体質」で片づけないことが、この分野の出発点になっている——「測れる分子として説明できるものが、少しずつ増えている」。
English version
Core
Antitumour drugs have a narrow therapeutic window. So individual variation in metabolism becomes, directly, a severe adverse effect.
| Drug | Molecule involved | With an abnormality |
|---|---|---|
| 5-Fluorouracil, capecitabine | DPD (DPYD) | It cannot be degraded: severe marrow suppression, mucositis, diarrhoea |
| Azathioprine, 6-mercaptopurine | NUDT15, TPMT | Severe marrow suppression, alopecia |
| Irinotecan | UGT1A1 (*6/*28) | Neutropenia, diarrhoea |
| Methotrexate | MTHFR, renal function | Mucositis, marrow suppression |
In Japan, testing for NUDT15 and UGT1A1 is done before administration.
The antiviral sorivudine inhibited DPD and hugely increased the toxicity of 5-FU (the drug disaster of 1993).
Going further
- The background of this section is the premise that a drug aimed at cells that multiply hits the normal multiplying cells just as hard. Hence the toxicity appears in marrow, gut mucosa and hair follicles (the chapter on antitumour drugs) — the sites of the adverse effects confirming the mechanism of the drug.
- The sorivudine affair was a drug disaster that could have been prevented had the mechanism been understood (the chapter on the history of drug disasters) — a drug that stops the degrading enzyme given together with the drug it degrades.
- The meaning of the spread of testing before administration is that the dose can be adjusted (the section on individual variation in drug metabolism) — not withholding the drug, but starting from the dose that suits that person.
- Hand–foot syndrome and mucositis greatly reduce quality of life (the chapter on cancer pain) — prophylactic oral care and moisturising raise the rate at which treatment is continued.
- Not disposing of an adverse effect as "constitution" is the starting point of this field — the number of things explicable as measurable molecules is growing little by little.
メトトレキサートは、量が変われば別の薬になる
同じ薬でありながら、抗癌剤としての使い方と、抗リウマチ薬としての使い方で、効いている機序が違うと考えられている。
| 高用量(抗腫瘍) | DHFR を止め、DNA の材料を枯らす | 分裂の速い細胞が死ぬ。ロイコボリン救済が要る |
| 低用量・週 1 回(抗リウマチ) | 別の酵素を抑えてアデノシンを放出させる | アデノシンが受容体を介して抗炎症に働く。葉酸を併用しても効果は保たれる |
だから抗リウマチ用途では、葉酸を一緒に飲ませる。口内炎・肝障害・血球減少といった副作用は葉酸拮抗によるものなので、葉酸を補えば副作用だけを減らせる。抗腫瘍の場面とは考え方が逆になる。
⚠️ この薬は、投与間隔の誤りで人が亡くなっている。
関節リウマチでは週 1 回(あるいは週 1 日に分割)投与する。これを毎日投与すると、数日で骨髄抑制と粘膜障害を起こし、致死的になる。日本でも繰り返し報告され、厚生労働省と医療機能評価機構から注意喚起が出ている。
- 処方箋に「週1回」と明記し、曜日を決める
- 入院時の持参薬をそのまま毎日の定期薬に転記しない——事故はここで起きる
- 患者にも「毎日ではない」と伝える。飲み忘れて翌日にまとめて飲む、も危険
腎機能が落ちると、一気に危なくなる。主に腎から排泄されるので、脱水・NSAID・ST 合剤・プロトンポンプ阻害薬との併用で血中濃度が上がる。「食欲が落ちて水が飲めていない高齢者」が、最も危ない状況である。
中毒時の解毒は2段構えになる。ロイコボリン(活性型葉酸)で下流を助け、重症例ではグルカルピダーゼ(メトトレキサートを分解する酵素)を使う。尿のアルカリ化と大量補液で結晶による腎障害も防ぐ。
副作用として間質性肺炎があり、用量に依存せず、投与開始から数か月以内に起こりうる。咳と息切れを訴えたら、感染と鑑別する。
関節リウマチの患者を診たら、メトトレキサートを何曜日に飲んでいるかを必ず確認する。答えられないときは処方を確かめる。
English version
Core
Though it is the same drug, the mechanism at work is thought to differ between its use as an antitumour drug and as an antirheumatic drug.
| High dose (antitumour) | Stops DHFR and exhausts the material of DNA | Rapidly dividing cells die. Leucovorin rescue is needed |
| Low dose, once weekly (antirheumatic) | Suppresses other enzymes and causes the release of adenosine | Adenosine acts anti-inflammatorily through its receptors. The effect is preserved even with folate given alongside |
So in the antirheumatic use, folate is taken with it. The adverse effects — stomatitis, liver injury, cytopenias — come from folate antagonism, so supplying folate reduces the adverse effects alone. The reasoning is the reverse of the antitumour setting.
Going further
⚠️ People have died from errors in the interval of administration.
In rheumatoid arthritis it is given once a week (or divided within one day of the week). Given daily, it causes marrow suppression and mucosal injury within days and can be fatal. It has been reported repeatedly in Japan, and warnings have been issued by the Ministry of Health, Labour and Welfare and the Japan Council for Quality Health Care.
- Write "once weekly" explicitly on the prescription and fix the day.
- Do not transcribe a patient’s own medicines on admission straight into the daily regular orders — this is where the accidents happen.
- Tell the patient too that it is not daily. Taking a double dose the next day after forgetting is also dangerous.
When renal function falls it becomes dangerous at a stroke. Being excreted chiefly by the kidney, the blood level rises with dehydration, NSAIDs, co-trimoxazole and proton pump inhibitors. "An older person whose appetite has fallen and who is not drinking" is the most dangerous situation.
The antidote in toxicity has two stages. Leucovorin (active folate) helps downstream, and in severe cases glucarpidase (an enzyme that degrades methotrexate) is used. Alkalinisation of the urine and large-volume fluid also prevent renal injury from crystals.
Interstitial pneumonitis is an adverse effect, independent of dose, and can occur within months of starting. If the patient complains of cough and breathlessness, distinguish it from infection.
In the clinic
Seeing a patient with rheumatoid arthritis, always confirm which day of the week they take methotrexate. If they cannot say, check the prescription.
骨髄抑制は、細胞の寿命どおりの順序で現れる
抗癌剤を投与しても、その日に血球は減らない。既に血中にいる細胞は、寿命が尽きるまで働き続けるからである。だから減り始める時期は、細胞の寿命で決まる。
| 好中球 | 血中の寿命が半日〜1 日 | 最も早く減る。最低値は 7〜14 日目。回復は 3〜4 週 |
| 血小板 | 寿命 7〜10 日 | 好中球よりやや遅れて下がる |
| 赤血球 | 寿命 120 日 | 急には減らない。貧血は繰り返し投与で、ゆっくり進む |
だから「投与直後は元気だが、10 日目に発熱する」という経過になる。患者にはこの時期を具体的に伝えておく。
次の投与までの間隔(3〜4 週)は、好中球が戻る時間で決まっている。薬の半減期ではなく、正常組織が回復する時間が投与間隔を決めている。
⚠️ 発熱性好中球減少症は、緊急事態として扱う。
- 好中球 500/μL 未満(または 1000 未満で下降中)+発熱で定義する
- 感染巣も起炎菌も分からないうちに、広域抗菌薬を1時間以内に始める
- 炎症の徴候が出ない——好中球がいないので、膿も浸潤影もできにくい。発熱だけが唯一の徴候になりうる
「所見が乏しいこと」が、軽症であることを意味しない——この一点が最も重要である。
薬によって、抑制の出方が違う。
- ニトロソウレア・マイトマイシン——4〜6 週と遅れて最低値が来る。回復も遅く、累積する
- ブレオマイシン・ビンクリスチン——骨髄抑制が軽い(そのかわり肺線維症・神経障害が用量を制限する)
- G-CSF——好中球の回復を早める。予防投与は、発熱性好中球減少症の頻度が高いレジメンで行う
同じ理屈は他の副作用にも当てはまる。口内炎は 5〜7 日目(口腔粘膜の更新が数日)、脱毛は 2〜3 週目(毛母細胞の分裂の速さ)。「どの正常組織が、どれくらいの速さで入れ替わるか」を知っていれば、副作用の時期は予測できる。
化学療法中の患者が発熱で受診したら、最終投与日から何日目かを最初に聞く。それだけで危険度の見当がつく。
English version
Core
Give an antitumour drug and the blood counts do not fall that day. The cells already in the blood go on working until their lifespan is over. So when they begin to fall is set by the lifespan of the cell.
| Neutrophil | Lifespan in blood half a day to a day | Falls first. The nadir is day 7–14. Recovery in 3–4 weeks |
| Platelet | Lifespan 7–10 days | Falls a little after the neutrophils |
| Red cell | Lifespan 120 days | Does not fall suddenly. Anaemia advances slowly with repeated cycles |
Hence the course "well immediately after the infusion and febrile on day 10". Tell the patient this period specifically.
The interval to the next dose (3–4 weeks) is set by the time the neutrophils take to return. Not the half-life of the drug but the time for normal tissue to recover sets the interval.
Going further
⚠️ Treat febrile neutropenia as an emergency.
- Defined as a neutrophil count below 500/μL (or below 1000 and falling) with fever.
- Start a broad-spectrum antibiotic within an hour, before the focus or the organism is known.
- The signs of inflammation do not appear — with no neutrophils, neither pus nor an infiltrate forms readily. Fever may be the only sign.
"Few findings" does not mean "mild" — this single point is the most important.
The pattern of suppression differs with the drug.
- Nitrosoureas, mitomycin — the nadir comes late, at 4–6 weeks. Recovery is slow and it is cumulative.
- Bleomycin, vincristine — marrow suppression is mild (instead, pulmonary fibrosis and neuropathy limit the dose).
- G-CSF — hastens the recovery of neutrophils. Prophylaxis is given with regimens in which febrile neutropenia is frequent.
The same reasoning applies to other adverse effects. Stomatitis on day 5–7 (the oral mucosa renews in days), hair loss at 2–3 weeks (the division rate of the hair matrix). Knowing which normal tissue turns over how fast, the timing of the adverse effects can be predicted.
In the clinic
When a patient on chemotherapy presents with fever, first ask how many days it is since the last dose. That alone gives an idea of the danger.
まとめ
| 葉酸とチミジル酸を狙う — メトトレキサートと5-フルオロウラシル | チミジル酸合成は、DNA合成の律速である。 |
|---|---|
| プリンを狙う薬と、鎖を止める薬 | 薬作用要点6-メルカプトプリン/アザチオプリンプリン合成を阻害キサンチンオキシダーゼで分解される → アロプリノール併用で毒性が跳ね上がるミコフェノール酸イノシン一リン酸脱水素酵素… |
| ロイコボリン救済 — 効かせたい細胞だけを、後から助ける | メトトレキサートはジヒドロ葉酸還元酵素を阻害し、活性型葉酸(テトラヒドロ葉酸)を枯渇させる。 |
| 同じ量で死ぬ人がいる — 代謝の個人差が、抗腫瘍薬で牙をむく | 抗腫瘍薬は治療域が狭い。だから代謝の個人差が、そのまま重篤な副作用になる。 |
| メトトレキサートは、量が変われば別の薬になる | 同じ薬でありながら、抗癌剤としての使い方と、抗リウマチ薬としての使い方で、効いている機序が違うと考えられている。 |
| 骨髄抑制は、細胞の寿命どおりの順序で現れる | 抗癌剤を投与しても、その日に血球は減らない。 |
このノートは医学生が授業の内容を自分の言葉でまとめたもので、診療の判断に使うものではありません。誤りに気づいたらお知らせください。

