
ホモシステインは、それ自体が栄養素でも伝達物質でもない中間体である。にもかかわらず臨床で重視されるのは、ここで葉酸・ビタミンB12・ビタミンB6の3つが交差するためで、血中濃度が3つの欠乏の感度の高い指標になる。
そして溜まると血管内皮を傷害し、血栓症を起こす。代謝の中間体が病気を作る、分かりやすい例である。
- メチオニン回路とトランススルフレーション — 2つの出口
- ホモシスチン尿症 — Marfan症候群に似て、血栓を起こす
- MTHFR と一炭素単位 — メチル基は、どこから来るのか
- システインの行き先 — グルタチオン・タウリン・硫酸
- ホモシステインを下げても、心血管イベントは減らなかった
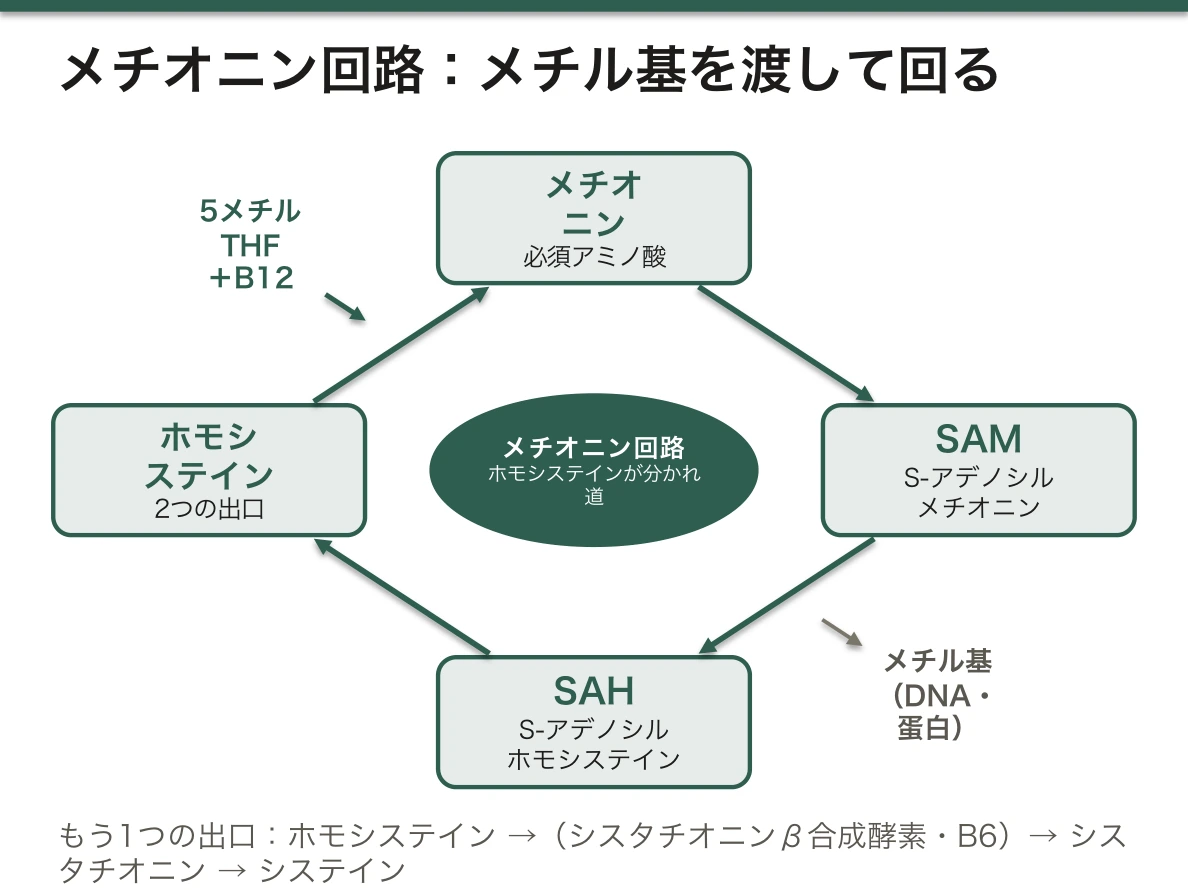
メチオニン回路とトランススルフレーション — 2つの出口
ホモシステインには2つの行き先がある。
1. 再メチル化(メチオニンへ戻る)
ホモシステイン →(メチオニン合成酵素)→ メチオニン
補酵素:ビタミンB12(メチルコバラミン)/メチル基の供与体:5メチルテトラヒドロ葉酸
2. トランススルフレーション(システインへ抜ける)
ホモシステイン →(シスタチオニンβ合成酵素)→ シスタチオニン → システイン
補酵素:ビタミンB6
- メチオニン → S-アデノシルメチオニンは、体内の主要なメチル基供与体(DNA・蛋白・神経伝達物質のメチル化)
- システインはグルタチオン・タウリン・硫酸の材料
- システインは条件付き必須アミノ酸——メチオニンから作れるので、通常は必須でない
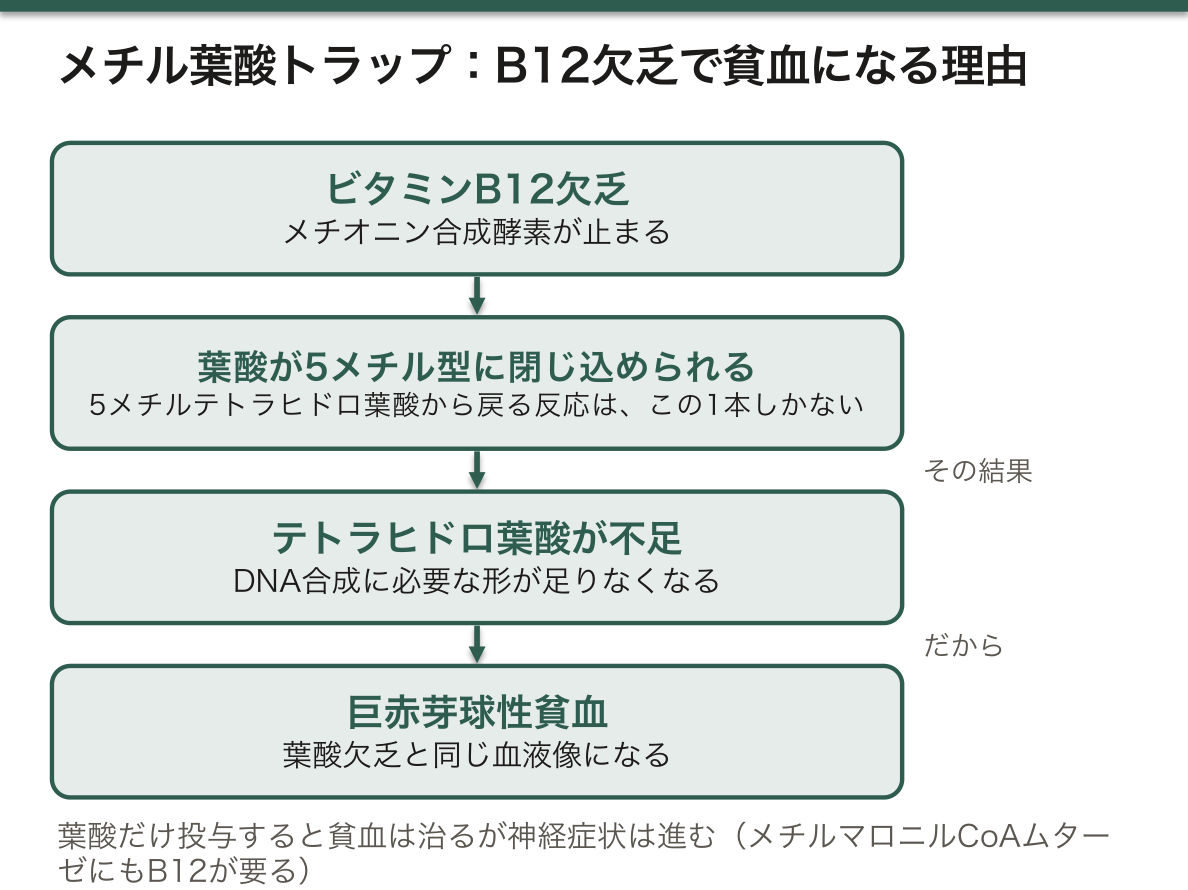
葉酸トラップ(メチル葉酸トラップ)が、ビタミンB12欠乏の症状を説明する鍵になる。
葉酸は体内で5メチルテトラヒドロ葉酸として最も多く存在するが、この形から他の形へ戻る反応はメチオニン合成酵素の1本しかない。ビタミンB12が欠乏するとこの反応が止まり、葉酸が5メチル型に閉じ込められる。
- 結果としてDNA合成に必要なテトラヒドロ葉酸が不足し、巨赤芽球性貧血になる
- だからビタミンB12欠乏でも葉酸欠乏でも、血液像は同じ
- しかし葉酸を投与すると貧血だけ改善し、神経症状は進行する——ビタミンB12はもう一つの反応(メチルマロニルCoAムターゼ)にも要るからで、そちらは葉酸では代償できない
亜急性連合性脊髄変性症を防ぐには、葉酸を出す前にビタミンB12を確認する——この順序は臨床上きわめて重要である。
鑑別にはメチルマロン酸を測る。ビタミンB12欠乏では上がり、葉酸欠乏では上がらない。ホモシステインは両方で上がるので単独では区別できない。
| ホモシステイン | メチルマロン酸 | |
|---|---|---|
| ビタミンB12欠乏 | ↑ | ↑ |
| 葉酸欠乏 | ↑ | → |
| ビタミンB6欠乏 | ↑ | → |
English version
Core
Homocysteine has two destinations.
1. Remethylation (back to methionine)
Homocysteine → (methionine synthase) → methionine
Coenzyme: vitamin B12 (methylcobalamin) / methyl donor: 5-methyl-THF
2. Transsulfuration (out to cysteine)
Homocysteine → (cystathionine β-synthase) → cystathionine → cysteine
Coenzyme: vitamin B6
- Methionine → S-adenosylmethionine, the body’s principal methyl donor (methylation of DNA, protein and neurotransmitters).
- Cysteine is the material of glutathione, taurine and sulphate.
- Cysteine is a conditionally essential amino acid — made from methionine, so usually not essential.
Going further
The methyl folate trap is the key to explaining the symptoms of B12 deficiency. Folate exists in the body chiefly as 5-methyl-THF, and the only reaction returning it from that form is methionine synthase. In B12 deficiency that reaction stops and folate is trapped in the methyl form.
- The result is a shortage of the tetrahydrofolate needed for DNA synthesis — a megaloblastic anaemia.
- So the blood picture is the same in B12 and in folate deficiency.
- But giving folate improves only the anaemia while the neurological disease progresses — B12 is needed for another reaction as well (methylmalonyl-CoA mutase), and folate cannot substitute there.
To prevent subacute combined degeneration, confirm the B12 before prescribing folate — the order matters greatly in practice.
The differential is methylmalonic acid. It rises in B12 deficiency and not in folate deficiency. Homocysteine rises in both and cannot separate them alone.
| Homocysteine | Methylmalonic acid | |
|---|---|---|
| B12 deficiency | ↑ | ↑ |
| Folate deficiency | ↑ | → |
| B6 deficiency | ↑ | → |
ホモシスチン尿症 — Marfan症候群に似て、血栓を起こす
シスタチオニンβ合成酵素の欠損が最多。常染色体潜性遺伝。
| 所見 | Marfan症候群との違い |
|---|---|
| 高身長・細長い四肢・クモ状指 | 共通 |
| 水晶体亜脱臼 | 下方へずれる(Marfan症候群は上方) |
| 知的障害 | Marfan症候群には無い |
| 血栓症 | Marfan症候群には無い。若年の脳梗塞・深部静脈血栓 |
| 骨粗鬆症 | 共通ではない |
- 治療:ビタミンB6大量投与(反応型がある)、メチオニン制限・システイン補充、ベタイン(別経路で再メチル化を促す)
- 葉酸とビタミンB12も併用する
「Marfan様の体型+水晶体のずれ」を見たら、水晶体がどちらへずれているかを必ず確認する。方向が違うのは、Zinn小帯(毛様体小帯)のどの部分が弱るかが病態によって異なるためである。この一点で全身管理の方針が変わる——Marfan症候群なら大動脈、ホモシスチン尿症なら血栓である。
血栓を起こす機序は、ホモシステインが血管内皮を直接傷害し、酸化ストレスを増やし、第V因子の活性化と血小板凝集を促すことによる。加えてコラーゲンの架橋を妨げるため、結合組織も弱くなる——体型がMarfan症候群に似るのはこのためである。
手術と麻酔で血栓リスクが跳ね上がるので、周術期の輸液・早期離床・抗凝固が要る。診断されていない患者が術後に若年で脳梗塞を起こすのが、この疾患の最も恐ろしい形である。
軽度の高ホモシステイン血症は、はるかにありふれている。メチレンテトラヒドロ葉酸還元酵素の多型(C677T)は日本人にも多く、葉酸が不足していると血中ホモシステインが上がる。ただし葉酸を投与してホモシステインを下げても、心血管イベントは減らなかった——高比重リポ蛋白のときと同じく、マーカーと因果を混同してはいけないという教訓がここにもある。
葉酸の意義が確立しているのは神経管閉鎖障害の予防のほうで、妊娠前から1日400 μgの摂取が推奨される。閉鎖は妊娠4週までに完了するので、妊娠が分かってからでは間に合わない。
English version
Core
Cystathionine β-synthase deficiency is the commonest. Autosomal recessive.
| Finding | Compared with Marfan syndrome |
|---|---|
| Tall stature, long limbs, arachnodactyly | Shared |
| Lens dislocation | Downwards (upwards in Marfan) |
| Intellectual disability | Absent in Marfan |
| Thrombosis | Absent in Marfan. Stroke and deep vein thrombosis in the young |
| Osteoporosis | Not shared |
Treatment: high-dose vitamin B6 (there is a responsive form), methionine restriction with cysteine supplementation, betaine (promoting remethylation by another route). Folate and B12 are given with them.
Going further
Seeing a Marfanoid habitus with a dislocated lens, always confirm in which direction the lens has moved. The direction differs because which part of the zonule weakens differs between the diseases. This one point changes the whole plan of management — the aorta in Marfan, thrombosis in homocystinuria.
The mechanism of thrombosis is that homocysteine injures the endothelium directly, increases oxidative stress and promotes activation of factor V and platelet aggregation. It also impedes the cross-linking of collagen — hence the resemblance in habitus to Marfan syndrome.
The thrombotic risk leaps with surgery and anaesthesia, so perioperative fluid, early mobilisation and anticoagulation are required. An undiagnosed patient having a stroke after an operation at a young age is the most feared form of this disease.
Mild hyperhomocysteinaemia is far commoner. The MTHFR C677T polymorphism is common in Japanese people, and with insufficient folate the blood homocysteine rises. But giving folate and lowering the homocysteine did not reduce cardiovascular events — as with HDL, a lesson against confusing a marker with a cause.
Where folate’s value is established is the prevention of neural tube defects, 400 µg a day recommended from before conception. Closure is complete by four weeks, so starting when the pregnancy is known is too late.
MTHFR と一炭素単位 — メチル基は、どこから来るのか
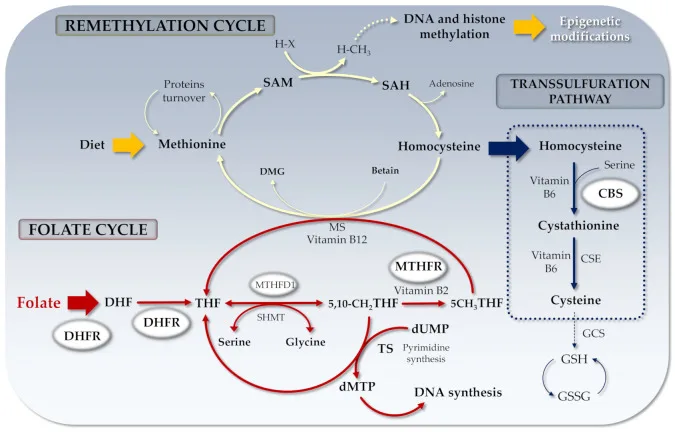
一炭素単位(メチル基など)を運ぶのはテトラヒドロ葉酸になる。
葉酸は2つの用途に取り合われている。
| 用途 | 形 | 行き先 |
|---|---|---|
| ①DNA 合成 | 5,10-メチレンTHF | チミジル酸の合成 |
| ②メチル化 | 5-メチルTHF | ホモシステイン → メチオニン → S-アデノシルメチオニン |
その分かれ道にあるのが MTHFR(メチレンテトラヒドロ葉酸還元酵素)で、①から②へ不可逆に押し流す。
C677T 多型では酵素活性が下がり、ホモシステインが上がりやすい——日本人で TT 型は約 10〜15%。
「葉酸を、DNA を作るのに使うか、メチル基を渡すのに使うか」という配分の問題が、この項の骨格になる。MTHFR がその配分を決めている(ビタミンB12 と葉酸の項)——「1つの酵素が、2つの需要を仲裁している」。
メチル葉酸トラップという現象も、ここから出てくる。ビタミンB12 が無いと 5-メチルTHF から先へ進めず、葉酸が使えない形で溜まる——「B12 欠乏で、葉酸が足りているのに巨赤芽球性貧血になる理由になる」。
MTHFR 多型と葉酸の摂取は、神経管閉鎖障害の危険と関係する(妊娠前からの医療の章)——「だから多型があってもなくても、妊娠を計画する時点から葉酸を摂る」。
メトトレキサートは、この経路の入口を止める薬になる(ロイコボリン救済の項)——「①も②も同時に止まるので、粘膜も血球も傷む」。
ホモシステイン高値は心血管疾患と関連するが、下げても事故が減るとは示されていない(検査の性能の章)——「相関があることと、介入が有効であることは別になる」。
English version
Core
One-carbon units (methyl groups and others) are carried by tetrahydrofolate. Folate is contended for by two uses.
| Use | Form | Destination |
|---|---|---|
| ① DNA synthesis | 5,10-methylene-THF | Synthesis of thymidylate |
| ② Methylation | 5-methyl-THF | Homocysteine → methionine → SAM |
At that parting stands MTHFR (methylenetetrahydrofolate reductase), which pushes irreversibly from ① to ②. In the C677T polymorphism the activity falls and homocysteine rises readily — the TT genotype is about 10–15 per cent in Japanese people.
Going further
The skeleton of this section is the question of allocation — is the folate to be used for making DNA or for handing over methyl groups? MTHFR decides that allocation — one enzyme arbitrating between two demands.
The methyl folate trap comes out of this too. Without B12 it cannot proceed beyond 5-methyl-THF and folate accumulates in an unusable form — the reason B12 deficiency gives a megaloblastic anaemia with adequate folate.
The MTHFR polymorphism and folate intake bear on the risk of neural tube defects — which is why folate is taken from the time a pregnancy is planned, with or without the polymorphism.
Methotrexate blocks the entrance to this pathway — ① and ② stop together, so mucosa and blood cells are both damaged.
A high homocysteine is associated with cardiovascular disease, but lowering it has not been shown to reduce events — an association and an effective intervention are different things.
システインの行き先 — グルタチオン・タウリン・硫酸
システインはメチオニンから、トランススルフレーション経路で作られる(半必須アミノ酸)。ビタミンB6 が要る。
| 行き先 | できるもの | 役割 |
|---|---|---|
| ①グルタチオン | グルタミン酸+システイン+グリシン | 還元力・解毒(律速はシステインの供給) |
| ②タウリン | — | 胆汁酸の抱合・膜の安定・網膜と心筋 |
| ③硫酸(PAPS) | 活性硫酸 | 硫酸抱合(第II相)・グリコサミノグリカンの硫酸化 |
| ④蛋白 | ジスルフィド結合 | 立体構造の固定 |
硫化水素も、この経路の酵素(CBS・CSE)が作る気体伝達物質になる。
「グルタチオンの合成が、システインの供給で決まる」ことが、解毒薬の設計そのものになっている。N-アセチルシステインは、律速になっている材料を直接入れている(アセトアミノフェン中毒の項)——「グルタチオンそのものを飲んでも、細胞内には届かない」。
硫酸抱合には上限がある(第I相と第II相の章)——「アセトアミノフェンの過量で抱合が飽和するのは、この供給が尽きるからになる」。
タウリンが胆汁酸の抱合に使われることは、乳児の栄養で問題になる(乳児の栄養の章)——「新生児は合成能が低いので、母乳と調製乳に含まれている」。
ジスルフィド結合は、蛋白の立体構造を固定する唯一の共有結合になる(蛋白質の構造の章)——「還元剤で切れると、蛋白は形を失う。毛髪のパーマも同じ化学になる」。
N-アセチルシステインが去痰薬でもあるのは、痰のムチンのジスルフィド結合を切るからになる(呼吸器の薬の章)——「同じ分子が、解毒薬としても粘液溶解薬としても使われている」。
English version
Core
Cysteine is made from methionine by transsulfuration (a semi-essential amino acid), requiring vitamin B6.
| Destination | Product | Role |
|---|---|---|
| ① | Glutathione (glutamate + cysteine + glycine) | Reducing power, detoxification (the rate-limiting step is the supply of cysteine) |
| ② | Taurine | Conjugation of bile acids, membrane stability, retina and myocardium |
| ③ | Sulphate (PAPS) | Sulphate conjugation (phase II), sulphation of glycosaminoglycans |
| ④ | Protein | Disulphide bonds — fixing the conformation |
Hydrogen sulphide is also made by the enzymes of this pathway (CBS, CSE) as a gaseous transmitter.
Going further
That the synthesis of glutathione is set by the supply of cysteine is itself the design of an antidote. N-acetylcysteine supplies the rate-limiting material directly — swallowing glutathione itself does not get it into the cell.
Sulphate conjugation has a ceiling — the saturation of conjugation in paracetamol overdose is that supply running out.
That taurine is used in conjugating bile acids matters in infant nutrition — the newborn’s synthetic capacity is low, so it is present in breast milk and in formula.
The disulphide bond is the only covalent bond fixing the conformation of a protein — cut with a reducing agent, the protein loses its shape. The chemistry of a permanent wave is the same.
That N-acetylcysteine is also an expectorant is because it cuts the disulphide bonds of the mucins of sputum — the same molecule used both as an antidote and as a mucolytic.
ホモシステインを下げても、心血管イベントは減らなかった
高ホモシステイン血症は、動脈硬化・血栓症・認知症と強く相関する。機序も説明できる——内皮の障害、酸化ストレス、コラーゲンの架橋異常。だから「下げれば病気が減る」と期待された。
ところが大規模な介入試験の結果はそろって否定的だった。葉酸・ビタミン B6・B12 を投与するとホモシステインは確かに 20〜30% 下がるが、心筋梗塞も死亡も減らなかった。
相関があり、機序も説明でき、検査値も動くのに、アウトカムが変わらないことがある。これが臨床研究の核心的な教訓である。
なぜこうなるのかを、3つの可能性に分けて考える。
| 交絡 | ホモシステインは腎機能低下・喫煙・低栄養で上がる | これらが本当の原因で、ホモシステインはその影だった可能性 |
| 逆の因果 | 動脈硬化そのものがホモシステインを上げていた | 結果を原因と読んでいた可能性 |
| 介入が遅い/短い | 血管の変化は数十年かけて進む | 数年の試験では差が出ない可能性 |
同じ結末をたどった例は多い。ホルモン補充療法と心血管疾患、抗酸化ビタミンと癌、抗不整脈薬による心室性期外収縮の抑制(CAST 試験では死亡が増えた)。「検査値(代用のアウトカム)が良くなること」と「患者が良くなること」は別である。
それでもホモシステインを測る場面は残る。
- 若年の血栓症・動脈硬化——ホモシスチン尿症という単一遺伝子疾患を探すため。こちらは治療で明確に予後が改善する
- ビタミン B12・葉酸欠乏の感度の高い指標として——血中 B12 が境界値のとき、ホモシステインとメチルマロン酸が上がっていれば欠乏と判断できる
「病気の指標」として役に立たなくても、「欠乏の指標」としては有用である——検査は何の目的で測るかで価値が変わる。
新しい検査や薬を勧められたとき、「変わったのは検査値か、患者の予後か」を確かめる。この問いだけで、避けられる誤りが多い。
English version
Core
Hyperhomocysteinaemia correlates strongly with atherosclerosis, thrombosis and dementia, and the mechanism can be explained — endothelial injury, oxidative stress, abnormal collagen cross-linking. So it was expected that lowering it would reduce disease.
The results of the large intervention trials were uniformly negative. Giving folate, B6 and B12 does lower homocysteine by 20–30 per cent, but neither myocardial infarction nor mortality fell.
There can be an association, an explicable mechanism, and a laboratory value that moves, and yet no change in outcome. This is the central lesson of clinical research.
Going further
Consider why, under three possibilities.
| Possibility | |
|---|---|
| Confounding | Homocysteine rises with renal impairment, smoking and malnutrition. Those may have been the real cause and homocysteine its shadow |
| Reverse causation | Atherosclerosis itself may have raised the homocysteine. The result read as the cause |
| The intervention too late or too short | Vascular change takes decades. A trial of a few years may not show a difference |
Many examples have ended the same way: hormone replacement and cardiovascular disease; antioxidant vitamins and cancer; suppression of ventricular ectopics with antiarrhythmics (mortality increased in the CAST trial). "The laboratory value (the surrogate outcome) improving" and "the patient improving" are different.
There remain places where homocysteine is measured.
- Thrombosis or atherosclerosis in a young person — to look for the monogenic disease homocystinuria. There, treatment clearly improves the outcome.
- As a sensitive index of B12 and folate deficiency — with a borderline B12, a raised homocysteine and methylmalonic acid establish the deficiency.
Useless as an index of disease, it remains useful as an index of deficiency — the value of a test changes with the purpose for which it is measured.
In the clinic
When a new test or drug is recommended, ask whether what changed was the laboratory value or the patient’s outcome. That question alone avoids a great many errors.
まとめ
| メチオニン回路とトランススルフレーション — 2つの出口 | ホモシステインには2つの行き先がある。 |
|---|---|
| ホモシスチン尿症 — Marfan症候群に似て、血栓を起こす | シスタチオニンβ合成酵素の欠損が最多。常染色体潜性遺伝。 |
| MTHFR と一炭素単位 — メチル基は、どこから来るのか | 一炭素単位(メチル基など)を運ぶのはテトラヒドロ葉酸になる。 |
| システインの行き先 — グルタチオン・タウリン・硫酸 | システインはメチオニンから、トランススルフレーション経路で作られる(半必須アミノ酸)。 |
| ホモシステインを下げても、心血管イベントは減らなかった | 高ホモシステイン血症は、動脈硬化・血栓症・認知症と強く相関する。 |
このノートは医学生が授業の内容を自分の言葉でまとめたもので、診療の判断に使うものではありません。誤りに気づいたらお知らせください。

