
先天代謝異常症は数が多く、名前だけを並べると覚えられない。「どこで詰まって、何が溜まり、何が作れなくなるか」の3点で整理すれば、症状は導ける。
この章ではフェニルアラニン・チロシン(芳香族)とロイシン・イソロイシン・バリン(分枝鎖)を扱う。どちらも新生児マススクリーニングの中核であり、食事療法で予後が変わる——見つけることに意味がある疾患群である。
- フェニルケトン尿症 — 溜まるものと、作れないもの
- メープルシロップ尿症と有機酸血症 — 匂いと、代謝性アシドーシス
- チロシンの分解が詰まる — 尿が黒くなる病気、肝が壊れる病気
- ナイアシンが足りなくなる4つの入口 — ペラグラを機序で分ける
- グルタル酸血症 I 型 — 頭の大きい乳児が、発熱を境に動けなくなる
フェニルケトン尿症 — 溜まるものと、作れないもの
フェニルアラニン水酸化酵素の欠損で、フェニルアラニン → チロシンの変換ができない。
| 結果 | 症状 |
|---|---|
| フェニルアラニンが溜まる | 知的障害・けいれん・ネズミ尿様の体臭(フェニル酢酸) |
| チロシンが作れない | メラニンが減る → 色白・金髪・碧眼 |
- 常染色体潜性遺伝。日本では約7万人に1人
- 治療は低フェニルアラニン食。フェニルアラニンは必須アミノ酸なので完全除去はできない——制限であって除去ではない
- アスパルテームはフェニルアラニンを含むので摂取できない
- 母体フェニルケトン尿症——妊娠前から管理しないと、胎児に小頭症・心奇形・知的障害が起きる
「溜まるもの」と「作れないもの」の両方を見る——これが先天代謝異常症を読む基本の型である。フェニルケトン尿症では、知的障害は溜まったフェニルアラニンによるもの、色素の薄さは作れないチロシンによるもので、原因が別である。だからチロシンを補充しても知的障害は防げないし、フェニルアラニンを制限しても色素は完全には戻らない。
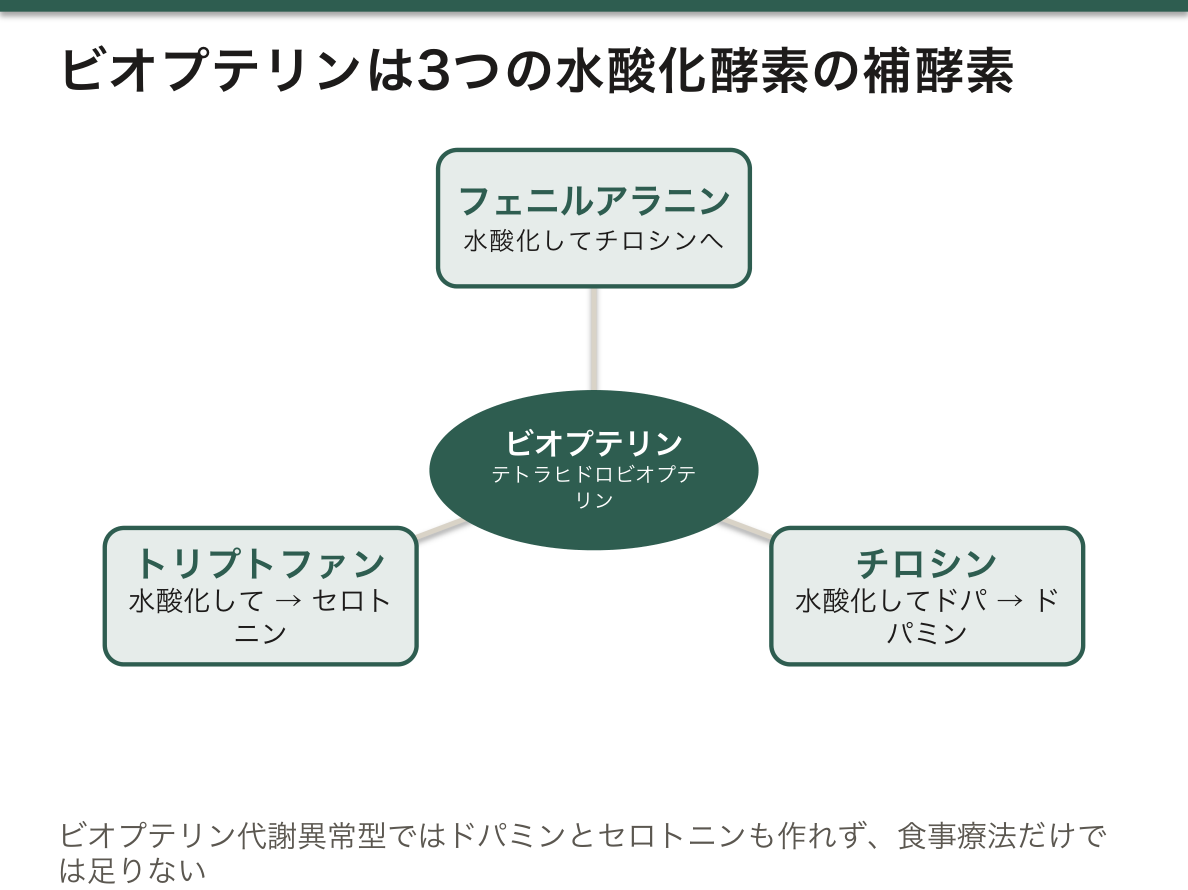
約2%はビオプテリン代謝異常型(悪性型)である。フェニルアラニン水酸化酵素そのものは正常で、補酵素であるテトラヒドロビオプテリンが作れない、または再生できない。ここが決定的に重要なのは、テトラヒドロビオプテリンがチロシン水酸化酵素とトリプトファン水酸化酵素の補酵素でもあるためである。
- つまりドパミンとセロトニンも作れない
- 食事療法だけでは神経症状が進行する。ビオプテリンとレボドパ・5ヒドロキシトリプトファンの補充が要る
- だからスクリーニング陽性例では必ず病型を鑑別する
母体フェニルケトン尿症の問題は「本人は治療済みでも子が侵される」点にある。胎盤はフェニルアラニンを能動輸送で胎児側へ濃縮するので、母体濃度の1.5倍近くが胎児に届く。器官形成期はすでに妊娠初期なので、妊娠が分かってからでは遅い——女性患者には妊娠計画の段階からの食事管理を伝える必要がある。成人期に食事療法を自己中断していた例で問題になる。
English version
Core
Deficiency of phenylalanine hydroxylase means phenylalanine cannot be converted to tyrosine.
| Consequence | Symptoms |
|---|---|
| Phenylalanine accumulates | Intellectual disability, seizures, a mousy body odour (phenylacetate) |
| Tyrosine cannot be made | Melanin falls → pale skin, fair hair, blue eyes |
- Autosomal recessive; about 1 in 70,000 in Japan.
- Treatment is a low-phenylalanine diet. Phenylalanine is an essential amino acid, so it cannot be removed entirely — restriction, not elimination.
- Aspartame contains phenylalanine and cannot be taken.
- Maternal PKU — without management from before conception, the fetus develops microcephaly, cardiac malformation and intellectual disability.
Going further
Look at both what accumulates and what cannot be made — this is the basic form of reading an inborn error. In PKU the intellectual disability is due to the accumulated phenylalanine and the pale colouring to the tyrosine that cannot be made: different causes. So supplementing tyrosine does not prevent the intellectual disability, and restricting phenylalanine does not fully restore the pigment.
About 2 per cent are the biopterin (malignant) variant. Phenylalanine hydroxylase itself is normal but tetrahydrobiopterin, its coenzyme, cannot be made or regenerated. What makes this decisive is that tetrahydrobiopterin is also the coenzyme of tyrosine hydroxylase and tryptophan hydroxylase.
- So dopamine and serotonin cannot be made either.
- Diet alone leaves the neurological disease to progress. Biopterin with levodopa and 5-hydroxytryptophan is required.
- So the variant must always be determined in a screen-positive case.
The problem of maternal PKU is that the child is affected although the mother is treated. The placenta actively concentrates phenylalanine towards the fetus, so nearly 1.5 times the maternal level reaches it. Organogenesis is already in the first trimester, so starting when the pregnancy is known is too late — a woman with PKU must be told about dietary control from the stage of planning. It matters in patients who stopped the diet themselves in adult life.
メープルシロップ尿症と有機酸血症 — 匂いと、代謝性アシドーシス
メープルシロップ尿症:分枝鎖αケト酸脱水素酵素の欠損。ロイシン・イソロイシン・バリンとそのケト酸が溜まる。
- 甘い焦げたような尿の匂い・哺乳不良・けいれん・後弓反張
- ロイシンが最も神経毒性が強い
- 補酵素はチアミン(ビタミンB1)——チアミン反応型がある
有機酸血症(メチルマロン酸血症・プロピオン酸血症・イソ吉草酸血症など)
| 共通する所見 | 理由 |
|---|---|
| 代謝性アシドーシス(アニオンギャップ開大) | 有機酸そのものが溜まる |
| 高アンモニア血症 | 有機酸が尿素回路を阻害する |
| ケトーシス・低血糖 | 代謝の破綻 |
| 汎血球減少 | 骨髄抑制 |
イソ吉草酸血症は「足の蒸れた匂い」が特徴。
新生児の急性発症型の代謝異常は、3つの検査で当たりを付ける。
- 血液ガス——代謝性アシドーシスがあるか、アニオンギャップは開大しているか
- 血中アンモニア——高いか
- 血糖とケトン体
| アシドーシス | アンモニア | 代表 | |
|---|---|---|---|
| 尿素回路異常症 | 無い(むしろ呼吸性アルカローシス) | 著明高値 | オルニチントランスカルバミラーゼ欠損 |
| 有機酸血症 | あり(開大) | 高値 | メチルマロン酸血症 |
| 脂肪酸酸化異常症 | 軽度 | 軽度高値 | 中鎖アシルCoA脱水素酵素欠損 |
尿素回路異常症で呼吸性アルカローシスになるのは、アンモニアが脳の呼吸中枢を刺激して過換気を起こすためである。「新生児の意識障害で、アシドーシスが無いのにアンモニアが高い」という組み合わせは、この群を強く示唆する。
初期対応は病型が分かる前から始める。異化を止めることが最優先で、蛋白を止め、ブドウ糖を十分量投与して同化に振る。高アンモニア血症が高度なら血液透析。診断を待って治療を遅らせない——神経学的予後はアンモニアが高い時間の長さで決まる。
メチルマロン酸血症にはビタミンB12反応型がある(メチルマロニルCoAムターゼの補酵素がアデノシルコバラミンであるため)。治療可能な型を見逃さないために、必ず補酵素負荷を試す——これが代謝疾患診療の原則である。
English version
Core
Maple syrup urine disease: deficiency of branched-chain α-keto acid dehydrogenase. Leucine, isoleucine and valine and their keto acids accumulate. A sweet, burnt smell to the urine, poor feeding, seizures, opisthotonus.
- Leucine is the most neurotoxic.
- The coenzyme is thiamine — there is a thiamine-responsive form.
The organic acidaemias (methylmalonic, propionic, isovaleric acidaemia and others)
| Shared finding | Reason |
|---|---|
| Metabolic acidosis (widened anion gap) | The organic acid itself accumulates |
| Hyperammonaemia | The organic acids inhibit the urea cycle |
| Ketosis, hypoglycaemia | Metabolic breakdown |
| Pancytopenia | Marrow suppression |
Isovaleric acidaemia is characterised by a smell of sweaty feet.
Going further
Acute metabolic presentation in the newborn is narrowed by three tests: blood gases (is there a metabolic acidosis, is the anion gap widened?), blood ammonia (is it high?), and glucose with ketones.
| Acidosis | Ammonia | Example | |
|---|---|---|---|
| Urea cycle disorder | None (a respiratory alkalosis, rather) | Markedly high | OTC deficiency |
| Organic acidaemia | Present (widened) | High | Methylmalonic acidaemia |
| Fatty acid oxidation disorder | Mild | Mildly high | MCAD deficiency |
A respiratory alkalosis occurs in urea cycle disorders because ammonia stimulates the respiratory centre and causes hyperventilation. The combination "impaired consciousness in a newborn with a high ammonia and no acidosis" strongly suggests this group.
Initial management begins before the type is known. Stopping catabolism comes first: stop protein and give ample glucose to swing it to anabolism. Haemodialysis if the hyperammonaemia is severe. Do not delay treatment for the diagnosis — the neurological outcome is decided by how long the ammonia stays high.
Methylmalonic acidaemia has a vitamin B12-responsive form (adenosylcobalamin being the coenzyme of methylmalonyl-CoA mutase). Always try a coenzyme challenge so as not to miss a treatable form — this is the principle of metabolic practice.
チロシンの分解が詰まる — 尿が黒くなる病気、肝が壊れる病気
チロシンの分解は、ホモゲンチジン酸を経てフマル酸とアセト酢酸に至る——だから糖原性でもケト原性でもある。
その途中の3か所で、別の病気になる。
| 疾患 | 欠損酵素 | 溜まるもの | 症状 |
|---|---|---|---|
| チロシン血症I型 | フマリルアセト酢酸加水分解酵素 | スクシニルアセトン | 肝不全・肝細胞癌・腎尿細管障害(Fanconi 症候群)・「茹でたキャベツ」様の臭い |
| チロシン血症II型 | チロシンアミノ基転移酵素 | チロシン | 角膜の樹枝状潰瘍・掌蹠の角化・知的障害 |
| アルカプトン尿症 | ホモゲンチジン酸酸化酵素 | ホモゲンチジン酸 | 尿が空気に触れて黒くなる・軟骨と強膜の黒色沈着(組織褐変症)・脊椎と大関節の変性 |
チロシン血症I型は、新生児マススクリーニングの対象になっている。

チロシン血症I型の治療が、代謝異常症の治療の考え方を最もよく示している。ニチシノンは、詰まりよりも上流(4-ヒドロキシフェニルピルビン酸ジオキシゲナーゼ)をわざと止める(治療できる先天代謝異常の項)——「毒性のある中間体が作られないよう、手前で流れを止める」。
面白いのは、その結果としてアルカプトン尿症と同じ状態を作っていることになる——「重い病気を、軽い病気に置き換えている」。
実際、その酵素はアルカプトン尿症の治療にも試されている(脊椎の章)——「1つの薬が、隣り合う2つの疾患で逆の使われ方をする」。
ニチシノンを使うときは、チロシンとフェニルアラニンの食事制限を併用する——「上流を止めれば、その手前に溜まるからになる」。
アルカプトン尿症は、成人になってから関節症状で見つかることがある——「おむつや下着に黒い染みが付く、という乳児期の記憶が手がかりになる」。
チロシン血症I型では、肝細胞癌の危険が高い(肝の各論の章)——「治療が始まっても、画像とAFPでの監視を続ける」。
English version
Core
Tyrosine is degraded through homogentisate to fumarate and acetoacetate — so it is both glucogenic and ketogenic. Three points along that road give three different diseases.
| Disease | Enzyme | Accumulates | Features |
|---|---|---|---|
| Tyrosinaemia type I | Fumarylacetoacetate hydrolase | Succinylacetone | Liver failure, hepatocellular carcinoma, renal tubular disease (Fanconi syndrome), a boiled-cabbage smell |
| Tyrosinaemia type II | Tyrosine aminotransferase | Tyrosine | Dendritic corneal ulcers, palmoplantar keratosis, intellectual disability |
| Alkaptonuria | Homogentisate oxidase | Homogentisic acid | The urine blackens in air; black deposition in cartilage and sclera (ochronosis); degeneration of spine and large joints |
Tyrosinaemia type I is included in newborn screening.
Going further
The treatment of tyrosinaemia type I best shows the way of thinking in metabolic disease. Nitisinone deliberately blocks a step upstream of the block (4-hydroxyphenylpyruvate dioxygenase) — stopping the flow before the toxic intermediate can be made.
What is interesting is that the result creates the same state as alkaptonuria — replacing a severe disease with a mild one. The same enzyme has indeed been tried as a treatment for alkaptonuria — one drug used in opposite ways in two neighbouring diseases.
When nitisinone is used, dietary restriction of tyrosine and phenylalanine goes with it — stop the flow upstream and they accumulate in front of the stop.
Alkaptonuria may be found in adult life through joint symptoms — a memory of black stains on the nappy or underwear in infancy is the clue.
In tyrosinaemia type I the risk of hepatocellular carcinoma is high — continue surveillance with imaging and AFP even after treatment has begun.
ナイアシンが足りなくなる4つの入口 — ペラグラを機序で分ける
ナイアシンは食事から摂るほか、トリプトファンからも作られる——トリプトファン 60 mg からナイアシン 1 mg。変換にはビタミンB6 が要る。
だから欠乏に至る入口が4つある。
| 入口 | 機序 |
|---|---|
| ①摂取が少ない | トウモロコシ主体の食事。ナイアシンが結合型で吸収されず、トリプトファンも少ない |
| ②吸収できない | Hartnup 病(中性アミノ酸輸送体の異常)・慢性下痢・アルコール依存 |
| ③材料が奪われる | カルチノイド症候群。腫瘍がトリプトファンをセロトニン合成へ大量に消費する |
| ④変換が止まる | イソニアジドがビタミンB6 を消費する |
ペラグラの三徴——皮膚炎(日光に当たる部位・Casal 首飾り)・下痢・認知症。放置すれば死に至る(4つ目の D)。
「同じ欠乏症に、栄養・遺伝・腫瘍・薬の4つの入口がある」ことが、この項の要点になる。症状から診断がついても、原因はそこから4方向に分かれる(水溶性ビタミンの章)——「欠乏症を見たら、摂取・吸収・消費・変換の4段で考える」。
ナイアシンは NAD⁺ の材料なので、欠乏は全身のエネルギー代謝に響く(NAD⁺ の項)——「増殖の速い組織(皮膚・消化管粘膜)と、需要の大きい脳に症状が出る理由になる」。
皮膚炎が日光に当たる部位に出ることが、診断の決め手になる(皮膚から全身を読む章)——「左右対称で、境界がはっきりしている」。
Hartnup 病は、腎でも同じ輸送体が働かない(尿を読む章)——「中性アミノ酸尿が診断の手がかりになる。多くは無症状で、負荷がかかったときだけ症状が出る」。
イソニアジドを使うときにビタミンB6 を併用するのは、末梢神経障害とペラグラの両方を防ぐためになる(抗酸菌の章)——「1つの併用が、2つの副作用を同時に防いでいる」。
English version
Core
Niacin is taken in the diet and is also made from tryptophan — 1 mg of niacin from 60 mg of tryptophan, the conversion requiring vitamin B6. So there are four entrances to deficiency.
| Entrance | Mechanism |
|---|---|
| ① Too little taken | A maize-based diet. The niacin is bound and unabsorbable and there is little tryptophan |
| ② Cannot be absorbed | Hartnup disease (neutral amino acid transporter), chronic diarrhoea, alcohol dependence |
| ③ The material is taken | Carcinoid syndrome — the tumour consumes tryptophan for serotonin |
| ④ The conversion stops | Isoniazid consumes vitamin B6 |
The triad of pellagra — dermatitis (on sun-exposed skin; Casal’s necklace), diarrhoea, dementia. Untreated it leads to death (the fourth D).
Going further
The point of this section is that one deficiency state has four entrances — nutritional, genetic, neoplastic and pharmacological. The diagnosis may be made from the symptoms, but the cause then divides four ways — seeing a deficiency, think in the four stages of intake, absorption, consumption and conversion.
Niacin is the material of NAD⁺, so deficiency tells throughout energy metabolism — hence symptoms in the rapidly dividing tissues (skin, gut mucosa) and in the brain, where demand is high.
That the dermatitis appears on sun-exposed skin is decisive for the diagnosis — symmetrical and sharply demarcated.
In Hartnup disease the same transporter fails in the kidney — neutral aminoaciduria is the clue. Most are asymptomatic and become symptomatic only under load.
Vitamin B6 is given with isoniazid to prevent both peripheral neuropathy and pellagra — one combination preventing two adverse effects at once.
グルタル酸血症 I 型 — 頭の大きい乳児が、発熱を境に動けなくなる
リジン・ヒドロキシリジン・トリプトファンの分解経路にあるグルタリル CoA 脱水素酵素が働かない病気である。グルタル酸と 3-ヒドロキシグルタル酸が溜まる。
経過の形が独特で、そこが診断の鍵になる。
- 生下時から頭囲が大きい(大頭症)——ほぼ唯一の、発症前の手がかり
- それ以外は正常に発達する——1〜2 歳ごろまで気づかれない
- 感染や予防接種による発熱をきっかけに、急性脳症を起こす——線条体が選択的に壊れ、ジストニアと不随意運動が残る
- 一度壊れた線条体は戻らない。だから発作を起こす前に見つける意味が大きい

⚠️ 虐待と誤られる病気である。この点だけは必ず知っておく。
大頭症に伴って硬膜下血腫と網膜出血が起きることがある。この2つは虐待による頭部外傷の典型的な所見であるため、実際に家族が疑われた事例が報告されている。乳児の硬膜下血腫を見たとき、頭囲の推移と代謝異常症を鑑別に入れられるかが分かれ目になる。
なぜ脳だけが壊れるのか。グルタル酸は極性が高く、血液脳関門を通って外へ出にくい。脳の中で作られたものが脳の中に閉じ込められ、局所の濃度だけが上がる(トラッピング仮説)。「全身の代謝異常なのに、症状が1つの臓器に限られる」という型の代表例である。メチルマロン酸血症で基底核が傷むのも同じ理屈で説明される。
治療は発作を起こさせないことに尽きる。
- リジン制限食とカルニチン補充(グルタル酸をカルニチン抱合で捨てる)
- 発熱時の緊急対応——早期にブドウ糖を十分に入れて異化を止める。「熱が出たらすぐ受診」という指示書を家族に持たせる
日本の新生児マススクリーニング(タンデム質量分析)ではグルタリルカルニチン(C5DC)で拾われる。
乳児の硬膜下血腫+網膜出血で虐待を疑うときも、頭囲の成長曲線を必ず見る。出生時から大きければ、代謝異常症の可能性を排除してから話を進める。
English version
Core
A disease in which glutaryl-CoA dehydrogenase, on the degradative pathway of lysine, hydroxylysine and tryptophan, does not work. Glutaric and 3-hydroxyglutaric acids accumulate.
The shape of the course is peculiar, and that is the key to the diagnosis.
- The head is large from birth (macrocephaly) — almost the only clue before it presents.
- Otherwise development is normal — it goes unnoticed until about one or two years.
- A fever from infection or immunisation triggers an acute encephalopathy — the striatum is selectively destroyed and dystonia and involuntary movements remain.
- A striatum once destroyed does not recover. Hence the great value of finding it before an attack.
Going further
⚠️ This is a disease mistaken for abuse, and this point at least must be known.
With the macrocephaly, subdural haematoma and retinal haemorrhage can occur. These two are the typical findings of abusive head trauma, and families have in fact been suspected. Seeing a subdural haematoma in an infant, whether one can put the growth of the head circumference and a metabolic disease into the differential is the dividing line.
Why is only the brain destroyed? Glutaric acid is highly polar and leaves poorly across the blood–brain barrier. What is made within the brain is trapped there and only the local concentration rises (the trapping hypothesis). The classic instance of a systemic metabolic disorder whose symptoms are confined to one organ. The damage to the basal ganglia in methylmalonic acidaemia is explained the same way.
The treatment amounts to preventing an attack.
- A lysine-restricted diet and carnitine supplementation (discarding glutaric acid as its carnitine conjugate).
- Emergency management with fever — give ample glucose early to stop catabolism. Give the family a written instruction saying "attend at once if a fever begins".
Japanese newborn screening (tandem mass spectrometry) detects it by glutarylcarnitine (C5DC).
In the clinic
Even when suspecting abuse from a subdural haematoma with retinal haemorrhage in an infant, always look at the head circumference growth chart. If it was large from birth, exclude a metabolic disease before taking the conversation further.
まとめ
| フェニルケトン尿症 — 溜まるものと、作れないもの | フェニルアラニン水酸化酵素の欠損で、フェニルアラニン → チロシンの変換ができない。 |
|---|---|
| メープルシロップ尿症と有機酸血症 — 匂いと、代謝性アシドーシス | メープルシロップ尿症:分枝鎖αケト酸脱水素酵素の欠損。 |
| チロシンの分解が詰まる — 尿が黒くなる病気、肝が壊れる病気 | チロシンの分解は、ホモゲンチジン酸を経てフマル酸とアセト酢酸に至る——だから糖原性でもケト原性でもある。 |
| ナイアシンが足りなくなる4つの入口 — ペラグラを機序で分ける | ナイアシンは食事から摂るほか、トリプトファンからも作られる——トリプトファン 60 mg からナイアシン 1 mg。 |
| グルタル酸血症 I 型 — 頭の大きい乳児が、発熱を境に動けなくなる | リジン・ヒドロキシリジン・トリプトファンの分解経路にあるグルタリル CoA 脱水素酵素が働かない病気である。 |
このノートは医学生が授業の内容を自分の言葉でまとめたもので、診療の判断に使うものではありません。誤りに気づいたらお知らせください。

